Okamoto K, Kaizaki Y, Kida Y, Wada H, Takayama T.
Gastrointest Endosc. 2026 Jun 9:S0016-5107(26)06800-8. doi: 10.1016/j.gie.2026.06.010.
17세 여아가 빈혈과 상부위장관내시경(EGD)에서 다발성 위궤양이 발견되어 본원으로 의뢰되었다.
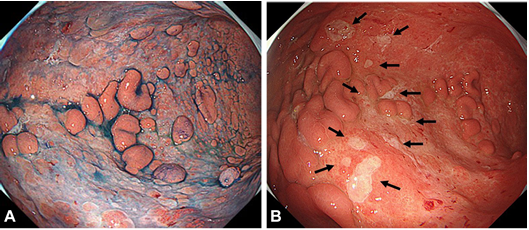
내시경에서는 위체부 대만곡을 따라 결절성 융기가 다수 관찰되었으며, 그 사이의 점막은 위축되어 있었다(A). 또한 위체부 상부에는 다발성 궤양이 관찰되었고(B, 화살표), 전정부 점막은 정상 소견을 보였다.
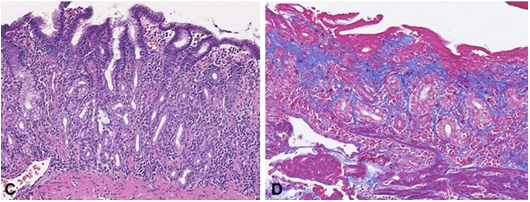
위축된 중간 점막에서 시행한 조직검사(H&E, 원배율 ×100)에서는 위저선 점막에 깊은 림프구 침윤이 관찰되었으며, 이로 인해 유문선 유사 화생(pseudopyloric gland metaplasia)이 형성되어 있었다. 또한 장크로마핀유사세포(enterochromaffin-like cell, ECL) 증식이 동반되어 자가면역성 위염(autoimmune gastritis, AIG)에 합당한 소견을 보였다(C). Azan 염색(원배율 ×100)에서는 상피하 콜라겐층의 국소적인 비후가 확인되었고(D), 이를 바탕으로 자가면역성 위염과 교원성 위염(collagenous gastritis, CG)이 중첩된(overlapping) 증례로 진단하였다.
검사실 검사에서는 대변 Helicobacter pylori 항원이 음성이었고, 항벽세포항체(anti-parietal cell antibody)는 양성이었으며, 항내인자항체(anti-intrinsic factor antibody)는 음성이었다. 혈청 가스트린 농도는 52.9 pmol/L로 증가되어 있었다. 환자는 위산분비억제제와 철분 보충 치료 후 증상이 호전되었으며, 향후 매년 내시경 추적관찰을 시행할 예정이다.
소아에서 발생하는 교원성 위염은 자가면역성 위염의 초기 발현 형태일 가능성이 제기되고 있으나, 그 병태생리는 아직 명확하게 밝혀지지 않았다. 본 증례는 두 질환 사이의 이행 단계(transitional phase)를 시사하는 내시경적 근거를 제시하는 사례로 볼 수 있다. 또한 전형적인 자가면역성 위염이나 교원성 위염의 소견과는 달리, 다발성 위궤양이 동반되었다는 점이 이 증례의 특징이었다.
<Commentary>
This case highlights a rare and intriguing overlap between AIG and CG in an adolescent patient presenting with anemia and multiple gastric ulcers. Both conditions are uncommon in pediatric populations, and their coexistence raises impor tant questions regarding shared pathogenic mechanisms and the potential progression of pediatric-onset CG into autoimmune-mediated gastric injury. The unusual endoscopic appearance of nodular mucosa with intervening atrophic areas, together with multiple gastric ulcers localized to the gastric corpus, further distinguishes this case from the more typical presentations of either AIG or CG alone. Histopathologic evaluation was critical in establishing the diagnosis. Features consistent with AIG, including pseudopyloric gland metaplasia, deep lymphocytic infiltration of the fundic gland mucosa, and enterochromaffin-like cell hyperplasia, coexisted with focal subepithelial collagen deposition characteristic of CG. The presence of both pathologic patterns pro vides valuable morphologic support for the proposed relationship between these 2 entities. In addition, hypergastrinemia and positive anti–parietal cell antibodies further support an underlying autoimmune pathophysiologic process. The presence of multiple gastric ulcers is particularly noteworthy, as ulceration is not a classic feature of either AIG or CG. This case therefore broadens the recognized clinical spectrum of these rare disorders and suggests that overlapping in flammatory mechanisms may contribute to atypical mucosal injury patterns in younger patients.
이 증례는 빈혈과 다발성 위궤양을 동반한 청소년 환자에서 발생한 자가면역성 위염(autoimmune gastritis, AIG)과 교원성 위염(collagenous gastritis, CG)의 드문 중복 사례를 보여주는 매우 흥미로운 증례이다. 두 질환 모두 소아 및 청소년에서 매우 드물게 발생하며, 이들이 함께 나타났다는 사실은 두 질환이 공통된 병인 기전을 공유하는지, 그리고 소아기에 발생한 교원성 위염이 자가면역성 위 손상으로 진행하는 초기 단계일 가능성이 있는지에 대한 중요한 의문을 제기한다. 또한 결절성 점막과 그 사이에 위치한 위축성 점막이 함께 관찰되는 독특한 내시경 소견과, 위체부에 국한된 다발성 위궤양은 전형적인 자가면역성 위염이나 교원성 위염의 내시경 양상과는 구별되는 특징이었다.
조직병리학적 검사는 진단을 확립하는 데 결정적인 역할을 하였다. 유문선 유사 화생(pseudopyloric gland metaplasia), 위저선 점막의 깊은 림프구 침윤, 장크로마핀유사세포(enterochromaffin-like cell, ECL) 증식 등 자가면역성 위염에 합당한 소견과 함께, 교원성 위염의 특징인 국소적인 상피하 콜라겐 침착이 동시에 확인되었다. 이처럼 두 질환의 병리학적 특징이 하나의 조직에서 함께 관찰된 것은, 자가면역성 위염과 교원성 위염 사이의 연관성을 뒷받침하는 중요한 형태학적 근거를 제공한다. 또한 고가스트린혈증(hypergastrinemia)과 항벽세포항체(anti-parietal cell antibody) 양성 소견 역시 기저에 자가면역성 병태생리가 존재함을 뒷받침한다.
특히 다발성 위궤양의 존재는 매우 주목할 만한 소견이다. 위궤양은 자가면역성 위염이나 교원성 위염 모두에서 전형적으로 나타나는 소견이 아니기 때문이다. 따라서 본 증례는 이러한 드문 질환들의 임상적 스펙트럼을 확장하는 사례로 볼 수 있으며, 젊은 환자에서 두 질환의 염증 기전이 중첩되면서 비전형적인 위점막 손상 양상을 유발할 수 있음을 시사한다.
Faisal Kamal, MD
Assistant Editor for Focal Points
Amy Tyberg, MD, FASGE, FACG
Associate Editor for Focal Points


Okamoto K, Kaizaki Y, Kida Y, Wada H, Takayama T.
Gastrointest Endosc. 2026 Jun 9:S0016-5107(26)06800-8. doi: 10.1016/j.gie.2026.06.010.
17세 여아가 빈혈과 상부위장관내시경(EGD)에서 다발성 위궤양이 발견되어 본원으로 의뢰되었다.
내시경에서는 위체부 대만곡을 따라 결절성 융기가 다수 관찰되었으며, 그 사이의 점막은 위축되어 있었다(A). 또한 위체부 상부에는 다발성 궤양이 관찰되었고(B, 화살표), 전정부 점막은 정상 소견을 보였다.
위축된 중간 점막에서 시행한 조직검사(H&E, 원배율 ×100)에서는 위저선 점막에 깊은 림프구 침윤이 관찰되었으며, 이로 인해 유문선 유사 화생(pseudopyloric gland metaplasia)이 형성되어 있었다. 또한 장크로마핀유사세포(enterochromaffin-like cell, ECL) 증식이 동반되어 자가면역성 위염(autoimmune gastritis, AIG)에 합당한 소견을 보였다(C). Azan 염색(원배율 ×100)에서는 상피하 콜라겐층의 국소적인 비후가 확인되었고(D), 이를 바탕으로 자가면역성 위염과 교원성 위염(collagenous gastritis, CG)이 중첩된(overlapping) 증례로 진단하였다.
검사실 검사에서는 대변 Helicobacter pylori 항원이 음성이었고, 항벽세포항체(anti-parietal cell antibody)는 양성이었으며, 항내인자항체(anti-intrinsic factor antibody)는 음성이었다. 혈청 가스트린 농도는 52.9 pmol/L로 증가되어 있었다. 환자는 위산분비억제제와 철분 보충 치료 후 증상이 호전되었으며, 향후 매년 내시경 추적관찰을 시행할 예정이다.
소아에서 발생하는 교원성 위염은 자가면역성 위염의 초기 발현 형태일 가능성이 제기되고 있으나, 그 병태생리는 아직 명확하게 밝혀지지 않았다. 본 증례는 두 질환 사이의 이행 단계(transitional phase)를 시사하는 내시경적 근거를 제시하는 사례로 볼 수 있다. 또한 전형적인 자가면역성 위염이나 교원성 위염의 소견과는 달리, 다발성 위궤양이 동반되었다는 점이 이 증례의 특징이었다.
<Commentary>
This case highlights a rare and intriguing overlap between AIG and CG in an adolescent patient presenting with anemia and multiple gastric ulcers. Both conditions are uncommon in pediatric populations, and their coexistence raises impor tant questions regarding shared pathogenic mechanisms and the potential progression of pediatric-onset CG into autoimmune-mediated gastric injury. The unusual endoscopic appearance of nodular mucosa with intervening atrophic areas, together with multiple gastric ulcers localized to the gastric corpus, further distinguishes this case from the more typical presentations of either AIG or CG alone. Histopathologic evaluation was critical in establishing the diagnosis. Features consistent with AIG, including pseudopyloric gland metaplasia, deep lymphocytic infiltration of the fundic gland mucosa, and enterochromaffin-like cell hyperplasia, coexisted with focal subepithelial collagen deposition characteristic of CG. The presence of both pathologic patterns pro vides valuable morphologic support for the proposed relationship between these 2 entities. In addition, hypergastrinemia and positive anti–parietal cell antibodies further support an underlying autoimmune pathophysiologic process. The presence of multiple gastric ulcers is particularly noteworthy, as ulceration is not a classic feature of either AIG or CG. This case therefore broadens the recognized clinical spectrum of these rare disorders and suggests that overlapping in flammatory mechanisms may contribute to atypical mucosal injury patterns in younger patients.
이 증례는 빈혈과 다발성 위궤양을 동반한 청소년 환자에서 발생한 자가면역성 위염(autoimmune gastritis, AIG)과 교원성 위염(collagenous gastritis, CG)의 드문 중복 사례를 보여주는 매우 흥미로운 증례이다. 두 질환 모두 소아 및 청소년에서 매우 드물게 발생하며, 이들이 함께 나타났다는 사실은 두 질환이 공통된 병인 기전을 공유하는지, 그리고 소아기에 발생한 교원성 위염이 자가면역성 위 손상으로 진행하는 초기 단계일 가능성이 있는지에 대한 중요한 의문을 제기한다. 또한 결절성 점막과 그 사이에 위치한 위축성 점막이 함께 관찰되는 독특한 내시경 소견과, 위체부에 국한된 다발성 위궤양은 전형적인 자가면역성 위염이나 교원성 위염의 내시경 양상과는 구별되는 특징이었다.
조직병리학적 검사는 진단을 확립하는 데 결정적인 역할을 하였다. 유문선 유사 화생(pseudopyloric gland metaplasia), 위저선 점막의 깊은 림프구 침윤, 장크로마핀유사세포(enterochromaffin-like cell, ECL) 증식 등 자가면역성 위염에 합당한 소견과 함께, 교원성 위염의 특징인 국소적인 상피하 콜라겐 침착이 동시에 확인되었다. 이처럼 두 질환의 병리학적 특징이 하나의 조직에서 함께 관찰된 것은, 자가면역성 위염과 교원성 위염 사이의 연관성을 뒷받침하는 중요한 형태학적 근거를 제공한다. 또한 고가스트린혈증(hypergastrinemia)과 항벽세포항체(anti-parietal cell antibody) 양성 소견 역시 기저에 자가면역성 병태생리가 존재함을 뒷받침한다.
특히 다발성 위궤양의 존재는 매우 주목할 만한 소견이다. 위궤양은 자가면역성 위염이나 교원성 위염 모두에서 전형적으로 나타나는 소견이 아니기 때문이다. 따라서 본 증례는 이러한 드문 질환들의 임상적 스펙트럼을 확장하는 사례로 볼 수 있으며, 젊은 환자에서 두 질환의 염증 기전이 중첩되면서 비전형적인 위점막 손상 양상을 유발할 수 있음을 시사한다.
Faisal Kamal, MD
Assistant Editor for Focal Points
Amy Tyberg, MD, FASGE, FACG
Associate Editor for Focal Points