Damianos JA, Jin M, Ospina-Velasquez L, Chowla N, Wang XJ.
Minerva Gastroenterol (Torino). 2026 Jun;72(2):160-168. doi: 10.23736/S2724-5985.26.04066-0.
Introduction
Small intestinal microbial overgrowth (MO)는 소장 내 미생물(세균, 바이러스, 진균, 고세균)이 과도하게 증가함으로써 발생하는 위장관 증상의 증후군이다. 소장에서 비정상적으로 높은 세균 밀도가 존재하는 상태를 small intestinal bacterial overgrowth (SIBO)라고 하며, 이는 복부 불편감, 복부 팽만, 가스 증가, 배변 습관 변화와 같은 위장관 증상을 유발할 수 있다. SIBO는 처음에는 장 정체(intestinal stasis)와 해부학적 구조 변화가 있는 환자, 즉 수술로 장 구조가 변형된 환자(과거에는 “blind loop syndrome”이라 불림)에서 발생하는 것으로 알려졌으며, 심한 경우 염증, 융모 위축, 소화 장애, 흡수 장애가 나타났다. 이후 소장 미생물 시퀀싱을 이용한 최근 연구에서는 원인 미생물들이 밝혀지면서 특정 질병 표현형들이 정의되었다. SIBO에서는 Enterobacteriaceae가 우세해지는 경향이 있으며, 정상 장내 세균을 대체하는 이른바 disruptor taxa로 Klebsiella, Escherichia, Enterococcus 등이 포함된다. [1] 메탄 생성 고세균인 Methanobrevibacter smithii의 과증식은 intestinal methanogen overgrowth라고 하며, 이는 변비와 관련된 표현형으로 알려져 있다. [2] 또한 small intestinal fungal overgrowth (SIFO)도 확인되었는데, 이는 주로 다양한 Candida 종에 의해 발생하며, 특히 면역저하 환자에서 흔하다. [3]
이러한 다양한 미생물 표현형에서 MO는 2차적인 과정, 즉 정상적으로 미생물 과증식을 억제하는 생리적 방어기전 중 하나 이상이 실패한 결과로 발생한다. 이러한 방어기전에는 위산 분비, 담즙 및 췌장액, 장 운동성, 분비성 IgA와 같은 항균 펩타이드, 회맹판 기능 등이 포함된다. [4] 이러한 요인 중에서도 위산은 특히 중요한 역할을 하는데, proton pump inhibitor (PPI) 사용과 MO 사이의 잘 알려진 연관성이 이를 뒷받침한다. [5–8]
Achlorhydria(무위산증)는 위산 생성이 없거나 현저히 감소한 상태를 의미하며, 여러 생리적 과정을 교란하여 위장관 내 MO를 유발할 수 있다. 정상적으로 위산은 강력한 항균 방어 역할을 하여 섭취된 세균이 소장으로 도달하기 전에 제거한다. 그러나 위산이 감소하면 이러한 보호 효과가 감소하여 세균이 살아남아 소장으로 이동하게 되고, 산도가 낮은 환경에서 세균이 증식하고 정착할 수 있게 된다. [9] 또한 위산 감소는 소화 효소와 담즙의 활성화를 저하시켜, 이들 역시 항균 작용이 감소한다. 위산 부족은 위 배출을 지연시켜 세균이 위와 소장에서 더 오래 증식할 수 있는 시간을 제공한다. [10] 이러한 요인들이 결합되어 결국 MO가 발생하기 쉬운 환경을 형성하게 된다.
Autoimmune atrophic gastritis는 위의 산을 분비하는 벽세포(parietal cell)를 면역 반응이 공격하는 만성 면역매개 염증 질환으로, 만성 염증과 위 점막 위축을 유발하며, 벽세포 파괴로 인해 무위산증이 발생한다. [11] 이러한 무위산증 환경에서는 autoimmune atrophic gastritis 환자에서 MO 발생 위험이 증가할 수 있으나, 이에 대해서는 충분한 연구가 이루어지지 않았다. 또한 MO 진단과 관련하여 진단 방법(호기 검사 vs 장 흡인 검사), 호기 검사에서 lactulose vs glucose 사용, 장 흡인 검사에서 진단 기준을 >10⁵ CFU/mL로 할지 또는 >10³ CFU/mL로 할지에 대한 논란이 있어, autoimmune atrophic gastritis 환자에서 MO의 특성을 이해할 필요성이 다시 제기되고 있다.
본 연구의 목적은 MO 검사를 시행한 autoimmune atrophic gastritis 환자에서 MO의 빈도를 보고하고, 또한 autoimmune atrophic gastritis와 비위축성 만성 위염(non-atrophic chronic gastritis) 환자 간의 MO 빈도를 비교하는 것이다.
Materials and methods
본 연구는 MO 검사를 시행한 autoimmune atrophic gastritis 환자들을 대상으로 한 후향적 연구(retrospective study)이다. 우리는 Mayo Clinic에서 MO 검사를 시행한 모든 환자들의 대규모 데이터베이스를 활용하였다. MO 검사는 esophagogastroduodenoscopy (EGD)를 시행하면서 단일 루멘 카테터(single lumen catheter; Hobbs Medical, Inc)를 이용하여 소장 흡인액 배양(intestinal aspirate culture)을 시행한 경우 또는 glucose 또는 lactulose hydrogen/methane breath test를 시행한 경우를 포함하였다. 이 두 가지 진단 방법에 대한 자세한 프로토콜은 Supplementary Digital Material 1 (Supplementary Text File 1)에 추가로 설명되어 있다.
--------------------------------------------------------------------------------------------------
<Supplementary Text file 1. Microbial overgrowth diagnostic testing>
우리 기관에서 시행하는 호기 검사(breath testing) 프로토콜은 환자가 기질(substrate)인 lactulose 10g 또는 glucose 75g을 섭취한 후, 기저치에서 시작하여 15분 간격으로 90분까지 호기 내 수소(hydrogen)와 메탄(methane) 농도를 측정하는 방식으로 진행된다. 단, 검사 양성 기준을 이미 충족한 경우에는 60분에서 검사를 종료할 수 있다.
식도위십이지장내시경(esophagogastroduodenoscopy) 중 소장 흡인액 배양(intestinal aspirate culture)을 얻기 위해, 내시경을 최소 십이지장 제2부까지 진입시키며 세척(washing)이나 흡인(suction)은 피한다. 이후 흡인 카테터(Hobbs Medical, Inc, 멸균 240 cm 길이, 직경 2.3 mm의 single-lumen catheter)를 삽입하여 가능한 한 장 내 깊숙이 전진시킨다. 그 다음 보조자가 장액(enteric fluid)을 흡인한다. 이 액체는 미생물 검사실로 보내지며, 다음 배지에서 배양된다.
aerobic trypticase soy agar with blood
eosin methylene blue agar
anaerobic CDC blood agar
phenylethyl alcohol agar
Laked blood agar with kanamycin and vancomycin
결과는 CFU/mL (colony forming units per mL)로 보고되며 다음과 같이 분류된다.
none
< 1,000
1,000–10,000
10,000–100,000
> 100,000
또한 호기성(aerobic)과 혐기성(anaerobic) 균의 비율도 함께 보고된다. 특정 미생물은 한 종류 이상의 균이 우세하거나, 특정 균이 100,000 CFU/mL 이상인 경우에 보고된다.
------------------------------------------------------------------------------------------------
우리는 이후 ICD-9 및 ICD-10 진단 코드 중 chronic atrophic gastritis에 해당하는 코드를 이용하여 autoimmune atrophic gastritis 환자들을 선별하였다. 확인된 각 환자의 의무기록(chart)은 전문 위장관 병리학자(expert gastrointestinal pathologist)가 판독한 표준 조직학적 기준에 근거하여 autoimmune atrophic gastritis 진단이 맞는지 확인하기 위해 수작업으로 검토되었다.[11] 조직학적으로 autoimmune atrophic gastritis가 확인되지 않은 환자는 제외하였다. 또한 PPI 사용 여부, 복부 수술 병력, 위 배출 검사(gastric emptying scintigraphy) 결과도 함께 수집하였다.
소장 흡인액 배양 결과는 세균 수가 ≥10³ CFU/mL 또는 ≥10⁵ CFU/mL인 경우 각각 양성으로 정의하여 threshold 분석(threshold analysis)을 시행하였다. Small intestinal fungal overgrowth (SIFO)는 효모(yeast) 또는 진균(fungi)이 ≥10³ CFU/mL 이상 검출된 경우로 정의하였다.
호기 검사는 North American Consensus 기준에 따라 판정하였다. 즉, 기저치 대비 호기 수소 농도가 90분 이내에 ≥20 ppm 증가하거나, 또는 호기 메탄 농도가 어느 시점에서든 ≥10 ppm 이상인 경우 양성으로 판정하였다.
마지막으로 우리는 autoimmune atrophic gastritis 환자와 non-autoimmune, non-Helicobacter pylori 비위축성 위염(non-atrophic gastritis) 환자 간의 MO 발생률을 비교하였다. 비위축성 위염 환자는 ICD 코드를 이용하여 선별하였으며, autoimmune atrophic gastritis와 H. pylori 감염이 모두 없는 환자임을 확인하였다. 이후 통계적 검정력을 높이기 위해 연령 및 성별을 매칭한 대조군(age- and sex-matched controls)을 이용한 추가 분석을 시행하였다. 각 autoimmune atrophic gastritis 환자당 연령과 성별이 일치하는 대조군 환자 2명을 무작위로 선택하여 2:1 비율로 분석을 수행하였다.
통계 분석은 Chi-square test와 logistic regression을 포함하여 Microsoft Excel과 Bluesky Statistics를 사용하여 수행하였다.
본 연구는 Mayo Clinic Institutional Review Board의 승인을 받았으며, 해당 규정에 따라 수행되었다(승인번호 23-012480). 연구 설계 특성상(환자 정보 비식별화 및 환자 접촉 없음) 구두 또는 서면 동의는 필요하지 않았으나, 의무기록 연구(chart review research)에 대한 사전 동의가 있는 환자만 포함하였다. 환자와의 직접적인 접촉은 없었다.
Results
인구학적 및 임상 정보는 Table I에 요약되어 있다.
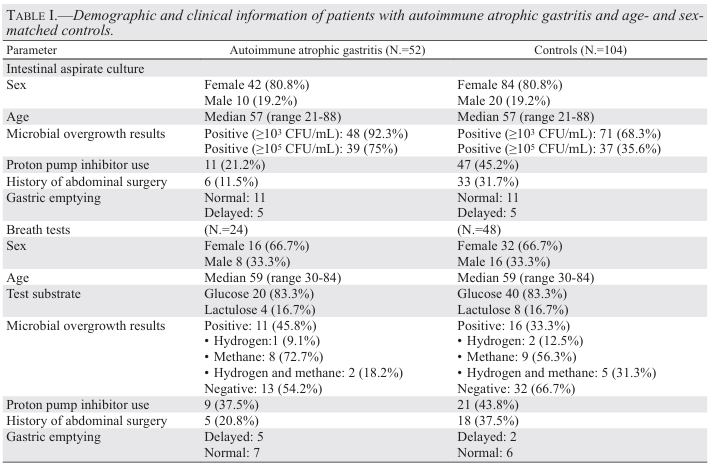
우리는 EGD 중 소장 흡인액 배양(intestinal aspirate culture)을 시행한 autoimmune atrophic gastritis 환자 52명을 확인하였다(여성 42명, 남성 10명, 중앙 연령 57세). 이 환자들 중 48명(92.3%)은 ≥10³ CFU/mL 기준에서 SIBO 진단 기준을 충족하였고, 39명(75%)은 ≥10⁵ CFU/mL 기준에서 SIBO 진단 기준을 충족하였다. SIFO는 4명(7.7%)에서 진단되었으며, 모두 SIBO와 동시에 존재하였다.
양성 흡인액 배양 결과 중에서
42명에서는 호기성 및 혐기성 세균이 함께 배양되었고,
5명에서는 호기성 세균 및/또는 통성 혐기성 세균만 배양되었으며,
1명에서는 통성 혐기성 세균만 배양되었다.
오직 혐기성 세균만 배양된 경우는 없었다.
확인된 특정 균종은 다음과 같다.
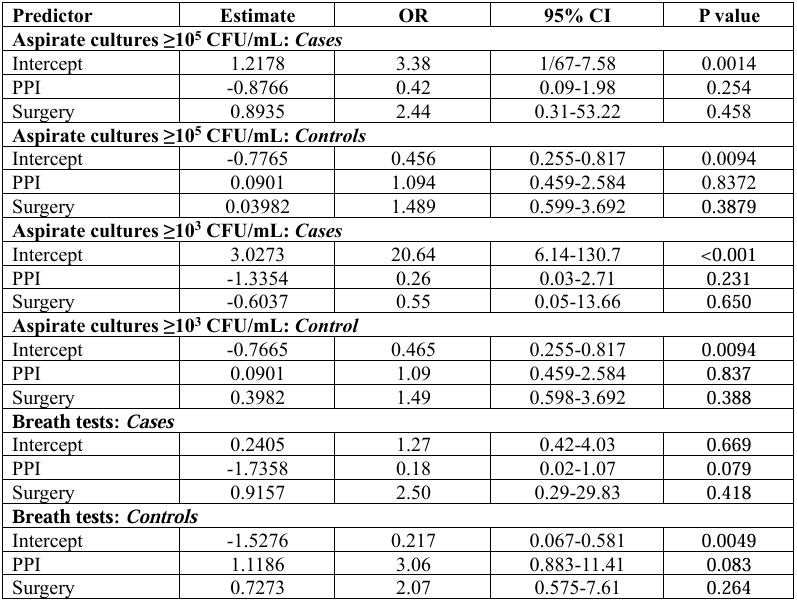
로지스틱 회귀 분석에서 PPI 사용 여부와 복부 수술 병력은 두 가지 진단 기준 모두에서 양성 흡인액 배양과 유의한 연관성을 보이지 않았다(Supplementary Digital Material 2: Supplementary Table I).
우리는 호기 검사를 시행한 autoimmune atrophic gastritis 환자 24명도 확인하였다(여성 16명, 남성 8명, 평균 연령 59.3세). 이 중 20명(83%)은 glucose를 기질로 사용하였고, 나머지 4명(17%)은 lactulose를 사용하였다. 이 24명의 호기 검사 환자 중 11명(45.8%)에서 검사 양성이 확인되었다.
양성 결과의 원인은
수소 증가만으로 양성: 1명(9.1%)
메탄 증가로 양성: 8명(72.7%)
수소와 메탄 모두 증가: 2명(18.2%)
였다. 메탄 상승(수소 동반 여부와 관계없이)이 전체 양성 검사 중 90.9%를 설명하였다.
로지스틱 회귀 분석에서 PPI 사용 여부와 복부 수술 병력은 양성 호기 검사와 유의한 연관성을 보이지 않았다(Supplementary Table I).
Supplementary Table I.—Results of logistic regression analyses assessing the contributions of PPI use and prior abdominal surgery toward results of microbial overgrowth testing.
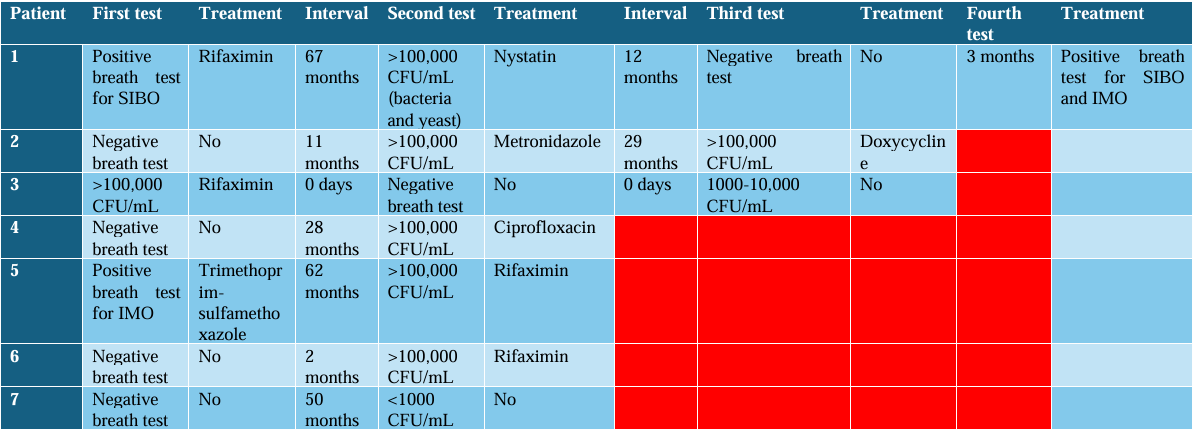
7명의 환자에서는 흡인액 배양 검사와 호기 검사를 모두 시행하였다(Supplementary Digital Material 3: Supplementary Table II).
Supplementary Table II.—Results of MO testing from patients who underwent both testing modalities, including treatments administered.
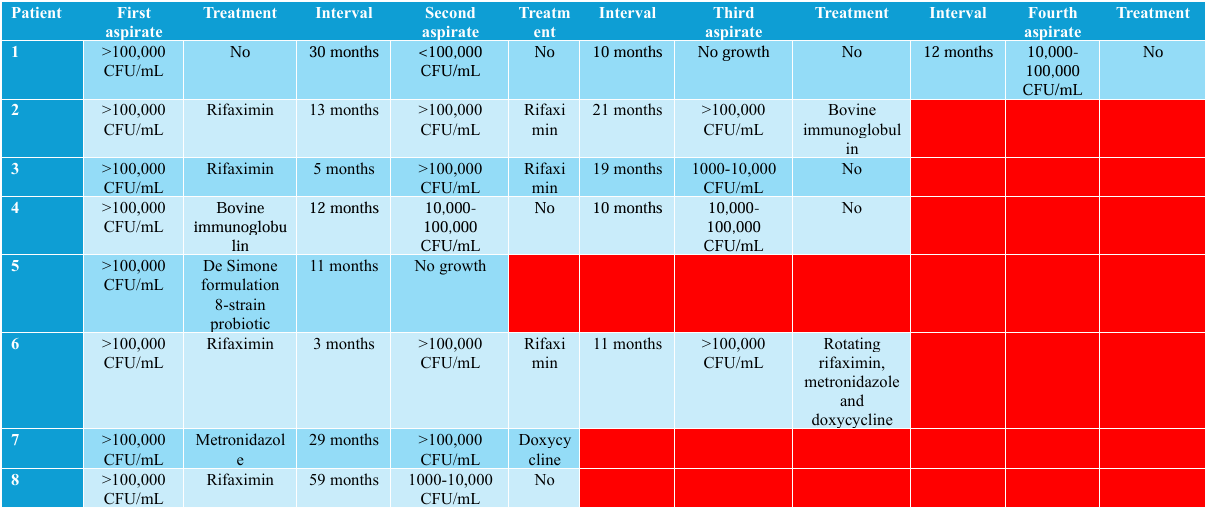
8명의 환자에서는 소장 흡인액 배양 검사가 두 번 이상 시행되었으며, 이 결과는 Supplementary Digital Material 4 (Supplementary Table III)에 제시되어 있다. 이 중 8명 중 7명(87.5%)에서 SIBO가 재발(recurrent SIBO)하였다(특히 6명의 환자 중 1명은 어떠한 치료도 받지 않았다).
Supplementary Table III.—Results of aspirate cultures from patients who had undergone more than one aspirate culture, including treatments administered.
마지막으로 우리는 autoimmune atrophic gastritis와, autoimmune gastritis 또는 Helicobacter pylori 감염과 관련되지 않은 비위축성 만성 위염(chronic gastritis without atrophy) 환자 간 MO 발생률을 비교하였다. 우리는 소장 흡인액 배양을 위해 EGD를 시행한 비위축성 만성 위염 환자 1,634명(평균 연령 52.9세, 남성 30.2%)과 호기 검사를 시행한 환자 593명(평균 연령 53.1세, 남성 22.6%)을 확인하였다. MO 검사 결과와 autoimmune atrophic gastritis와의 비교 결과는 Table II에 제시되어 있다.
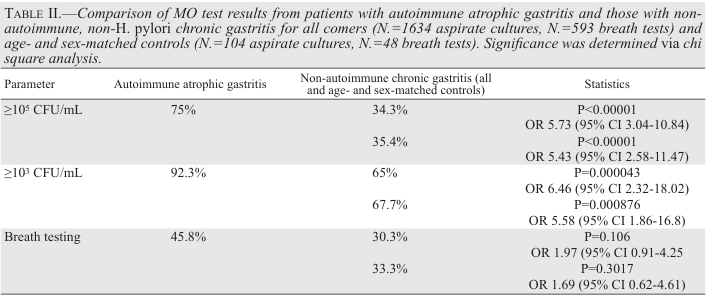
Autoimmune atrophic gastritis 환자들은 두 가지 진단 기준 모두에서 chronic non-autoimmune gastritis 환자보다 양성 SIBO 흡인액 배양 결과의 오즈가 유의하게 높았다.
- ≥10⁵ CFU/mL 기준에서
SIBO 양성률은 75.0% vs 34.3%였으며
(P<0.00001; OR 5.73, 95% CI 3.04–10.84) - ≥10³ CFU/mL 기준에서도
양성률은 92.3% vs 65.0%였다
(P=0.000043; OR 6.46, 95% CI 2.32–18.02)
반면 호기 검사 양성률은 autoimmune atrophic gastritis 환자에서 수치상 더 높았지만 통계적으로 유의하지는 않았다
(45.8% vs 30.3%; P=0.106; OR 1.97, 95% CI 0.91–4.25)
분석을 연령 및 성별 매칭 대조군으로 제한했을 때도 결과는 변하지 않았으며, autoimmune atrophic gastritis에서 SIBO의 오즈가 여전히 유의하게 높았다.
- ≥10⁵ CFU/mL 기준:
75.0% vs 35.4%
(P<0.00001; OR 5.43, 95% CI 2.58–11.47) - ≥10³ CFU/mL 기준:
92.3% vs 67.7%
(P=0.000876; OR 5.58, 95% CI 1.86–16.8)
호기 검사 양성률은 autoimmune atrophic gastritis 군에서 수치상 더 높았으나 통계적으로 유의하지는 않았다
(45.8% vs 33.3%; P=0.3017; OR 1.69; 95% CI 0.62–4.61)
로지스틱 회귀 분석에서는 PPI 사용 여부와 복부 수술 병력은 두 가지 진단 기준에서의 양성 흡인액 배양 결과나 양성 호기 검사와 유의한 연관성을 보이지 않았다 (Supplementary Table I).
Discussion
본 연구는 현재까지 autoimmune atrophic gastritis에서 MO를 기술한 가장 큰 연구이다. 위장관 증상 평가를 위해 소장 흡인액 배양 검사를 시행한 autoimmune atrophic gastritis 환자에서, SIBO는 ≥10⁵ CFU/mL 기준에서 75%, ≥10³ CFU/mL 기준에서 92.3%로 확인되었다. 호기 검사로 진단했을 경우에는 45.8%가 양성이었다. Autoimmune atrophic gastritis는 autoimmune atrophic gastritis나 Helicobacter pylori 감염에 의하지 않은 만성 위염 환자를 연령 및 성별 매칭하여 비교했을 때, 양성 흡인액 배양 결과의 오즈가 유의하게 높았으며 약 5배 이상의 증가를 보였다. 또한 재발성 SIBO도 흔하게 관찰되었다.
소장 흡인액 배양에서 SIBO의 최적 진단 기준에 대해서는 여전히 연구가 진행 중이지만, ≥10³ CFU/mL 기준이 특정 위장관 증상, 특징적인 dysbiosis, 그리고 대사체(metabolomic) 프로파일과 연관된다는 근거가 증가하고 있다[1]. 어떤 기준을 사용하더라도, 소장 흡인액을 얻은 autoimmune atrophic gastritis 환자에서 SIBO의 유병률은 매우 높은 것이 분명하다. 배양 결과는 이전 SIBO 시퀀싱 연구 결과와 일치하며, Enterobacteriaceae 우세와 Klebsiella 및 Escherichia와 같은 disruptor taxa의 존재를 보여준다[1]. 또한 반복 흡인액 배양을 시행한 환자 중 83.3%에서 SIBO가 재발하였다.
SIFO는 본 코호트에서 드물었으며(7.7%), 항상 SIBO와 함께 발생하였다. SIBO의 유병률이 매우 높은데도 SIFO가 드문 것은 위산이 장내 진균량 조절에 주요한 역할을 하지 않을 가능성을 시사한다. 이 가설은 쥐 실험에서 famotidine 전처치 후 Candida albicans를 위에 접종해도 위 정착에 영향을 주지 않았다는 연구에 의해 뒷받침된다[12]. 그러나 인간 연구에서는 histamine-2 receptor antagonist와 PPI를 사용하는 환자에서 위 내 Candida albicans 양이 증가한 것으로 보고되었다[13]. 또한 PPI 사용은 SIFO와도 관련이 있다[14].
이전 연구에서 autoimmune atrophic gastritis에서 MO를 직접적으로 연구한 것은 없지만, achlorhydria 상태에서 장내 미생물에 대한 연구는 존재한다. 1969년 Drasar, Shiner, McLeod의 연구에서는 achlorhydria 환자와 건강 대조군의 장내 미생물을 비교하였다. 건강 대조군에서는 일반적으로 105 CFU/mL 이하였으며, Lactobacillus, Streptococcus, Enterococcus가 주로 존재하는 다양한 균 구성을 보였다. 반면 achlorhydria 환자에서는 소장 내 세균 수가 유의하게 증가하여 일반적으로 106–107 CFU/mL였다. 이 군에서 흔한 균은 Bacteroides, Clostridia, Escherichia coli였다[15]. 이 연구는 achlorhydria가 dysbiosis와 MO 모두와 연관됨을 보여주었다.
이후 Saltzmann 등의 1994년 연구에서는 위축성 위염 또는 PPI 복용 중인 노인 17명을 대상으로 MO를 조사하였으며, lactulose 또는 glucose 호기 검사에서 단 1명만 이상 결과를 보였다[16]. 그러나 이후 여러 연구에서 PPI 사용과 SIBO 사이의 연관성이 보고되었으며, 여러 메타분석도 이를 지지한다. Lo와 Chan(2013)은 흡인액 배양 기준에서는 PPI 사용이 MO 위험 증가와 관련 있지만 호기 검사 기준에서는 그렇지 않다는 메타분석 결과를 보고하였다[6]. Su 등(2018)도 호기 검사 또는 흡인액 배양 기준 모두에서 MO 위험이 중등도 증가한다고 보고하였다[7]. 최근 건강한 자원자를 대상으로 한 중재 연구에서는 pantoprazole을 7일간 복용 후 7.8%에서 glucose 호기 검사 양성이 나타났으며, MO가 발생한 사람에서는 복부 팽만과 가스 증가가 관찰되었다[8]. 기존 PPI 사용자 연구에 비해 본 연구에서 MO 유병률이 더 높은 것은 기전적으로 설명 가능하다. 왜냐하면 autoimmune atrophic gastritis에서는 벽세포의 광범위하고 비가역적인 파괴로 인해 PPI에 의한 가역적 H+/K+ ATPase 억제보다 훨씬 심한 achlorhydria가 발생하기 때문이다.
호기 검사를 시행한 환자에서는 45.8%만 양성으로 나타났으며, 이는 보수적인 흡인액 기준보다도 훨씬 낮은 유병률이다. 또한 두 검사를 모두 시행한 환자에서 71%는 흡인액 배양은 양성이지만 호기 검사는 음성으로 나타나 두 검사 간 불일치가 존재하였다. 이러한 결과는 위축성 위염 환자에서 호기 검사의 민감도가 낮을 수 있음을 시사한다. (다른 설명으로는 호기 검사가 제균 확인을 위해 시행되었을 가능성이 있으나, 반복 흡인액 배양에서 대부분 지속적으로 양성이었기 때문에 이는 가능성이 낮다.) 이 결과는 achlorhydria 환자에서 호기 검사 양성이 거의 없었던 Saltzmann 등의 연구와도 일치한다[16]. 이러한 낮은 민감도는 수소나 메탄을 생성하지 않는 세균의 존재 때문일 수도 있고(그러나 배양 결과에서는 가스 생성 균과 유사한 균이 확인되었다), 약물 등의 교란 요인 때문일 수도 있다.
또한 흡인액 배양은 gold standard 진단법이지만 위양성(false positive)의 가능성도 있다. 특히 부적절한 기술을 사용할 경우 구인두 균 오염이 발생할 수 있으며, 특히 비멸균 single lumen catheter를 사용할 때 그렇다. 우리 기관에서는 이러한 카테터를 사용하고 있으며, 우리 기관 연구에서는 이 방법으로 얻은 샘플의 최대 20%가 오염되어 위양성으로 나타난다고 보고하였다[17]. 이러한 오염은 매우 높은 양성률과 배양과 호기 검사 간 불일치를 일부 설명할 수 있다. 그러나 배양에서 확인된 특정 균들이 double lumen sterile catheter를 사용한 연구에서 MO 원인균으로 확인된 균과 일치한다는 점은 이러한 설명을 부분적으로 반박한다[1,18,19]. 또한 흡인액 배양은 너무 근위부에서 채취할 경우 소장의 더 원위부에서 발생한 MO를 놓쳐 위음성(false negative)이 될 수도 있다[20].
이러한 한계에도 불구하고, 흡인액 배양은 여전히 gold standard 진단법으로 간주된다. 이는 호기 검사가 여러 변수로 인해 위양성과 위음성 모두 발생할 수 있기 때문이다[21,22]. 실제로 glucose 호기 검사 연구에서 scintigraphic tracer를 이용해 기질의 위치를 확인했을 때 양성 호기 검사 중 48%가 실제로는 대장에서 발효된 위양성이었다[23]. Lactulose를 사용한 연구에서는 수소 증가 시점에 88%에서 이미 맹장에 기질이 도달해 있었다[24]. 호기 검사는 장비 문제, 환자의 호기 샘플 문제, 운동, 약물(항생제, 장운동촉진제, 완하제), 장운동 장애 등에 의해 위음성이 될 수 있다. 특히 마지막 요인은 본 연구에서 중요한데, autoimmune atrophic gastritis와 achlorhydria는 위 배출 지연과 연관되어 있기 때문이다[25,26]. Lactulose는 특히 민감도와 특이도가 낮아 신속한 장 통과가 있는 경우 신뢰도가 낮다. 우리 기관에서는 대부분 glucose를 사용하며, 본 연구에서도 83%가 glucose 호기 검사였다. 이는 검사 결과의 신뢰도를 높이지만, glucose 호기 검사 역시 한계가 존재한다.
최근에는 황산염 환원 세균(Desulfovibrio 등)의 과증식으로 인한 intestinal sulfide overproduction라는 MO의 또 다른 표현형이 제시되었으며, 이는 설사와 관련된다[27]. Hydrogen sulfide는 일반적인 hydrogen/methane 호기 검사에서 측정되지 않는다. 만약 hydrogen sulfide와 autoimmune atrophic gastritis 사이에 연관성이 있다면(수소 황화물은 위 점막 항상성에 영향을 미치는 것으로 알려져 있음)[28], 현재의 호기 검사는 이러한 MO 사례를 놓칠 수 있다. 결국 MO의 두 진단 방법 모두 위양성과 위음성이 발생할 수 있는 한계가 있으며, autoimmune atrophic gastritis 환자에서 MO 검사 결과를 해석할 때 이러한 점을 고려해야 한다.
흥미롭게도 autoimmune atrophic gastritis 환자의 양성 호기 검사 중 90.9%는 메탄 증가(단독 72.7%, 수소 동반 18.2%)로 설명되었다. Intestinal methanogen overgrowth는 변비와 관련되며[2], 소장 및 대장 운동 저하의 결과일 수 있다[29]. Autoimmune gastritis에서는 위 배출 지연이 보고되어 있으며[25,26], 이는 자율신경계 기능 이상 때문일 수 있다. 그러나 소장과 대장 운동 이상은 아직 연구되지 않았다. 자율신경 이상이 장 통과를 지연시켜 IMO 위험을 증가시킬 가능성이 있다.
흡인액 배양 비교 분석에서 autoimmune atrophic gastritis는 non-autoimmune chronic gastritis보다 SIBO와 훨씬 더 강하게 연관되었으며, 두 진단 기준 모두에서 약 5배 이상의 위험 증가를 보였다. 그러나 이러한 OR 해석에서는 autoimmune atrophic gastritis 환자 수가 적어 신뢰구간이 넓다는 점을 고려해야 한다. 반면 호기 검사에서는 autoimmune atrophic gastritis에서 수치상 더 높았지만 통계적으로 유의하지 않았다. 두 군 모두에서 호기 검사 양성률은 배양 양성률보다 훨씬 낮았다.
흡인액 배양과 호기 검사 간 낮은 일치도는 이전 연구에서도 보고된 바 있다. 40명을 대상으로 한 연구에서는 공장 흡인액 배양 양성 35%, lactulose 호기 검사 45%, glucose 호기 검사 30%였으며, 특히 lactulose 검사와 배양 결과의 일치도가 낮았다[30]. 139명을 대상으로 한 연구에서도 배양 양성 44.6%, glucose 호기 검사 양성 27.3%, 진단 일치도 65.5%였다[31]. 이러한 낮은 일치도는 흡인액 배양의 구인두 오염에 의한 위양성과 호기 검사 위음성 때문일 가능성이 있다[17,22].
전반적으로 흡인액 배양은 EGD와 진정이 필요하고 비용이 높아 일부 환자에서는 시행이 어렵지만, autoimmune atrophic gastritis 환자에서는 정기적으로 intestinal metaplasia 및 위암 선별을 위해 EGD를 시행하는 경우가 많기 때문에, 이러한 환자에서는 흡인액 배양을 시행하는 것이 합리적이다. 구인두 오염으로 인한 위양성을 줄이기 위해 sterile double lumen catheter 사용을 고려해야 한다[32].
Limitations of the study
본 연구에는 몇 가지 한계가 있다. 첫째, 본 연구는 후향적 연구(retrospective study)이다. 증례의 식별은 ICD-9 및 ICD-10 코드를 이용하여 이루어졌는데, autoimmune gastritis 자체에는 고유한 진단 코드가 존재하지 않는다. 따라서 다른 코드로 분류된 경우 일부 증례가 누락되었을 가능성이 있다. 본 연구는 autoimmune atrophic gastritis 환자에서 MO의 유병률(prevalence)을 평가하기 위해 설계된 연구가 아니다(이는 대조군을 포함한 연구에서만 가능하다). 대신 우리는 MO 검사를 시행한 autoimmune atrophic gastritis 환자에서 MO의 빈도(frequency)를 평가하였다.
또한 본 연구에서는 MO 검사를 시행하게 된 적응증이나 환자의 임상 결과(clinical outcomes)를 평가하지 않았다. 이는 해당 정보가 전자의무기록(electronic health record)에 일관된 형식으로 기록되어 있지 않아 데이터 추출이 어려웠기 때문이다. MO 검사를 시행한 이유를 직접 분석하지는 않았지만, 아마도 지속적인 위장관 증상 때문이었을 것으로 추정된다. 우리 기관의 경험에 따르면 대부분의 흡인액 배양 검사는 설사 평가를 위해 시행된다. 따라서 본 연구 대상은 모든 autoimmune atrophic gastritis 환자를 대표한다고 보기 어렵고, 이 질환에서 MO의 실제 유병률을 과대평가했을 가능성이 있다.
마지막으로, 앞서 상세히 논의한 바와 같이 모든 MO 진단 방법은 위양성(false positive)과 위음성(false negative)의 가능성이 있다. 우리 기관의 흡인액 배양 채취 방법은 최대 20%에서 위양성을 초래할 수 있어 SIBO를 과대평가했을 가능성이 있다[17]. 마찬가지로 호기 검사 역시 여러 제한점이 있으며, 이는 다른 문헌에서 광범위하게 논의된 바 있다[21,22].
향후 연구에서는 autoimmune atrophic gastritis 환자에서 MO 존재 여부를 전향적으로(prospectively) 평가하고, gold-standard 진단 방법을 사용하며, 또한 특정 증상이 MO를 예측하는지 여부도 함께 평가해야 할 것이다.
Conclusions
Autoimmune atrophic gastritis 환자에서 소장 흡인액 배양을 동반한 EGD를 시행한 경우 SIBO는 흔하게 관찰되었으며, ≥10³ CFU/mL 기준에서는 92.3%, ≥10⁵ CFU/mL 기준에서는 75%의 빈도를 보였다. 반복 흡인액 배양을 시행한 환자 중에서는 83.3%에서 SIBO가 재발하였다. SIFO는 7.7%로 매우 드물었으며 항상 SIBO와 함께 발생하였다. 호기 검사 양성은 45.8%에서 관찰되었으며, 대부분의 경우는 intestinal methanogen overgrowth에 의한 것이었다.
Autoimmune atrophic gastritis 환자는 non-autoimmune chronic gastritis 환자에 비해 두 가지 진단 기준 모두에서 SIBO 흡인액 배양 양성일 가능성이 5배 이상 높았다. 본 연구 결과는 MO 진단 방법의 검사 특성이 완전하지 않다는 한계가 있다. 임상가는 지속적인 증상이 있는 autoimmune atrophic gastritis 환자에서 MO의 가능성을 항상 고려해야 한다.
<Abstract>
Background: Autoimmune atrophic gastritis causes achlorhydria, which may predispose to gastrointestinal microbial overgrowth (MO). We sought to evaluate the association between autoimmune atrophic gastritis and MO.
Methods: From a database of patients at our institution who had undergone MO testing (via intestinal aspirate culture or glucose or lactulose hydrogen/methane breath testing), we identified patients with autoimmune atrophic gastritis via ICD codes. We then confirmed that these patients had a histologically confirmed diagnosis. Finally we queried the electronic health record to identify patients with non-atrophic chronic gastritis who had undergone MO testing.
Results: We identified 52 patients with autoimmune atrophic gastritis who underwent aspirate culture; 48 (92.3%) met criteria for small intestinal bacterial overgrowth (SIBO) at a threshold of ≥103 CFU/mL, and 39 (75%) at ≥105 CFU/mL. Among patients who had multiple aspirates, 83.3% had recurrent SIBO. Among 24 patients who underwent breath testing, 11 (45.8%) tested positive, primarily reflecting intestinal methanogen overgrowth. A notable discordance was observed among seven patients who underwent both testing modalities, with five patients having a positive culture but negative breath test. Finally, comparing MO results from patients with autoimmune atrophic gastritis to those with non-atrophic chronic gastritis identified significantly higher test positivity in autoimmune atrophic gastritis (75% vs. 34.3% at ≥105 CFU/mL, P<0.00001; 92.3% vs. 65%, P=0.000043), but not for breath tests (45.8% vs. 30.3%, P=0.106).
Conclusions: MO is common among symptomatic patients with autoimmune atrophic gastritis, and intestinal aspirate culture identifies more positive cases than breath testing in this population. Findings are subject to selection bias and the inherent constraints of both MO testing modalities, and require confirmation with prospective studies.
References
1. leite G, rezaie a, Mathur r, Barlow GM, rashid M, Hosseini a, et al.; REIMAGINE Study Group. Defining Small In testinal Bacterial overgrowth by Culture and High through put Sequencing. Clin Gastroenterol Hepatol 2024;22:259–70.
2. Mehravar s, takakura W, Wang J, Pimentel M, Nasser J, Rezaie A. Symptom Profile of Patients With Intestinal Metha nogen overgrowth: a systematic review and Meta-analysis. Clin Gastroenterol Hepatol 2025;23:1111–1122.e9.
3. lim J, rezaie a. irritable Bowel syndrome-like symp toms in Quiescent Inflammatory Bowel Disease: A Practical approach to Diagnosis and treatment of organic Causes. Dig Dis Sci 2023;68:4081–97.
4. Pimentel M, saad rJ, long MD, rao ss. aCG Clinical Guideline: small intestinal Bacterial overgrowth. am J Gas troenterol 2020;115:165–78.
5. lombardo l, Foti M, ruggia o, Chiecchio a. increased incidence of small intestinal bacterial overgrowth during proton pump inhibitor therapy. Clin Gastroenterol Hepatol 2010;8:504–8.
6. lo WK, Chan WW. Proton pump inhibitor use and the risk of small intestinal bacterial overgrowth: a meta-analysis. Clin Gastroenterol Hepatol 2013;11:483–90.
7. su t, lai s, lee a, He X, Chen s. Meta-analysis: proton pump inhibitors moderately increase the risk of small intesti nal bacterial overgrowth. J Gastroenterol 2018;53:27–36.
8. Durán-rosas C, Priego-Parra Ba, Morel-Cerda e, Mer cado-Jauregui la, aquino-ruiz Ca, triana-romero a, et al. incidence of small intestinal Bacterial overgrowth and symptoms after 7 Days of Proton Pump inhibitor Use: a Study on Healthy Volunteers. Dig Dis Sci 2024;69:209–15.
9. Bohm M, shin a, teagarden s, Xu H, Gupta a, siwiec r, et al. Risk Factors Aassociated With Upper Aerodigestive Tract or Coliform Bacterial Overgrowth of the Small Intestine in Symptomatic Patients. J Clin Gastroenterol 2020;54:150–7.
10. Tucci A, Poli l, Biasco G, Paparo GF, Tosetti C, Fusaroli P, et al. Helicobacter pylori infection and gastric function in patients with fundic atrophic gastritis. Dig Dis sci 2001;46:1573–83.
11. Lenti MV, Rugge M, Lahner E, Miceli E, Toh BH, Genta RM, et al. Autoimmune gastritis. Nat Rev Dis Primers 2020;6:56.
12. Greenfield RA, Joyce WA. Gastric colonization with Candida albicans. Mycopathologia 1993;122:1–5.
13. Mottaghi B, emami MH, riahi P, Fahim a, rahimi H, Mohammadi r. Candida colonization of the esophagus and gastric mucosa; a comparison of patients taking proton pump inhibitors and those taking histamine receptor antagonist drugs. Gastroenterol Hepatol Bed Bench 2021;14:349–55.
14. Jacobs C, Coss adame e, attaluri a, Valestin J, rao ss. Dysmotility and proton pump inhibitor use are independent risk factors for small intestinal bacterial and/or fungal over growth. Aliment Pharmacol Ther 2013;37:1103–11.
15. Drasar Bs, shiner M, Mcleod GM. studies on the in testinal flora. I. The bacterial flora of the gastrointestinal tract in healthy and achlorhydric persons. Gastroenterology 1969;56:71–9.
16. saltzman Jr, Kowdley KV, Pedrosa MC, sepe t, Gol ner B, Perrone G, et al. Bacterial overgrowth without clinical malabsorption in elderly hypochlorhydric subjects. Gastroen terology 1994;106:615–23.
17. Cangemi DJ, lacy Be, Wise J. Diagnosing small in testinal Bacterial overgrowth: a Comparison of lactu lose Breath tests to small Bowel aspirates. Dig Dis sci 2021;66:2042–50.
18. Barlow Jt, leite G, romano ae, sedighi r, Chang C, Celly s, et al. Quantitative sequencing clarifies the role of dis ruptor taxa, oral microbiota, and strict anaerobes in the human small-intestine microbiome. Microbiome 2021;9:214.
19. Villanueva-Millan MJ, leite G, Wang J, Morales W, Par odi G, Pimentel Ml, et al. Methanogens and Hydrogen sul f ide Producing Bacteria Guide Distinct Gut Microbe Profiles and irritable Bowel syndrome subtypes. am J Gastroenterol 2022;117:2055–66.
20. shah eD. Breath test or Duodenal aspirate for small in testinal Bacterial overgrowth: still No Breath of Fresh air. Dig Dis Sci 2021;66:1770–1.
21. Kashyap P, Moayyedi P, Quigley eM, simren M, Van ner s. Critical appraisal of the siBo hypothesis and breath testing: a clinical practice update endorsed by the european society of neurogastroenterology and motility (esNM) and the american neurogastroenterology and motility society (ANMS). Neurogastroenterol Motil 2024;36:e14817.
22. Damianos Ja, Matar a, Halawi H. Gas-tly interpreta tions: a Case-Based approach to the Nuances of siBo Breath Testing. Curr Gastroenterol Rep 2025;27:30.
23. lin eC, Massey Bt. scintigraphy Demonstrates High rate of False-positive results From Glucose Breath tests for small Bowel Bacterial overgrowth. Clin Gastroenterol Hepa tol 2016;14:203–8.
24. yu D, Cheeseman F, Vanner s. Combined oro-caecal scintigraphy and lactulose hydrogen breath testing demon strate that breath testing detects oro-caecal transit, not small intestinal bacterial overgrowth in patients with iBs. Gut 2011;60:334–40.
25. tosetti C, stanghellini V, tucci a, Poli l, salvioli B, Bi asco G, et al. Gastric emptying and dyspeptic symptoms in patients with nonautoimmune fundic atrophic gastritis. Dig Dis Sci 2000;45:252–7.
26. Kalkan Ç, soykan i, soydal Ç, Özkan e, Kalkan e. Assessment of Gastric emptying in Patients with autoimmune Gastritis. Dig Dis Sci 2016;61:1597–602.
27. Villanueva-Millan MJ, leite G, Mathur r, rezaie a, Fajardo CM, de Freitas Germano J, et al. Hydrogen Sulfide and Methane on Breath test Correlate with Human small in testinal Hydrogen Sulfide Producers and Methanogens. Dig Dis Sci 2025;70:3846–56.
28. Fiorucci s, Distrutti e, Cirino G, Wallace Jl. the emerg ing roles of hydrogen sulfide in the gastrointestinal tract and liver. Gastroenterology 2006;131:259–71.
29. Talamantes S, Steiner F, Spencer S, Neshatian l, Sonu I. Intestinal Methanogen Overgrowth (IMO) is associated with Delayed small Bowel and Colonic transit time (TT) on the Wireless Motility Capsule (WMC). Dig Dis sci 2024;69:3361–8.
30. Tang S, Li J, Ma J, Li Y, Li Y, Wan J, et al. Comparison of jejunal aspirate culture and methane and hydrogen breath test in the diagnosis of small intestinal bacterial overgrowth. ir J Med Sci 2024;193:699–703.
31. Erdogan A, Rao SS, Gulley D, Jacobs C, Lee YY, Badger C. small intestinal bacterial overgrowth: duodenal as piration vs glucose breath test. Neurogastroenterol Motil 2015;27:481–9.
32. Karunaratne TB, Sharma A, Rao SS. small-bowel aspi ration during upper esophagogastroduodenoscopy: rao tech nique. VideoGIE 2020;6:152–4.


Damianos JA, Jin M, Ospina-Velasquez L, Chowla N, Wang XJ.
Minerva Gastroenterol (Torino). 2026 Jun;72(2):160-168. doi: 10.23736/S2724-5985.26.04066-0.
Introduction
Small intestinal microbial overgrowth (MO)는 소장 내 미생물(세균, 바이러스, 진균, 고세균)이 과도하게 증가함으로써 발생하는 위장관 증상의 증후군이다. 소장에서 비정상적으로 높은 세균 밀도가 존재하는 상태를 small intestinal bacterial overgrowth (SIBO)라고 하며, 이는 복부 불편감, 복부 팽만, 가스 증가, 배변 습관 변화와 같은 위장관 증상을 유발할 수 있다. SIBO는 처음에는 장 정체(intestinal stasis)와 해부학적 구조 변화가 있는 환자, 즉 수술로 장 구조가 변형된 환자(과거에는 “blind loop syndrome”이라 불림)에서 발생하는 것으로 알려졌으며, 심한 경우 염증, 융모 위축, 소화 장애, 흡수 장애가 나타났다. 이후 소장 미생물 시퀀싱을 이용한 최근 연구에서는 원인 미생물들이 밝혀지면서 특정 질병 표현형들이 정의되었다. SIBO에서는 Enterobacteriaceae가 우세해지는 경향이 있으며, 정상 장내 세균을 대체하는 이른바 disruptor taxa로 Klebsiella, Escherichia, Enterococcus 등이 포함된다. [1] 메탄 생성 고세균인 Methanobrevibacter smithii의 과증식은 intestinal methanogen overgrowth라고 하며, 이는 변비와 관련된 표현형으로 알려져 있다. [2] 또한 small intestinal fungal overgrowth (SIFO)도 확인되었는데, 이는 주로 다양한 Candida 종에 의해 발생하며, 특히 면역저하 환자에서 흔하다. [3]
이러한 다양한 미생물 표현형에서 MO는 2차적인 과정, 즉 정상적으로 미생물 과증식을 억제하는 생리적 방어기전 중 하나 이상이 실패한 결과로 발생한다. 이러한 방어기전에는 위산 분비, 담즙 및 췌장액, 장 운동성, 분비성 IgA와 같은 항균 펩타이드, 회맹판 기능 등이 포함된다. [4] 이러한 요인 중에서도 위산은 특히 중요한 역할을 하는데, proton pump inhibitor (PPI) 사용과 MO 사이의 잘 알려진 연관성이 이를 뒷받침한다. [5–8]
Achlorhydria(무위산증)는 위산 생성이 없거나 현저히 감소한 상태를 의미하며, 여러 생리적 과정을 교란하여 위장관 내 MO를 유발할 수 있다. 정상적으로 위산은 강력한 항균 방어 역할을 하여 섭취된 세균이 소장으로 도달하기 전에 제거한다. 그러나 위산이 감소하면 이러한 보호 효과가 감소하여 세균이 살아남아 소장으로 이동하게 되고, 산도가 낮은 환경에서 세균이 증식하고 정착할 수 있게 된다. [9] 또한 위산 감소는 소화 효소와 담즙의 활성화를 저하시켜, 이들 역시 항균 작용이 감소한다. 위산 부족은 위 배출을 지연시켜 세균이 위와 소장에서 더 오래 증식할 수 있는 시간을 제공한다. [10] 이러한 요인들이 결합되어 결국 MO가 발생하기 쉬운 환경을 형성하게 된다.
Autoimmune atrophic gastritis는 위의 산을 분비하는 벽세포(parietal cell)를 면역 반응이 공격하는 만성 면역매개 염증 질환으로, 만성 염증과 위 점막 위축을 유발하며, 벽세포 파괴로 인해 무위산증이 발생한다. [11] 이러한 무위산증 환경에서는 autoimmune atrophic gastritis 환자에서 MO 발생 위험이 증가할 수 있으나, 이에 대해서는 충분한 연구가 이루어지지 않았다. 또한 MO 진단과 관련하여 진단 방법(호기 검사 vs 장 흡인 검사), 호기 검사에서 lactulose vs glucose 사용, 장 흡인 검사에서 진단 기준을 >10⁵ CFU/mL로 할지 또는 >10³ CFU/mL로 할지에 대한 논란이 있어, autoimmune atrophic gastritis 환자에서 MO의 특성을 이해할 필요성이 다시 제기되고 있다.
본 연구의 목적은 MO 검사를 시행한 autoimmune atrophic gastritis 환자에서 MO의 빈도를 보고하고, 또한 autoimmune atrophic gastritis와 비위축성 만성 위염(non-atrophic chronic gastritis) 환자 간의 MO 빈도를 비교하는 것이다.
Materials and methods
본 연구는 MO 검사를 시행한 autoimmune atrophic gastritis 환자들을 대상으로 한 후향적 연구(retrospective study)이다. 우리는 Mayo Clinic에서 MO 검사를 시행한 모든 환자들의 대규모 데이터베이스를 활용하였다. MO 검사는 esophagogastroduodenoscopy (EGD)를 시행하면서 단일 루멘 카테터(single lumen catheter; Hobbs Medical, Inc)를 이용하여 소장 흡인액 배양(intestinal aspirate culture)을 시행한 경우 또는 glucose 또는 lactulose hydrogen/methane breath test를 시행한 경우를 포함하였다. 이 두 가지 진단 방법에 대한 자세한 프로토콜은 Supplementary Digital Material 1 (Supplementary Text File 1)에 추가로 설명되어 있다.
--------------------------------------------------------------------------------------------------
<Supplementary Text file 1. Microbial overgrowth diagnostic testing>
우리 기관에서 시행하는 호기 검사(breath testing) 프로토콜은 환자가 기질(substrate)인 lactulose 10g 또는 glucose 75g을 섭취한 후, 기저치에서 시작하여 15분 간격으로 90분까지 호기 내 수소(hydrogen)와 메탄(methane) 농도를 측정하는 방식으로 진행된다. 단, 검사 양성 기준을 이미 충족한 경우에는 60분에서 검사를 종료할 수 있다.
식도위십이지장내시경(esophagogastroduodenoscopy) 중 소장 흡인액 배양(intestinal aspirate culture)을 얻기 위해, 내시경을 최소 십이지장 제2부까지 진입시키며 세척(washing)이나 흡인(suction)은 피한다. 이후 흡인 카테터(Hobbs Medical, Inc, 멸균 240 cm 길이, 직경 2.3 mm의 single-lumen catheter)를 삽입하여 가능한 한 장 내 깊숙이 전진시킨다. 그 다음 보조자가 장액(enteric fluid)을 흡인한다. 이 액체는 미생물 검사실로 보내지며, 다음 배지에서 배양된다.
aerobic trypticase soy agar with blood
eosin methylene blue agar
anaerobic CDC blood agar
phenylethyl alcohol agar
Laked blood agar with kanamycin and vancomycin
결과는 CFU/mL (colony forming units per mL)로 보고되며 다음과 같이 분류된다.
none
< 1,000
1,000–10,000
10,000–100,000
> 100,000
또한 호기성(aerobic)과 혐기성(anaerobic) 균의 비율도 함께 보고된다. 특정 미생물은 한 종류 이상의 균이 우세하거나, 특정 균이 100,000 CFU/mL 이상인 경우에 보고된다.
------------------------------------------------------------------------------------------------
우리는 이후 ICD-9 및 ICD-10 진단 코드 중 chronic atrophic gastritis에 해당하는 코드를 이용하여 autoimmune atrophic gastritis 환자들을 선별하였다. 확인된 각 환자의 의무기록(chart)은 전문 위장관 병리학자(expert gastrointestinal pathologist)가 판독한 표준 조직학적 기준에 근거하여 autoimmune atrophic gastritis 진단이 맞는지 확인하기 위해 수작업으로 검토되었다.[11] 조직학적으로 autoimmune atrophic gastritis가 확인되지 않은 환자는 제외하였다. 또한 PPI 사용 여부, 복부 수술 병력, 위 배출 검사(gastric emptying scintigraphy) 결과도 함께 수집하였다.
소장 흡인액 배양 결과는 세균 수가 ≥10³ CFU/mL 또는 ≥10⁵ CFU/mL인 경우 각각 양성으로 정의하여 threshold 분석(threshold analysis)을 시행하였다. Small intestinal fungal overgrowth (SIFO)는 효모(yeast) 또는 진균(fungi)이 ≥10³ CFU/mL 이상 검출된 경우로 정의하였다.
호기 검사는 North American Consensus 기준에 따라 판정하였다. 즉, 기저치 대비 호기 수소 농도가 90분 이내에 ≥20 ppm 증가하거나, 또는 호기 메탄 농도가 어느 시점에서든 ≥10 ppm 이상인 경우 양성으로 판정하였다.
마지막으로 우리는 autoimmune atrophic gastritis 환자와 non-autoimmune, non-Helicobacter pylori 비위축성 위염(non-atrophic gastritis) 환자 간의 MO 발생률을 비교하였다. 비위축성 위염 환자는 ICD 코드를 이용하여 선별하였으며, autoimmune atrophic gastritis와 H. pylori 감염이 모두 없는 환자임을 확인하였다. 이후 통계적 검정력을 높이기 위해 연령 및 성별을 매칭한 대조군(age- and sex-matched controls)을 이용한 추가 분석을 시행하였다. 각 autoimmune atrophic gastritis 환자당 연령과 성별이 일치하는 대조군 환자 2명을 무작위로 선택하여 2:1 비율로 분석을 수행하였다.
통계 분석은 Chi-square test와 logistic regression을 포함하여 Microsoft Excel과 Bluesky Statistics를 사용하여 수행하였다.
본 연구는 Mayo Clinic Institutional Review Board의 승인을 받았으며, 해당 규정에 따라 수행되었다(승인번호 23-012480). 연구 설계 특성상(환자 정보 비식별화 및 환자 접촉 없음) 구두 또는 서면 동의는 필요하지 않았으나, 의무기록 연구(chart review research)에 대한 사전 동의가 있는 환자만 포함하였다. 환자와의 직접적인 접촉은 없었다.
Results
인구학적 및 임상 정보는 Table I에 요약되어 있다.
우리는 EGD 중 소장 흡인액 배양(intestinal aspirate culture)을 시행한 autoimmune atrophic gastritis 환자 52명을 확인하였다(여성 42명, 남성 10명, 중앙 연령 57세). 이 환자들 중 48명(92.3%)은 ≥10³ CFU/mL 기준에서 SIBO 진단 기준을 충족하였고, 39명(75%)은 ≥10⁵ CFU/mL 기준에서 SIBO 진단 기준을 충족하였다. SIFO는 4명(7.7%)에서 진단되었으며, 모두 SIBO와 동시에 존재하였다.
양성 흡인액 배양 결과 중에서
42명에서는 호기성 및 혐기성 세균이 함께 배양되었고,
5명에서는 호기성 세균 및/또는 통성 혐기성 세균만 배양되었으며,
1명에서는 통성 혐기성 세균만 배양되었다.
오직 혐기성 세균만 배양된 경우는 없었다.
확인된 특정 균종은 다음과 같다.
Klebsiella pneumoniae complex (5명)
Escherichia coli (2명)
혼합 호기성 그람음성 간균 (1명)
로지스틱 회귀 분석에서 PPI 사용 여부와 복부 수술 병력은 두 가지 진단 기준 모두에서 양성 흡인액 배양과 유의한 연관성을 보이지 않았다(Supplementary Digital Material 2: Supplementary Table I).
우리는 호기 검사를 시행한 autoimmune atrophic gastritis 환자 24명도 확인하였다(여성 16명, 남성 8명, 평균 연령 59.3세). 이 중 20명(83%)은 glucose를 기질로 사용하였고, 나머지 4명(17%)은 lactulose를 사용하였다. 이 24명의 호기 검사 환자 중 11명(45.8%)에서 검사 양성이 확인되었다.
양성 결과의 원인은
수소 증가만으로 양성: 1명(9.1%)
메탄 증가로 양성: 8명(72.7%)
수소와 메탄 모두 증가: 2명(18.2%)
였다. 메탄 상승(수소 동반 여부와 관계없이)이 전체 양성 검사 중 90.9%를 설명하였다.
로지스틱 회귀 분석에서 PPI 사용 여부와 복부 수술 병력은 양성 호기 검사와 유의한 연관성을 보이지 않았다(Supplementary Table I).
Supplementary Table I.—Results of logistic regression analyses assessing the contributions of PPI use and prior abdominal surgery toward results of microbial overgrowth testing.
7명의 환자에서는 흡인액 배양 검사와 호기 검사를 모두 시행하였다(Supplementary Digital Material 3: Supplementary Table II).
Supplementary Table II.—Results of MO testing from patients who underwent both testing modalities, including treatments administered.
8명의 환자에서는 소장 흡인액 배양 검사가 두 번 이상 시행되었으며, 이 결과는 Supplementary Digital Material 4 (Supplementary Table III)에 제시되어 있다. 이 중 8명 중 7명(87.5%)에서 SIBO가 재발(recurrent SIBO)하였다(특히 6명의 환자 중 1명은 어떠한 치료도 받지 않았다).
Supplementary Table III.—Results of aspirate cultures from patients who had undergone more than one aspirate culture, including treatments administered.
마지막으로 우리는 autoimmune atrophic gastritis와, autoimmune gastritis 또는 Helicobacter pylori 감염과 관련되지 않은 비위축성 만성 위염(chronic gastritis without atrophy) 환자 간 MO 발생률을 비교하였다. 우리는 소장 흡인액 배양을 위해 EGD를 시행한 비위축성 만성 위염 환자 1,634명(평균 연령 52.9세, 남성 30.2%)과 호기 검사를 시행한 환자 593명(평균 연령 53.1세, 남성 22.6%)을 확인하였다. MO 검사 결과와 autoimmune atrophic gastritis와의 비교 결과는 Table II에 제시되어 있다.
Autoimmune atrophic gastritis 환자들은 두 가지 진단 기준 모두에서 chronic non-autoimmune gastritis 환자보다 양성 SIBO 흡인액 배양 결과의 오즈가 유의하게 높았다.
SIBO 양성률은 75.0% vs 34.3%였으며
(P<0.00001; OR 5.73, 95% CI 3.04–10.84)
양성률은 92.3% vs 65.0%였다
(P=0.000043; OR 6.46, 95% CI 2.32–18.02)
반면 호기 검사 양성률은 autoimmune atrophic gastritis 환자에서 수치상 더 높았지만 통계적으로 유의하지는 않았다
(45.8% vs 30.3%; P=0.106; OR 1.97, 95% CI 0.91–4.25)
분석을 연령 및 성별 매칭 대조군으로 제한했을 때도 결과는 변하지 않았으며, autoimmune atrophic gastritis에서 SIBO의 오즈가 여전히 유의하게 높았다.
75.0% vs 35.4%
(P<0.00001; OR 5.43, 95% CI 2.58–11.47)
92.3% vs 67.7%
(P=0.000876; OR 5.58, 95% CI 1.86–16.8)
호기 검사 양성률은 autoimmune atrophic gastritis 군에서 수치상 더 높았으나 통계적으로 유의하지는 않았다
(45.8% vs 33.3%; P=0.3017; OR 1.69; 95% CI 0.62–4.61)
로지스틱 회귀 분석에서는 PPI 사용 여부와 복부 수술 병력은 두 가지 진단 기준에서의 양성 흡인액 배양 결과나 양성 호기 검사와 유의한 연관성을 보이지 않았다 (Supplementary Table I).
Discussion
본 연구는 현재까지 autoimmune atrophic gastritis에서 MO를 기술한 가장 큰 연구이다. 위장관 증상 평가를 위해 소장 흡인액 배양 검사를 시행한 autoimmune atrophic gastritis 환자에서, SIBO는 ≥10⁵ CFU/mL 기준에서 75%, ≥10³ CFU/mL 기준에서 92.3%로 확인되었다. 호기 검사로 진단했을 경우에는 45.8%가 양성이었다. Autoimmune atrophic gastritis는 autoimmune atrophic gastritis나 Helicobacter pylori 감염에 의하지 않은 만성 위염 환자를 연령 및 성별 매칭하여 비교했을 때, 양성 흡인액 배양 결과의 오즈가 유의하게 높았으며 약 5배 이상의 증가를 보였다. 또한 재발성 SIBO도 흔하게 관찰되었다.
소장 흡인액 배양에서 SIBO의 최적 진단 기준에 대해서는 여전히 연구가 진행 중이지만, ≥10³ CFU/mL 기준이 특정 위장관 증상, 특징적인 dysbiosis, 그리고 대사체(metabolomic) 프로파일과 연관된다는 근거가 증가하고 있다[1]. 어떤 기준을 사용하더라도, 소장 흡인액을 얻은 autoimmune atrophic gastritis 환자에서 SIBO의 유병률은 매우 높은 것이 분명하다. 배양 결과는 이전 SIBO 시퀀싱 연구 결과와 일치하며, Enterobacteriaceae 우세와 Klebsiella 및 Escherichia와 같은 disruptor taxa의 존재를 보여준다[1]. 또한 반복 흡인액 배양을 시행한 환자 중 83.3%에서 SIBO가 재발하였다.
SIFO는 본 코호트에서 드물었으며(7.7%), 항상 SIBO와 함께 발생하였다. SIBO의 유병률이 매우 높은데도 SIFO가 드문 것은 위산이 장내 진균량 조절에 주요한 역할을 하지 않을 가능성을 시사한다. 이 가설은 쥐 실험에서 famotidine 전처치 후 Candida albicans를 위에 접종해도 위 정착에 영향을 주지 않았다는 연구에 의해 뒷받침된다[12]. 그러나 인간 연구에서는 histamine-2 receptor antagonist와 PPI를 사용하는 환자에서 위 내 Candida albicans 양이 증가한 것으로 보고되었다[13]. 또한 PPI 사용은 SIFO와도 관련이 있다[14].
이전 연구에서 autoimmune atrophic gastritis에서 MO를 직접적으로 연구한 것은 없지만, achlorhydria 상태에서 장내 미생물에 대한 연구는 존재한다. 1969년 Drasar, Shiner, McLeod의 연구에서는 achlorhydria 환자와 건강 대조군의 장내 미생물을 비교하였다. 건강 대조군에서는 일반적으로 105 CFU/mL 이하였으며, Lactobacillus, Streptococcus, Enterococcus가 주로 존재하는 다양한 균 구성을 보였다. 반면 achlorhydria 환자에서는 소장 내 세균 수가 유의하게 증가하여 일반적으로 106–107 CFU/mL였다. 이 군에서 흔한 균은 Bacteroides, Clostridia, Escherichia coli였다[15]. 이 연구는 achlorhydria가 dysbiosis와 MO 모두와 연관됨을 보여주었다.
이후 Saltzmann 등의 1994년 연구에서는 위축성 위염 또는 PPI 복용 중인 노인 17명을 대상으로 MO를 조사하였으며, lactulose 또는 glucose 호기 검사에서 단 1명만 이상 결과를 보였다[16]. 그러나 이후 여러 연구에서 PPI 사용과 SIBO 사이의 연관성이 보고되었으며, 여러 메타분석도 이를 지지한다. Lo와 Chan(2013)은 흡인액 배양 기준에서는 PPI 사용이 MO 위험 증가와 관련 있지만 호기 검사 기준에서는 그렇지 않다는 메타분석 결과를 보고하였다[6]. Su 등(2018)도 호기 검사 또는 흡인액 배양 기준 모두에서 MO 위험이 중등도 증가한다고 보고하였다[7]. 최근 건강한 자원자를 대상으로 한 중재 연구에서는 pantoprazole을 7일간 복용 후 7.8%에서 glucose 호기 검사 양성이 나타났으며, MO가 발생한 사람에서는 복부 팽만과 가스 증가가 관찰되었다[8]. 기존 PPI 사용자 연구에 비해 본 연구에서 MO 유병률이 더 높은 것은 기전적으로 설명 가능하다. 왜냐하면 autoimmune atrophic gastritis에서는 벽세포의 광범위하고 비가역적인 파괴로 인해 PPI에 의한 가역적 H+/K+ ATPase 억제보다 훨씬 심한 achlorhydria가 발생하기 때문이다.
호기 검사를 시행한 환자에서는 45.8%만 양성으로 나타났으며, 이는 보수적인 흡인액 기준보다도 훨씬 낮은 유병률이다. 또한 두 검사를 모두 시행한 환자에서 71%는 흡인액 배양은 양성이지만 호기 검사는 음성으로 나타나 두 검사 간 불일치가 존재하였다. 이러한 결과는 위축성 위염 환자에서 호기 검사의 민감도가 낮을 수 있음을 시사한다. (다른 설명으로는 호기 검사가 제균 확인을 위해 시행되었을 가능성이 있으나, 반복 흡인액 배양에서 대부분 지속적으로 양성이었기 때문에 이는 가능성이 낮다.) 이 결과는 achlorhydria 환자에서 호기 검사 양성이 거의 없었던 Saltzmann 등의 연구와도 일치한다[16]. 이러한 낮은 민감도는 수소나 메탄을 생성하지 않는 세균의 존재 때문일 수도 있고(그러나 배양 결과에서는 가스 생성 균과 유사한 균이 확인되었다), 약물 등의 교란 요인 때문일 수도 있다.
또한 흡인액 배양은 gold standard 진단법이지만 위양성(false positive)의 가능성도 있다. 특히 부적절한 기술을 사용할 경우 구인두 균 오염이 발생할 수 있으며, 특히 비멸균 single lumen catheter를 사용할 때 그렇다. 우리 기관에서는 이러한 카테터를 사용하고 있으며, 우리 기관 연구에서는 이 방법으로 얻은 샘플의 최대 20%가 오염되어 위양성으로 나타난다고 보고하였다[17]. 이러한 오염은 매우 높은 양성률과 배양과 호기 검사 간 불일치를 일부 설명할 수 있다. 그러나 배양에서 확인된 특정 균들이 double lumen sterile catheter를 사용한 연구에서 MO 원인균으로 확인된 균과 일치한다는 점은 이러한 설명을 부분적으로 반박한다[1,18,19]. 또한 흡인액 배양은 너무 근위부에서 채취할 경우 소장의 더 원위부에서 발생한 MO를 놓쳐 위음성(false negative)이 될 수도 있다[20].
이러한 한계에도 불구하고, 흡인액 배양은 여전히 gold standard 진단법으로 간주된다. 이는 호기 검사가 여러 변수로 인해 위양성과 위음성 모두 발생할 수 있기 때문이다[21,22]. 실제로 glucose 호기 검사 연구에서 scintigraphic tracer를 이용해 기질의 위치를 확인했을 때 양성 호기 검사 중 48%가 실제로는 대장에서 발효된 위양성이었다[23]. Lactulose를 사용한 연구에서는 수소 증가 시점에 88%에서 이미 맹장에 기질이 도달해 있었다[24]. 호기 검사는 장비 문제, 환자의 호기 샘플 문제, 운동, 약물(항생제, 장운동촉진제, 완하제), 장운동 장애 등에 의해 위음성이 될 수 있다. 특히 마지막 요인은 본 연구에서 중요한데, autoimmune atrophic gastritis와 achlorhydria는 위 배출 지연과 연관되어 있기 때문이다[25,26]. Lactulose는 특히 민감도와 특이도가 낮아 신속한 장 통과가 있는 경우 신뢰도가 낮다. 우리 기관에서는 대부분 glucose를 사용하며, 본 연구에서도 83%가 glucose 호기 검사였다. 이는 검사 결과의 신뢰도를 높이지만, glucose 호기 검사 역시 한계가 존재한다.
최근에는 황산염 환원 세균(Desulfovibrio 등)의 과증식으로 인한 intestinal sulfide overproduction라는 MO의 또 다른 표현형이 제시되었으며, 이는 설사와 관련된다[27]. Hydrogen sulfide는 일반적인 hydrogen/methane 호기 검사에서 측정되지 않는다. 만약 hydrogen sulfide와 autoimmune atrophic gastritis 사이에 연관성이 있다면(수소 황화물은 위 점막 항상성에 영향을 미치는 것으로 알려져 있음)[28], 현재의 호기 검사는 이러한 MO 사례를 놓칠 수 있다. 결국 MO의 두 진단 방법 모두 위양성과 위음성이 발생할 수 있는 한계가 있으며, autoimmune atrophic gastritis 환자에서 MO 검사 결과를 해석할 때 이러한 점을 고려해야 한다.
흥미롭게도 autoimmune atrophic gastritis 환자의 양성 호기 검사 중 90.9%는 메탄 증가(단독 72.7%, 수소 동반 18.2%)로 설명되었다. Intestinal methanogen overgrowth는 변비와 관련되며[2], 소장 및 대장 운동 저하의 결과일 수 있다[29]. Autoimmune gastritis에서는 위 배출 지연이 보고되어 있으며[25,26], 이는 자율신경계 기능 이상 때문일 수 있다. 그러나 소장과 대장 운동 이상은 아직 연구되지 않았다. 자율신경 이상이 장 통과를 지연시켜 IMO 위험을 증가시킬 가능성이 있다.
흡인액 배양 비교 분석에서 autoimmune atrophic gastritis는 non-autoimmune chronic gastritis보다 SIBO와 훨씬 더 강하게 연관되었으며, 두 진단 기준 모두에서 약 5배 이상의 위험 증가를 보였다. 그러나 이러한 OR 해석에서는 autoimmune atrophic gastritis 환자 수가 적어 신뢰구간이 넓다는 점을 고려해야 한다. 반면 호기 검사에서는 autoimmune atrophic gastritis에서 수치상 더 높았지만 통계적으로 유의하지 않았다. 두 군 모두에서 호기 검사 양성률은 배양 양성률보다 훨씬 낮았다.
흡인액 배양과 호기 검사 간 낮은 일치도는 이전 연구에서도 보고된 바 있다. 40명을 대상으로 한 연구에서는 공장 흡인액 배양 양성 35%, lactulose 호기 검사 45%, glucose 호기 검사 30%였으며, 특히 lactulose 검사와 배양 결과의 일치도가 낮았다[30]. 139명을 대상으로 한 연구에서도 배양 양성 44.6%, glucose 호기 검사 양성 27.3%, 진단 일치도 65.5%였다[31]. 이러한 낮은 일치도는 흡인액 배양의 구인두 오염에 의한 위양성과 호기 검사 위음성 때문일 가능성이 있다[17,22].
전반적으로 흡인액 배양은 EGD와 진정이 필요하고 비용이 높아 일부 환자에서는 시행이 어렵지만, autoimmune atrophic gastritis 환자에서는 정기적으로 intestinal metaplasia 및 위암 선별을 위해 EGD를 시행하는 경우가 많기 때문에, 이러한 환자에서는 흡인액 배양을 시행하는 것이 합리적이다. 구인두 오염으로 인한 위양성을 줄이기 위해 sterile double lumen catheter 사용을 고려해야 한다[32].
Limitations of the study
본 연구에는 몇 가지 한계가 있다. 첫째, 본 연구는 후향적 연구(retrospective study)이다. 증례의 식별은 ICD-9 및 ICD-10 코드를 이용하여 이루어졌는데, autoimmune gastritis 자체에는 고유한 진단 코드가 존재하지 않는다. 따라서 다른 코드로 분류된 경우 일부 증례가 누락되었을 가능성이 있다. 본 연구는 autoimmune atrophic gastritis 환자에서 MO의 유병률(prevalence)을 평가하기 위해 설계된 연구가 아니다(이는 대조군을 포함한 연구에서만 가능하다). 대신 우리는 MO 검사를 시행한 autoimmune atrophic gastritis 환자에서 MO의 빈도(frequency)를 평가하였다.
또한 본 연구에서는 MO 검사를 시행하게 된 적응증이나 환자의 임상 결과(clinical outcomes)를 평가하지 않았다. 이는 해당 정보가 전자의무기록(electronic health record)에 일관된 형식으로 기록되어 있지 않아 데이터 추출이 어려웠기 때문이다. MO 검사를 시행한 이유를 직접 분석하지는 않았지만, 아마도 지속적인 위장관 증상 때문이었을 것으로 추정된다. 우리 기관의 경험에 따르면 대부분의 흡인액 배양 검사는 설사 평가를 위해 시행된다. 따라서 본 연구 대상은 모든 autoimmune atrophic gastritis 환자를 대표한다고 보기 어렵고, 이 질환에서 MO의 실제 유병률을 과대평가했을 가능성이 있다.
마지막으로, 앞서 상세히 논의한 바와 같이 모든 MO 진단 방법은 위양성(false positive)과 위음성(false negative)의 가능성이 있다. 우리 기관의 흡인액 배양 채취 방법은 최대 20%에서 위양성을 초래할 수 있어 SIBO를 과대평가했을 가능성이 있다[17]. 마찬가지로 호기 검사 역시 여러 제한점이 있으며, 이는 다른 문헌에서 광범위하게 논의된 바 있다[21,22].
향후 연구에서는 autoimmune atrophic gastritis 환자에서 MO 존재 여부를 전향적으로(prospectively) 평가하고, gold-standard 진단 방법을 사용하며, 또한 특정 증상이 MO를 예측하는지 여부도 함께 평가해야 할 것이다.
Conclusions
Autoimmune atrophic gastritis 환자에서 소장 흡인액 배양을 동반한 EGD를 시행한 경우 SIBO는 흔하게 관찰되었으며, ≥10³ CFU/mL 기준에서는 92.3%, ≥10⁵ CFU/mL 기준에서는 75%의 빈도를 보였다. 반복 흡인액 배양을 시행한 환자 중에서는 83.3%에서 SIBO가 재발하였다. SIFO는 7.7%로 매우 드물었으며 항상 SIBO와 함께 발생하였다. 호기 검사 양성은 45.8%에서 관찰되었으며, 대부분의 경우는 intestinal methanogen overgrowth에 의한 것이었다.
Autoimmune atrophic gastritis 환자는 non-autoimmune chronic gastritis 환자에 비해 두 가지 진단 기준 모두에서 SIBO 흡인액 배양 양성일 가능성이 5배 이상 높았다. 본 연구 결과는 MO 진단 방법의 검사 특성이 완전하지 않다는 한계가 있다. 임상가는 지속적인 증상이 있는 autoimmune atrophic gastritis 환자에서 MO의 가능성을 항상 고려해야 한다.
<Abstract>
Background: Autoimmune atrophic gastritis causes achlorhydria, which may predispose to gastrointestinal microbial overgrowth (MO). We sought to evaluate the association between autoimmune atrophic gastritis and MO.
Methods: From a database of patients at our institution who had undergone MO testing (via intestinal aspirate culture or glucose or lactulose hydrogen/methane breath testing), we identified patients with autoimmune atrophic gastritis via ICD codes. We then confirmed that these patients had a histologically confirmed diagnosis. Finally we queried the electronic health record to identify patients with non-atrophic chronic gastritis who had undergone MO testing.
Results: We identified 52 patients with autoimmune atrophic gastritis who underwent aspirate culture; 48 (92.3%) met criteria for small intestinal bacterial overgrowth (SIBO) at a threshold of ≥103 CFU/mL, and 39 (75%) at ≥105 CFU/mL. Among patients who had multiple aspirates, 83.3% had recurrent SIBO. Among 24 patients who underwent breath testing, 11 (45.8%) tested positive, primarily reflecting intestinal methanogen overgrowth. A notable discordance was observed among seven patients who underwent both testing modalities, with five patients having a positive culture but negative breath test. Finally, comparing MO results from patients with autoimmune atrophic gastritis to those with non-atrophic chronic gastritis identified significantly higher test positivity in autoimmune atrophic gastritis (75% vs. 34.3% at ≥105 CFU/mL, P<0.00001; 92.3% vs. 65%, P=0.000043), but not for breath tests (45.8% vs. 30.3%, P=0.106).
Conclusions: MO is common among symptomatic patients with autoimmune atrophic gastritis, and intestinal aspirate culture identifies more positive cases than breath testing in this population. Findings are subject to selection bias and the inherent constraints of both MO testing modalities, and require confirmation with prospective studies.
References
1. leite G, rezaie a, Mathur r, Barlow GM, rashid M, Hosseini a, et al.; REIMAGINE Study Group. Defining Small In testinal Bacterial overgrowth by Culture and High through put Sequencing. Clin Gastroenterol Hepatol 2024;22:259–70.
2. Mehravar s, takakura W, Wang J, Pimentel M, Nasser J, Rezaie A. Symptom Profile of Patients With Intestinal Metha nogen overgrowth: a systematic review and Meta-analysis. Clin Gastroenterol Hepatol 2025;23:1111–1122.e9.
3. lim J, rezaie a. irritable Bowel syndrome-like symp toms in Quiescent Inflammatory Bowel Disease: A Practical approach to Diagnosis and treatment of organic Causes. Dig Dis Sci 2023;68:4081–97.
4. Pimentel M, saad rJ, long MD, rao ss. aCG Clinical Guideline: small intestinal Bacterial overgrowth. am J Gas troenterol 2020;115:165–78.
5. lombardo l, Foti M, ruggia o, Chiecchio a. increased incidence of small intestinal bacterial overgrowth during proton pump inhibitor therapy. Clin Gastroenterol Hepatol 2010;8:504–8.
6. lo WK, Chan WW. Proton pump inhibitor use and the risk of small intestinal bacterial overgrowth: a meta-analysis. Clin Gastroenterol Hepatol 2013;11:483–90.
7. su t, lai s, lee a, He X, Chen s. Meta-analysis: proton pump inhibitors moderately increase the risk of small intesti nal bacterial overgrowth. J Gastroenterol 2018;53:27–36.
8. Durán-rosas C, Priego-Parra Ba, Morel-Cerda e, Mer cado-Jauregui la, aquino-ruiz Ca, triana-romero a, et al. incidence of small intestinal Bacterial overgrowth and symptoms after 7 Days of Proton Pump inhibitor Use: a Study on Healthy Volunteers. Dig Dis Sci 2024;69:209–15.
9. Bohm M, shin a, teagarden s, Xu H, Gupta a, siwiec r, et al. Risk Factors Aassociated With Upper Aerodigestive Tract or Coliform Bacterial Overgrowth of the Small Intestine in Symptomatic Patients. J Clin Gastroenterol 2020;54:150–7.
10. Tucci A, Poli l, Biasco G, Paparo GF, Tosetti C, Fusaroli P, et al. Helicobacter pylori infection and gastric function in patients with fundic atrophic gastritis. Dig Dis sci 2001;46:1573–83.
11. Lenti MV, Rugge M, Lahner E, Miceli E, Toh BH, Genta RM, et al. Autoimmune gastritis. Nat Rev Dis Primers 2020;6:56.
12. Greenfield RA, Joyce WA. Gastric colonization with Candida albicans. Mycopathologia 1993;122:1–5.
13. Mottaghi B, emami MH, riahi P, Fahim a, rahimi H, Mohammadi r. Candida colonization of the esophagus and gastric mucosa; a comparison of patients taking proton pump inhibitors and those taking histamine receptor antagonist drugs. Gastroenterol Hepatol Bed Bench 2021;14:349–55.
14. Jacobs C, Coss adame e, attaluri a, Valestin J, rao ss. Dysmotility and proton pump inhibitor use are independent risk factors for small intestinal bacterial and/or fungal over growth. Aliment Pharmacol Ther 2013;37:1103–11.
15. Drasar Bs, shiner M, Mcleod GM. studies on the in testinal flora. I. The bacterial flora of the gastrointestinal tract in healthy and achlorhydric persons. Gastroenterology 1969;56:71–9.
16. saltzman Jr, Kowdley KV, Pedrosa MC, sepe t, Gol ner B, Perrone G, et al. Bacterial overgrowth without clinical malabsorption in elderly hypochlorhydric subjects. Gastroen terology 1994;106:615–23.
17. Cangemi DJ, lacy Be, Wise J. Diagnosing small in testinal Bacterial overgrowth: a Comparison of lactu lose Breath tests to small Bowel aspirates. Dig Dis sci 2021;66:2042–50.
18. Barlow Jt, leite G, romano ae, sedighi r, Chang C, Celly s, et al. Quantitative sequencing clarifies the role of dis ruptor taxa, oral microbiota, and strict anaerobes in the human small-intestine microbiome. Microbiome 2021;9:214.
19. Villanueva-Millan MJ, leite G, Wang J, Morales W, Par odi G, Pimentel Ml, et al. Methanogens and Hydrogen sul f ide Producing Bacteria Guide Distinct Gut Microbe Profiles and irritable Bowel syndrome subtypes. am J Gastroenterol 2022;117:2055–66.
20. shah eD. Breath test or Duodenal aspirate for small in testinal Bacterial overgrowth: still No Breath of Fresh air. Dig Dis Sci 2021;66:1770–1.
21. Kashyap P, Moayyedi P, Quigley eM, simren M, Van ner s. Critical appraisal of the siBo hypothesis and breath testing: a clinical practice update endorsed by the european society of neurogastroenterology and motility (esNM) and the american neurogastroenterology and motility society (ANMS). Neurogastroenterol Motil 2024;36:e14817.
22. Damianos Ja, Matar a, Halawi H. Gas-tly interpreta tions: a Case-Based approach to the Nuances of siBo Breath Testing. Curr Gastroenterol Rep 2025;27:30.
23. lin eC, Massey Bt. scintigraphy Demonstrates High rate of False-positive results From Glucose Breath tests for small Bowel Bacterial overgrowth. Clin Gastroenterol Hepa tol 2016;14:203–8.
24. yu D, Cheeseman F, Vanner s. Combined oro-caecal scintigraphy and lactulose hydrogen breath testing demon strate that breath testing detects oro-caecal transit, not small intestinal bacterial overgrowth in patients with iBs. Gut 2011;60:334–40.
25. tosetti C, stanghellini V, tucci a, Poli l, salvioli B, Bi asco G, et al. Gastric emptying and dyspeptic symptoms in patients with nonautoimmune fundic atrophic gastritis. Dig Dis Sci 2000;45:252–7.
26. Kalkan Ç, soykan i, soydal Ç, Özkan e, Kalkan e. Assessment of Gastric emptying in Patients with autoimmune Gastritis. Dig Dis Sci 2016;61:1597–602.
27. Villanueva-Millan MJ, leite G, Mathur r, rezaie a, Fajardo CM, de Freitas Germano J, et al. Hydrogen Sulfide and Methane on Breath test Correlate with Human small in testinal Hydrogen Sulfide Producers and Methanogens. Dig Dis Sci 2025;70:3846–56.
28. Fiorucci s, Distrutti e, Cirino G, Wallace Jl. the emerg ing roles of hydrogen sulfide in the gastrointestinal tract and liver. Gastroenterology 2006;131:259–71.
29. Talamantes S, Steiner F, Spencer S, Neshatian l, Sonu I. Intestinal Methanogen Overgrowth (IMO) is associated with Delayed small Bowel and Colonic transit time (TT) on the Wireless Motility Capsule (WMC). Dig Dis sci 2024;69:3361–8.
30. Tang S, Li J, Ma J, Li Y, Li Y, Wan J, et al. Comparison of jejunal aspirate culture and methane and hydrogen breath test in the diagnosis of small intestinal bacterial overgrowth. ir J Med Sci 2024;193:699–703.
31. Erdogan A, Rao SS, Gulley D, Jacobs C, Lee YY, Badger C. small intestinal bacterial overgrowth: duodenal as piration vs glucose breath test. Neurogastroenterol Motil 2015;27:481–9.
32. Karunaratne TB, Sharma A, Rao SS. small-bowel aspi ration during upper esophagogastroduodenoscopy: rao tech nique. VideoGIE 2020;6:152–4.