Lahner E, Lenti MV, Massironi S, Zingone F, Miceli E, Della Bella C, Facciotti F, Pelizzaro F, Annibale B, D'Elios MM, Sabatino AD.
Dig Liver Dis. 2026 Jan;58(1):38-50. doi: 10.1016/j.dld.2025.10.015.
1. Introduction
자가면역성 위축성 위염(AAG)은 자가면역 기전으로 발생하는 non-self-limiting 질환으로, 최근 들어 의학 및 과학계에서 점점 더 주목받고 있다. 주요 자가항원은 프로톤 펌프(H⁺, K⁺-ATPase)의 β 아단위로 밝혀졌으며, 이는 위저선(oxyntic mucosa)의 벽세포(parietal cell)에 국한되어 존재하기 때문에, 자가면역성 염증손상 또한 이 부위에 한정되어 유문부(antrum)는 보존된다.
AAG의 임상 증상은 대개 비교적 후기 단계에 나타나며, 이는 위저부-체부 점막의 위축이 진행되어 위산 분비의 상실(hypo- 또는 achlorhydria)이 일어나고, pseudopyloric metaplasia나 intestinal metaplasia가 동반될 때 나타난다. 임상적으로는 위산 분비 저하, 철분 및/또는 코발라민(cobalamin) 흡수장애, 소화불량, 그리고 제1형 위신경내분비종양(type 1 gastric neuroendocrine neoplasm, t1-gNEN) 및 위암(gastric cancer, GC) 발생 위험의 증가가 특징적이다. 다만, 후자의 연관성은 여전히 논란의 여지가 있다.
다른 자가면역질환들과 마찬가지로, AAG는 종종 자가면역성 갑상선질환(autoimmune thyroid disease)과 함께 발생하며, 제1형 당뇨병(type 1 diabetes), 애디슨병(Addison’s disease) 등과도 동반될 수 있다 [1,2].
최근 몇 년간 AAG에 대한 연구가 활발히 이루어졌음에도 불구하고, 역학, 임상 양상, 병태생리, 진단, 치료 및 관리에 관한 여러 주제는 여전히 명확히 규명되지 않았다. 많은 환자들이 오진(misdiagnosis)되거나 진단이 지연(delay in diagnosis)되는 경우가 많으며 [3], 이는 미량영양소 결핍 및 이로 인한 빈혈, 나아가 신생물(neoplasm) 합병증 등 잠재적으로 해로운 결과를 초래할 수 있다. 따라서 AAG 환자의 조기이자 정확한 진단은 임상적으로 매우 중요하며, 이는 환자의 삶의 질 향상뿐만 아니라 사회적·경제적 부담을 줄이는 데에도 기여할 수 있다.
본 입장문(position paper)은 성인에서의 자가면역성 위축성 위염(AAG)에 대한 최신 지견을 다루며, Autoimmune gastRitis Italian netwOrk Study grOup (ARIOSO)의 견해를 반영하고 있다.
2. Material and methods
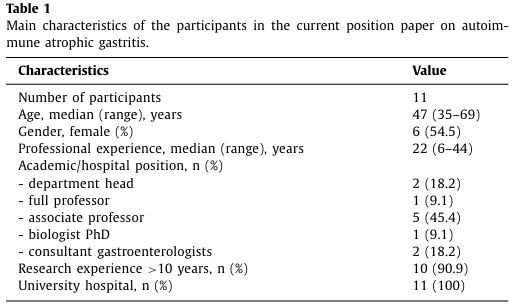
본 입장문(position paper)의 참여자들은 자가면역성 위축성 위염(AAG)과 관련된 주요 주제들 가운데, 현재의 임상진료 및 논란이 있는 쟁점들에 초점을 맞추어 일련의 진술문(statements)을 작성하고 제안하였다. 표 1에는 이번 AAG 입장문에 참여한 연구자들의 주요 특성이 요약되어 있다.
각 주제별로 2~3명의 전문가가 포함된 작업 그룹(working party) 이 구성되었으며, AAG와 관련된 문헌을 대상으로 PubMed, EMBASE, Scopus, Cochrane Library, Google Scholar 등 주요 전자 데이터베이스를 이용하여 2025년 3월까지 발표된 연구를 포괄적으로 검색하였다. 검색 주제에는 유병률(prevalence)과 발생률(incidence), 임상양상 및 증상(clinical presentation and symptoms), 진단(diagnosis), 치료(treatment), 추적관찰(follow-up) 이 포함되었다. 검색 전략은 MeSH 용어인 “atrophic gastritis”, “autoimmune gastritis”, “Helicobacter pylori”, “gastric cancer”, “gastric dysplasia”, “gastric intestinal metaplasia”, “gastric neuroendocrine tumours”, “pernicious anaemia”를 사용하였으며, 이들을 다양한 조합으로 불린 연산자(Boolean operators) 인 AND, OR, NOT을 활용하여 검색하였다. 문헌 검색은 영어로 작성된 논문으로 제한하였으며, 편집자에게 보내는 서신(letters to the editor), 증례보고(case reports), 학회 초록(meeting abstracts) 등은 제외하였다.
진술문 개발과 확정을 위해 수정 델파이(modified Delphi) 방법이 사용되었다. 각 진술문은 두 차례의 이메일 라운드를 통해 참여자들 간에 공유되었으며, 이 과정에서 과학적·임상적 타당성, 명확성과 가독성 향상, 중복 제거 등을 논의하였다. 모든 참여자들의 전원 합의(full agreement) 가 이루어질 때까지 진술문은 반복적으로 수정되었고, 이후 최종 초안이 승인되었다 [4].
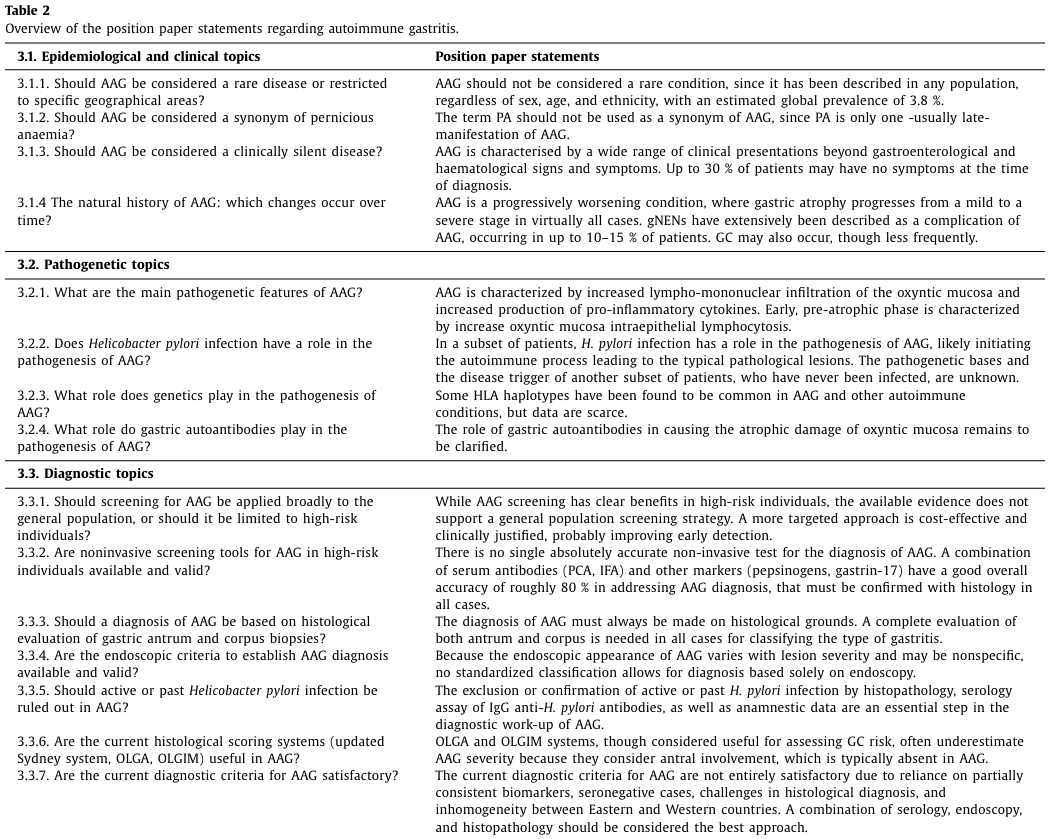
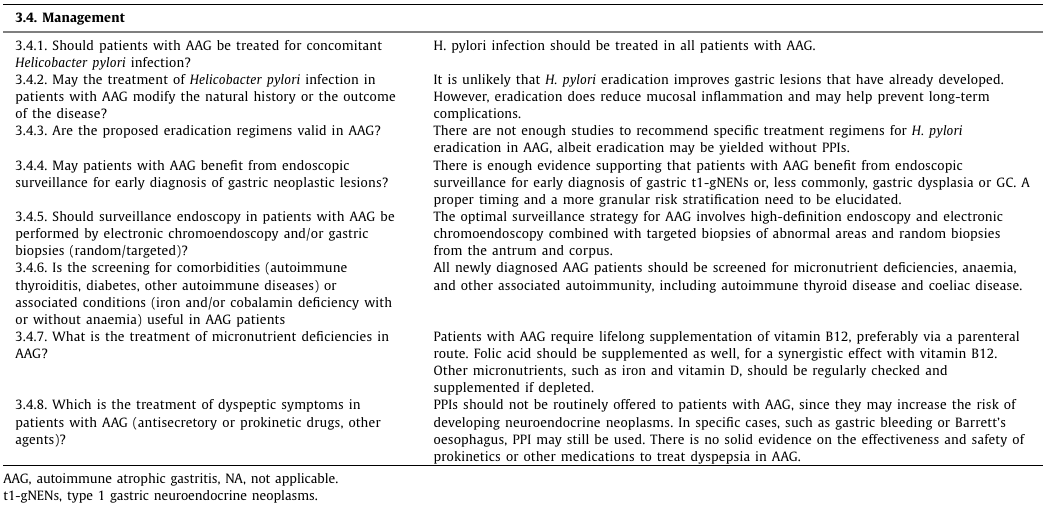
표 2는 포함된 진술문의 개요를 보여준다. 본 입장문의 구성은 각 진술문(statement), 근거 수준(evidence level, EL), 권고 등급(recommendation grade, RG), 그리고 근거 요약(summary of evidence) 으로 이루어져 있다. 이 문서는 ACCORD (ACcurate COnsensus Reporting Document) 가이드라인 [4]에 따라 작성되었다. 다만, 각 진술문에 대한 공식적인 등급화(formal grading) 는 생략되었다. 그 이유는, 첫째 본 문서가 입장문(position paper) 이며, 둘째 대부분의 질문들이 PICO(Problem, Intervention, Comparison, Outcome) 틀을 따르지 않고 AAG의 임상적 쟁점과 전반적 질문을 다루기 때문이다.
3. Statements
3.1. Epidemiological and clinical topics
3.1.1. 자가면역성 위축성 위염(AAG)은 희귀질환이거나 특정 지역에만 제한된 질환으로 보아야 하는가?
Position statement
: AAG는 희귀질환으로 간주되어서는 안 된다. 이 질환은 성별, 연령, 인종에 관계없이 전 인구집단에서 보고되었으며, 전 세계 추정 유병률은 약 3.8%로 보고된다.
AAG는 Addison에 의해 처음 기술된 이후, Helicobacter pylori (H. pylori) 의 발견으로 역학적 특성이 더욱 명확히 규명되었다. 이 발견을 통해 H. pylori 관련 위축성 위염과 자가면역성 위축성 위염(AAG) 이 구분될 수 있게 되었다 [1, 5–7]. 그 이전까지 대부분의 연구는 악성빈혈(pernicious anaemia, PA) 에만 초점을 맞추었으며, 이는 60세 이상 인구의 약 2%에서 유병률이 보고되었다 [8]. 조직학적으로 확진된 AAG의 전 세계 유병률은 연구에 따라 0.3–2.7% [9], 또는 0.5–4.5% [1,10] 로 추정되어 왔다. 또한, 최근 AAG의 역학에 관한 체계적 문헌고찰(systematic review) 에서는 전 세계 유병률이 약 3.8%로 보고되었으나, 포함된 연구들 간의 이질성이 매우 커서 일부는 혈청검사(serology) 만을 근거로 진단하여 실제보다 과대평가(overestimation) 되었을 가능성도 있다 [11]. 이 유병률 수치는 성별(여성에서 더 흔하며, 여성:남성 비는 약 2:1) [12,13], 연령(연령 증가에 따라 발생률 증가), 그리고 지리적 요인에 따라 달라질 수 있다 [1]. AAG의 역학을 보고한 대부분의 연구는 유럽(특히 이탈리아, 북유럽, 터키) 에서 수행되었으며 [1,10–17], 이로 인해 한동안 백인(Caucasian) 또는 터키계 인구에 주로 발생하는 질환으로 여겨졌다. 그러나 최근 수십 년간 일본 [18], 중국 [19,20], 아프리카 [21,22], 남아메리카 [23] 등 세계 여러 지역에서도 AAG 사례들이 보고되고 있다. 따라서 일부 연구가 부족한 지역(under-represented areas) 에서는 AAG의 실제 유병률이 과소평가(underestimated) 되었을 가능성이 높다. 한 이탈리아 연구에서는 비선택적 외래 환자군을 대상으로 혈청학적 선별검사(serological screening) 를 광범위하게 적용했을 때, AAG의 혈청학적 유병률은 10.6%, 조직학적으로 확진된 유병률은 4.3%로 보고되었다 [24].
3.1.2. 자가면역성 위축성 위염(AAG)은 악성빈혈(pernicious anaemia, PA)과 동일한 용어로 간주해야 하는가?
Position statement
: PA는 AAG의 동의어로 사용되어서는 안 된다.
PA는 AAG의 하나의 임상적 표현형(manifestation) 으로, 대개 질병의 후기 단계에서 나타나는 소견이다. PA는 오랫동안 자가면역성 위축성 위염(AAG) 환자를 지칭하는 용어로 혼용되어 왔다. 이는 비타민 B12(코발라민) 흡수 장애와 결핍으로 인해 발생하는 거대적아구성(megaloblastic), 대적혈구성 빈혈(macrocytic anaemia) 의 형태로 나타나며, 일부에서는 범혈구감소증(pancytopenia) 으로까지 진행하기도 한다 [25]. 이러한 형태의 빈혈은 오랫동안 AAG의 가장 대표적인 임상 양상으로 기술되어 왔으며 [1,8], 대개 진단 지연 없이 비교적 빠르게 AAG로 진단되는 경우가 많았다 [3]. 그러나 최근 들어 질환에 대한 이해와 진단기준이 발전함에 따라, 이 외에도 다양한 임상양상이 보고되고 있다(후술 참조). 따라서 전문가 합의에 따르면, 임상 스펙트럼이 훨씬 더 넓은 AAG를 단순히 PA와 동일시하는 것은 부적절하며, PA를 AAG의 동의어로 사용하는 것은 권장되지 않는다. 또한, 거대적아구성·대적혈구성 빈혈은 AAG 이외의 원인으로 인한 비타민 B12 결핍에서도 발생할 수 있다. 예를 들어, 식이 제한(dietary restriction), 위장관 수술 이력(previous gastrointestinal surgery), 헬리코박터 파일로리 감염(H. pylori infection) 등에서도 유사한 빈혈이 나타날 수 있다 [26].
3.1.3. 자가면역성 위축성 위염(AAG)은 임상적으로 ‘무증상 질환(clinically silent disease)’으로 간주되어야 하는가?
Position statement
: AAG는 위장관 증상이나 혈액학적 이상을 넘어서는 다양한 임상 양상을 보이는 질환이다. 진단 시점에서 최대 30%의 환자는 무증상(asymptomatic) 일 수 있다.
AAG의 임상 스펙트럼은 완전히 무증상인 상태에서부터 다음과 같은 다양한 임상 증상에 이르기까지 매우 광범위하다.
위장관 증상(Gastrointestinal symptoms): 소화불량(dyspepsia), 복통(abdominal pain), 체중감소(weight loss) 등
신경학적 이상(Neurological abnormalities): 기분 변화(mood alterations), 정신과적 증상(psychic manifestations), 감각이상(paraesthesia), 치매(dementia) 등이 있으며, 일부는 비가역적(irreversible) 일 수 있음
혈액학적 이상(Haematological alterations): 빈혈(anaemia, 비타민 B12 결핍성 또는 철결핍성), 범혈구감소증
생식 관련 이상(Fertility issues)
심혈관계 이상(Cardiovascular manifestations): 고호모시스테인혈증(hyperhomocysteinaemia)에 이차적으로 발생
기타 자가면역질환과의 연관성: 자가면역 다선증후군(autoimmune polyglandular syndromes), 자가면역성 갑상선질환(autoimmune thyroid disease) 등 [1,3,10–15,17,24].
현재까지의 연구에 따르면, AAG 환자의 약 30%까지는 뚜렷한 증상 없이 진단되거나 [12,15], 의료기관을 방문할 정도로 명확하지 않은 미묘한 임상 증상(nuanced manifestations) 만을 보일 수 있다. 일부 환자에서는 왜 특정 임상양상(예: PA)은 나타나지만 다른 양상(예: 신경학적 이상)은 나타나지 않는지 명확히 알려져 있지 않다. 이에 대해 유전적 요인(genetic factors) 이 AAG의 임상 표현형(clinical manifestation)에 영향을 미칠 수 있다는 가설이 제기되어 있다(3.2.3절 참조). 비타민 B12 결핍은 임상적으로 증상이 나타나기까지 수년에 걸쳐 서서히 진행되므로 [26], AAG 환자는 오랜 기간 동안 무증상 상태로 존재할 수 있다. 따라서 AAG 가족력이 있는 1차 친족(first-degree relatives) 이나 다른 자가면역질환을 가진 개인에 대해 혈청학적 선별검사(serological screening) 를 시행하면, 증상이 나타나기 전 무증상 단계에서 AAG를 조기 진단(early diagnosis) 할 수 있다 [24,27].
3.1.4. 자가면역성 위축성 위염(AAG)의 자연경과: 시간이 지나면서 어떤 변화가 일어나는가?
Position statement
: AAG는 점진적으로 악화되는 진행성 질환(progressively worsening condition) 으로, 거의 모든 경우에서 위축(gastric atrophy)이 경도에서 중등도, 중증 단계로 진행한다. AAG의 합병증으로는 위 신경내분비종양(gastric neuroendocrine neoplasms, gNENs) 이 잘 알려져 있으며, 환자의 약 10–15%에서 발생한다. 또한 위암(gastric cancer, GC) 도 드물지만 발생할 수 있다.
최근 수년간 AAG의 자연경과(natural history) 에 대한 몇몇 연구가 발표되었으며, 이들 연구의 중앙 추적관찰기간(median follow-up time) 은 약 10년 정도이며, 일부 연구에서는 최대 20년 이상 장기간 관찰된 환자들도 포함되었다 [28–32]. 이러한 연구들은 AAG가 시간이 지남에 따라 점진적으로 악화되는 질환임을 일관되게 보여주었다. 초기 단계의 AAG, 즉 위축이 없는 상태에서 벽세포 자가항체(parietal cell autoantibodies, PCA) 가 존재하는 경우를 잠재성 자가면역성 위염(potential autoimmune gastritis) 이라 한다. 이들은 시간이 지나면서 명확한 형태의 AAG(overt AAG) 로 발전할 위험이 있다.
관찰 연구에 따르면, 약 절반의 환자(약 50%)가 5년 내에 체부 위축(corpus atrophy) 으로 진행하며, 장기간 추적할 경우 약 75%까지 위축이 발생한다 [29,32]. 대부분의 경우, AAG 환자들은 경도의 위축에서 중증 위축으로 진행하지만 [29,30], 신생물 합병증(neoplastic complications) 으로 발전하는 경우는 소수(minority) 에 해당한다. 그 중 가장 흔한 것은 제1형 위 신경내분비종양(type 1 gNENs) [28–32]이며, 그 다음이 위암(GC) [30]이다.
AAG의 자연경과를 다룬 거의 모든 연구에서, t1-gNEN 발생 위험은 일관되게 보고되었으며, AAG 환자의 평생 유병률(lifetime risk) 은 약 10–15%로 추정된다 [28–32]. 반면, AAG 환자가 위암(GC) 발생 위험이 증가하는지 여부는 여전히 논란이 있다 [31,33,34]. 대부분의 연구들은 순수 AAG(pure AAG) 에서 위암 위험이 매우 낮거나 거의 없다고 보고하였으나 [28,29,31], 과거에 헬리코박터 파일로리 감염(H. pylori infection)의 병력이 있는 환자에서는 [29,34] 이 위험이 유의하게 증가할 수 있음이 제시되었다. 다만, AAG의 자연경과를 다룬 기존 연구들은 대부분 3차 의료기관(tertiary referral centre) 에서 수행된 것으로, 이들 기관에서는 내시경 감시(endoscopic surveillance) 가 매우 적극적으로 이루어지므로, 그 결과를 일반 인구집단에 그대로 적용하기는 어렵다.
병태생리학적 관점에서, 최근 연구에 따르면 AAG 환자의 위점막에서 H. pylori 위염과 유사하게 ANPEP/CD13을 발현하는 암 관련 화생세포(cancer-related metaplastic cells) 가 관찰되었다 [35]. 이 발견은 AAG가 일부 환자에서는 실제로 위암으로 진행할 수 있음을 시사하며, 이를 명확히 규명하기 위해서는 추가적인 전향적 연구(prospective studies) 가 필요하다.
3.2. Pathogenetic topics
3.2.1. 자가면역성 위축성 위염(AAG)의 주요 병인적 특징은 무엇인가?
Position statement
: AAG는 위저선(oxyntic mucosa)의 림프단핵세포(lymphomononuclear cell) 침윤 증가와 염증성 사이토카인(pro-inflammatory cytokine)의 과생산이 특징이다. 위축이 진행되기 전의 초기, 전(前)위축기(pre-atrophic phase) 에서는 위저선 점막 내상피 림프구침윤(intraepithelial lymphocytosis) 이 증가하는 것이 특징적이다.
AAG는 위체부(corpus)와 위저부(fundus)에 국한된 염증성 자가면역 질환으로, 위벽세포(parietal cell)의 파괴와 위저선 점막의 위축(atrophy) 을 특징으로 한다. 이로 인해 내인자(intrinsic factor) 결핍과 저산증 또는 무산증(hypo-/achlorhydria) 이 발생하며, 흔히 그레이브스병(Basedow–Graves’ disease), 하시모토 갑상선염(Hashimoto’s thyroiditis) 등 다른 자가면역질환과 동반된다. AAG의 병리학적 소견은 위 점막고유층(lamina propria)과 점막하층(submucosa) 에 존재하는 림프구 및 형질세포(plasma cell)의 침윤과, 위벽세포(parietal cell) 및 주세포(zyminogenic cell) 의 지속적인 파괴 과정으로 요약된다 [1,2]. AAG의 병인에서 핵심은 위벽세포의 H⁺,K⁺-ATPase 및 내인자(intrinsic factor)에 특이적인 T세포 반응과 이들을 표적으로 하는 자가항체(autoantibodies) 의 생성이다. 즉, H⁺,K⁺-ATPase에 대한 항체(anti-parietal cell antibody, PCA) 와 내인자에 대한 항체(anti-intrinsic factor antibody, IFA) 가 주요 면역 표적이다. AAG에서의 위점막 염증 및 손상의 주요 유발자는 H⁺,K⁺-ATPase 및 내인자에 특이적인 CD4⁺ T세포이며, 이들은 다음과 같은 기전을 통해 위점막 손상을 일으킨다:
IFN-γ, TNF-α, IL-17 등의 염증성 사이토카인 분비,
Fas–Fas ligand 경로를 통한 세포사멸(apoptosis) 유도,
perforin 매개 세포독성(perforin-mediated cytotoxicity) 을 통한 벽세포 직접 파괴,
B세포 도움(helper activity) 을 통한 자가항체 생성 촉진 [1,36].
면역형광검사(immunofluorescence) 결과, IL-7R과 TSLP(thymic stromal lymphopoietin) 의 발현이 AAG 환자에서 현저히 증가되어 있음이 보고되었다 [37]. 또한, CD38⁺ 형질 B세포(plasma B cell) 가 건강한 대조군에 비해 AAG 환자의 점막고유층에서 유의하게 더 많이 관찰된다 [38].
임상적으로 AAG의 초기 염증 단계(initial inflammatory events) 를 규명한 연구는 아직 부족하다. 최근 한 연구에서는, 위축이 없는 상태에서 벽세포 자가항체(PCA) 가 존재하는 환자군을 잠재성 자가면역성 위염(potential autoimmune gastritis) 으로 정의하고, 이들의 위체부 점막(corpus mucosa) 에서 상피내 림프구(intraepithelial lymphocyte, IEL) 침윤 양상을 분석하였다. 그 결과, CD3⁺ IEL의 깊은 층(deep zone) 에서의 침윤이 특징적이었으며,
100개의 상피세포당 7개 이상의 deep CD3⁺ IEL (>7/100 epithelial cells) 이 자가면역성 위염의 존재 및 중증도를 구분하는 지표로 사용될 수 있음을 확인하였다 (AUC = 0.842). 이는 위저선 점막에서의 deep CD3⁺ IEL 증가가 잠재성 AAG의 조직학적 표지(marker) 가 될 수 있음을 시사한다 [39].
3.2.2. 헬리코박터 파일로리(Helicobacter pylori) 감염은 자가면역성 위축성 위염(AAG)의 병인에 관여하는가?
Position statement
: 일부 AAG 환자에서 H. pylori 감염은 질환의 병인(pathogenesis)에 중요한 역할을 하며, 이는 자가면역 반응(autoimmune process)을 유발하거나 촉발(trigger) 하여 AAG의 전형적인 병리학적 병변을 일으키는 것으로 보인다. 반면, H. pylori 감염력이 전혀 없는 환자군(subset)의 질환 발생 기전과 병인적 기초는 아직 명확히 밝혀지지 않았다.
H. pylori는 위벽세포의 주요 자가항원인 H⁺,K⁺-ATPase와 구조적으로 유사한(epitope similarity) 항원 결정기(epitope) 를 발현하는 것으로 알려져 있다. 이러한 구조적 유사성은 분자적 모방(molecular mimicry) 기전을 통해 H. pylori 감염이 자가면역 반응을 유도할 수 있는 근거를 제공한다. 실제로, H. pylori에 감염된 AAG 환자에서는 위점막 내에 침윤한 CD4⁺ T 헬퍼세포가 자기 위벽세포의 H⁺,K⁺-ATPase 및 다양한 위 단백질의 항원결정기(epitope) 를 교차인식(cross-recognition) 하는 것이 확인되었다. 이러한 T세포는 활성화 후 다음과 같은 병리적 반응을 일으킨다:
IFN-γ, TNF-α 등의 염증성 사이토카인 생성,
Fas ligand 매개 세포사멸(Fas–FasL-mediated apoptosis) 및 perforin 매개 세포독성(perforin-mediated cytotoxicity) 을 통한 위벽세포 파괴,
H⁺,K⁺-ATPase에 대한 자가항체(anti-H⁺,K⁺-ATPase antibody) 생성 촉진.
이와 같은 기전으로 H. pylori 감염은 위 자가면역 반응을 유발하거나 악화시켜 위축(atrophy)을 일으킬 수 있다 [40,41].
또한, H. pylori에 감염된 AAG 환자들은 혈청 내에서 H⁺,K⁺-ATPase에 대한 자가항체가 순환(circulating autoantibody) 하는데, 이 항체는 H. pylori 제균치료 이후 유의하게 감소하는 것으로 보고되었다 [42–44].
H. pylori 감염이 명확히 진단된 AAG 환자에 대한 연구는 많지 않지만, 조직학적으로 위체부에 국한된 위축(corpus-restricted atrophy) 을 보인 연속 환자군을 대상으로 한 한 관찰연구에서는
또한, 최근 다기관 연구에 따르면 AAG 환자의 27.7%에서 과거 H. pylori 감염력이 확인되었다 [14].
결론적으로, 위체부 국한 위축(corpus-restricted atrophy) 으로 진단된 일부 AAG 환자에서는 활동성 H. pylori 감염 또는 과거 H. pylori 노출의 흔적이 존재하며, 이는 H. pylori 감염이 AAG의 병인에 부분적으로 기여할 가능성과 자가면역성 위염과 H. pylori 위염이 중첩(overlap) 또는 공존(co-presence) 할 수 있음을 시사한다.
3.2.3. 자가면역성 위축성 위염(AAG)의 병인에서 유전학은 어떤 역할을 하는가?
Position statement
: AAG 환자에서 특정 HLA 하플로타입(HLA haplotype) 이 다른 자가면역질환들과 공통적으로 관찰되지만, 현재까지의 연구 자료는 매우 제한적(scarce) 이다.
AAG의 병인에는 위 자가면역 반응(gastric autoimmunity) 의 발생을 촉진하는 여러 유전적 요인(genetic factors) 이 관여하는 것으로 알려져 있다.
그 예로,
특정 MHC class II 하플로타입이 존재하여 H⁺,K⁺-ATPase, 내인자(intrinsic factor), 또는 H⁺,K⁺-ATPase–H. pylori 교차반응성 항원(epitope) 을 제시할 수 있는 경우,
자가반응성 T세포(autoreactive T cell) 의 생존을 촉진시키는 유전적 요인,
위점막 면역관용(gastric tolerance)의 붕괴,
H. pylori 감염으로 유도되는 염증반응, 특히 IFN-γ, TNF-α, IL-17 등의 사이토카인 과생산,
그리고 Fas ligand 및 perforin 매개 세포독성 반응의 만성적 지속 활성화 등이 포함된다.
이러한 요인들은 복합적으로 작용하여 위벽세포(parietal cell)에 대한 자가면역 공격(autoimmune attack) 을 촉진한다 [1,37,41].
반면, AAG 환자에서 HLA 하플로타입을 직접 분석한 연구는 매우 제한적이다.
이탈리아 연구(Italian study) 에서는 89명의 AAG 환자를 대상으로 HLA-DRB1 유전형을 평가한 결과, 절반 이상에서 HLA-DRB1*03 또는 *04 대립유전자(allele) 가 발견되었으며, 이는 일반적으로 여러 자가면역질환과 연관된 하플로타입으로 알려져 있다. 이 결과는 AAG가 자가면역성 소인을 가진 개인에서 발생할 가능성을 시사한다 [45].
핀란드 연구(Finnish study) 에서는 12명의 AAG 환자를 분석하였고, HLA-DRB1*04 및 DQB1*03 대립유전자가 AAG 발생에 유전적 소인(predisposition) 을 줄 수 있는 반면, HLA-B8–DRB1*03 은 관련이 없음을 보고하였다 [46].
또 다른 연구에서는 transcobalamin 2 (TCN2) 유전자 다형성(polymorphic variant) 이 비타민 B12 혈중 농도 감소와 연관되며, 이러한 변이가 악성빈혈(pernicious anaemia, PA) 을 동반한 AAG 환자에서 대조군보다 더 흔하게 발견되었다고 보고하였다 [47]. 이는 AAG의 임상 표현형(예: PA 동반 여부) 또한 유전적 요인에 의해 부분적으로 결정될 수 있음을 시사한다.
3.2.4. 위 자가항체(gastric autoantibodies)는 AAG의 병인에 어떤 역할을 하는가?
Position statement
: 위저선(oxyntic mucosa)의 위축성 손상을 직접적으로 유발하는 데 있어 위 자가항체의 역할은 아직 명확히 규명되지 않았다.
위벽세포의 H⁺,K⁺-ATPase에 대한 자가항체(parietal cell antibody, PCA) 와 내인자에 대한 자가항체(intrinsic factor antibody, IFA) 는 이론적으로 여러 기전을 통해 AAG 환자의 위점막 손상을 일으킬 수 있다고 여겨진다. 그러나 이러한 작용이 인체에서 실제로 입증된 사례는 없다. 또한 일부 AAG 환자에서는 혈청학적으로 자가항체가 검출되지 않는 음성형(seronegative type) 으로 나타나기도 하며, 이는 자가항체 이외의 다른 조직 손상 기전이 존재함을 시사한다. PCA는 항체의존성 세포독성(antibody-dependent cellular cytotoxicity, ADCC) 기전을 통해 위벽세포의 파괴(parietal cell killing) 를 촉진할 가능성이 있다. 반면, IFA는 내인자(intrinsic factor)의 기능적 결핍을 일으켜 비타민 B12 흡수 장애 → 결핍 → 악성빈혈(pernicious anaemia, PA) 로 이어지고, 이에 따른 신경학적 이상(neurological involvement) 및 비타민 B12 결핍으로 인한 여러 임상적 후속 결과(clinical sequelae) 를 초래한다 [1,44,48].
3.3. Diagnostic topics
3.3.1. 자가면역성 위축성 위염(AAG)에 대한 선별검사는 일반 인구집단 전체에 적용해야 하는가, 아니면 고위험군에 한정해야 하는가?
Position statement
: AAG 선별검사는 고위험군에서 분명한 이점을 가지지만, 현재 이용 가능한 근거에 따르면 일반 인구집단을 대상으로 한 보편적 선별검사(general population screening) 는 정당화되지 않는다. 따라서 보다 표적화된(targeted) 접근이 비용 효율적(cost-effective)이며, 임상적으로도 타당하며, 조기 진단율을 향상시킬 수 있을 것으로 보인다.
일반 인구를 대상으로 AAG 선별검사를 시행하기 위해서는 혈청검사(laboratory tests), 내시경 검사(endoscopy), 조직학적 평가(histological evaluation) 등이 필요하며, 이는 상당한 보건의료 비용(healthcare expenditures) 을 요구한다. AAG의 유병률이 최근 증가 추세를 보이고 있으나,
한 탐색적 연구(case-finding study)에서 15.5%의 유병률이 보고되었음에도 불구하고 [24], 전체 인구 수준에서의 임상적 유병률(clinical prevalence) 은 여전히 약 2%에서 5% 수준으로 낮게 유지되고 있다 [7,49]. 따라서 광범위한 선별검사를 시행할 경우 위양성(false positive) 결과가 다수 발생할 가능성이 높으며, 이는 불필요한 진단적 시술과 환자의 불안 증가(patient anxiety) 를 초래할 수 있다. 또한, 이러한 대규모 선별 프로그램을 관리·운영하는 데 필요한 보건의료 인프라의 부담은 잠재적 이익을 상회할 수 있으며, 일반 인구집단에서의 무증상 또는 초기 단계(subclinical/early-stage) 질환의 발견이 실제로 비용 대비 효용(cost-effectiveness)을 갖는지는 여전히 불분명하다. AAG의 조기 발견이 장기적인 합병증을 예방할 수 있다는 점은 분명하지만,
그로 인한 전체적인 진단 효율(yield) 이 의료 시스템이 감당해야 할 경제적·물리적 부담을 정당화할 만큼 크지는 않다는 것이 현재의 근거이다.
따라서 보다 효율적이고 비용 효율적인 접근법은 AAG의 유병률이 유의하게 높은 고위험군(high-risk population) 에 선별검사를 집중하는 것이다 [24,27]. 이러한 고위험군에는 다음과 같은 집단이 포함된다.
자가면역질환 가족력(family history of autoimmune diseases) 이 있는 사람
악성빈혈(pernicious anaemia, PA) 환자
제1형 당뇨병(type 1 diabetes) 환자 [50]
자가면역성 갑상선염(autoimmune thyroiditis) 환자 [51]
자가면역 다선증후군(autoimmune polyendocrine syndromes) 환자 [52]
소화불량 증상(dyspepsia) 을 호소하는 환자 [53]
불임(fertility issues) 이 있는 환자 — 최근 연구에서는 이와 AAG 간의 관련 가능성이 제시되고 있음 [54].
이러한 집단에서는 AAG의 유병률이 약 5~10%로 보고되며, 이들에서의 조기 발견(early detection) 은 악성빈혈이나 위종양(gastric malignancies) 과 같은 합병증의 예방 및 관리에 있어 매우 중요하다 [33].
3.3.2. 고위험군에서 자가면역성 위축성 위염(AAG)을 진단하기 위한 비침습적 선별검사(noninvasive screening tools)는 존재하며 유효한가?
Position statement
: 현재 AAG를 절대적으로 정확히 진단할 수 있는 단일 비침습적 검사법은 존재하지 않는다. 그러나 혈청 자가항체(anti-parietal cell antibody, PCA; anti-intrinsic factor antibody, IFA) 와 기타 혈청 표지자(펩시노겐, 가스트린-17 등) 을 조합하면, 약 80% 정도의 진단 정확도(overall accuracy) 를 보이며, 모든 경우에서 조직학적 확진(histological confirmation) 이 필요하다.
AAG의 확진은 위내시경(gastroscopy) 중 시행한 조직검사(biopsy)의 병리학적 판독(histopathology) 을 기반으로 한다. 내시경 전 선별검사(pre-endoscopic screening) 로서 혈청 표지자 검사는 AAG가 의심되는 임상 상황(예: 자가면역성 갑상선질환, 제1형 당뇨병 환자 등) 에서 유용하다. 이 중 한 항목이라도 양성일 경우, 내시경과 생검을 통해 확진 또는 배제해야 한다. 반면, 철결핍성 빈혈(iron-deficiency anaemia) 의 원인이 불명확하거나, 비타민 B12 결핍, 원인불명의 소화불량(dyspepsia), 위암 가족력(family history of GC) 이 있는 경우에는 혈청검사보다는 조기 내시경 및 전정부·체부 생검을 시행하여 조직학적으로 AAG 또는 다른 질환을 감별해야 한다 [27]. 이 접근법은 최근 발표된 RE.GA.IN 합의문(consensus) 과 일치한다 [7].
현재 이용 가능한 비침습적 표지자는 두 가지 그룹으로 구분된다.
위 자가면역 관련 표지자(autoimmunity-related markers)
위저선 점막 손상 및 위산분비 저하를 반영하는 표지자(functional/atrophy-related markers)
첫 번째 그룹은 AAG와 주로 연관, 두 번째 그룹은 H. pylori 감염에 의한 위축성 위염과 더 밀접한 관련이 있다 [1,7,27].
PCA는 AAG의 대표적 혈청 표지자이며 [1], 여러 ELISA 키트에서 민감도 80–100%, 특이도 90–99%를 보였다. 간접면역형광법(IIF)은 민감도 95–99%, 특이도 99%였으나, 정량적 측정이 가능한 ELISA가 임상적으로 더 선호된다 [56,57]. 아직 상용화되지 않은 용액상 발광면역침강검사(LIPS) 는 PCA의 두 아단위(ATP4A, ATP4B)를 개별적으로 검출할 수 있으며, 민감도 100%, 특이도 90%를 보였다 [58]. 그러나 PCA 양성은 건강인에서도 약 9%, H. pylori 관련 비위축성 또는 다병소성 위축성 위염 환자에서는 최대 20%까지 보고된다 [59,60]. 위축이 없는 PCA 양성 환자를 연 1회 내시경으로 추적한 결과, 중앙 추적기간 2년 내 약 절반이 명확한 AAG(overt AAG)로 진행하였다 [32]. 따라서 PCA 양성은 잠재성 AAG(potential autoimmune gastritis)의 초기 표지자로 간주될 수 있다. 반면, PCA 음성이라고 해서 AAG를 배제할 수는 없으며, 혈청음성형(seronegative AAG) 도 보고된 바 있다 [1,2].
IFA는 일반적으로 악성빈혈(pernicious anaemia, PA) 의 혈청 표지자로 간주되며 [61], 민감도 32–37%, 특이도 95–100%를 보인다 [57,58]. 흥미롭게도, PA나 비타민 B12 결핍이 없는 체부위축(corpus atrophy) 환자에서도 IFA 양성이 나타날 수 있으며 [57,62], 이는 임상적 PA 발생 수년 전의 초기 표지자(early marker) 일 가능성이 제시되었다 [26]. PCA와 IFA를 병합하여 평가하면 진단 신뢰도가 향상된다 [27,57,62].
가스트린(Gastrin) 증가는 위산 분비 저하로 인한 양성 되먹임(positive feedback) 결과이다 [1,2]. 그러나 프로톤펌프억제제(PPI) 사용이나 활성 H. pylori 감염이 존재하면 위체부 위축이 없어도 고가스트린혈증(hypergastrinaemia) 이 발생할 수 있다 [27]. 과거의 방사면역분석(RIA)은 현재 상용 ELISA 키트로 대체되었다 [63].
펩시노겐(PG) 은 위축의 또 다른 혈청 표지자이다.
위체부의 주세포(chief cell)는 PGI 및 PGII를 분비하고,
전정부의 유문샘은 PGII만 분비한다 [64].
체부 점막 위축이 진행되면 PGI는 감소하나 PGII는 유지, 결과적으로 PGI/PGII 비율의 점진적 감소가 나타나며, 이는 위암 위험 증가와도 관련이 있다 [65]. PG 수치는 PPI의 영향을 받지 않지만, PGI/II 비율의 저하는 H. pylori 관련 다병소성 위축성 위염에서도 관찰될 수 있다 [27]. 메타분석에 따르면, 펩시노겐을 이용한 위축성 위염 진단의 민감도 69%, 특이도 88%였다 [66].
또한, 가스트린-17을 포함한 전체 패널 검사의 체계적 문헌고찰에서는 AAG 진단에 대한 민감도 70.4%, 특이도 98.4%로 보고되었다 [67]. 다른 연구에서는 가스트린의 민감도 83.9%, 특이도 93.4%, PGI의 민감도 90.3%, 특이도 91%, PGI/PGII 비율의 민감도 83.9%, 특이도 93.7%를 보고하였다 [68].
“혈청 위 생검 검사(serum gastric biopsy)”라는 개념은 이러한 비침습적 내시경 전 평가를 지칭하기 위해 제안된 용어이다 [69]. PCA와 PGI를 병합할 경우 민감도 87%, 특이도 78%로 보고되었으며 [70], 최근의 연구에서는 PCA, IFA, PGI/II, Gastrin-17을 함께 평가한 결과, PGI/II 비율이 단독으로는 민감도 79%, 특이도 90% (AUC 0.90) 로 가장 우수하였고, PCA + PGI/II 조합 시에는 민감도 97%, 특이도 78% (AUC 0.93) 로 향상되었다 [71]. 또한, 내시경 및 생검을 시행한 344명의 환자(그중 44명은 AAG 확진)를 대상으로 한 다변량 분석에서 PGI 수치가 AAG와 유의하게 연관(p<0.001) 되었음이 보고되었다 [72].
3.3.3. 자가면역성 위축성 위염(AAG)의 진단은 위 전정부(antrum)와 체부(corpus) 생검의 조직학적 평가에 근거해야 하는가?
Position statement
: AAG의 진단은 반드시 조직학적 근거(histological grounds) 에 기반해야 하며, 전정부와 체부 양측의 조직 평가가 모든 경우에서 필수적이다. 이는 위염의 유형(classification of gastritis) 을 정확히 분류하기 위함이다.
AAG의 진단은 전정부(antrum)와 체부(corpus) 에서 채취한 위 생검조직의 병리학적 평가(histological evaluation) 를 근거로 해야 한다. 또한, AAG가 의심되는 환자에서는 정확한 내시경 관찰(accurate endoscopic examination) 이 매우 중요하다 [1,2,7,73–77]. 이러한 접근법은 AAG를 다른 형태의 만성 위염(chronic gastritis), 예를 들어 H. pylori 관련 위염(H. pylori–associated gastritis) 과 구분하는 데 도움을 준다. 후자는 주로 전정부(antrum) 를 침범하는 반면, AAG는 체부(corpus) 및 저부(fundus) 에 국한된 염증을 보이는 것이 특징이다.
특히, AAG와 H. pylori 감염이 공존(coexist) 하는 경우도 존재하며, 이러한 상황에서는 위암(gastric cancer, GC) 의 위험이 더욱 증가할 수 있다 [1,2,7]. 따라서 위의 모든 부위(stomach compartments) 에서 생검을 시행하는 것은 위점막 전체의 병변을 포괄적으로 평가(comprehensive evaluation) 하고, 정확한 질환 분류 및 추적감시(surveillance) 를 가능하게 하는 핵심적 절차이다. 내시경 생검은 Sydney system의 최신 개정판(updated Sydney system) 을 따라 시행해야 하며, 이는 다음과 같이 구성된다 [6].
또한, 의심 병변(suspicious regions) 이 관찰될 경우에는 반드시 별도의 시료(separate sampling) 로 추가 생검(additional biopsy) 을 시행해야 한다.
3.3.4. 자가면역성 위축성 위염(AAG) 진단을 위한 내시경적 기준은 존재하며, 그 타당성이 입증되었는가?
Position statement
: AAG의 내시경 소견은 병변의 심한 정도(severity) 에 따라 다양하며, 비특이적(nonspecific) 인 경우가 많다. 따라서 내시경 소견만으로 AAG를 진단할 수 있는 표준화된 분류(classification)는 존재하지 않는다.
내시경 검사와 병리학적 평가(histopathology)는 AAG 진단에서 모두 중요한 역할을 하지만, 내시경 단독 진단의 독립적 타당성(independent validity) 은 여전히 연구 중이다. AAG의 전형적인 내시경 소견은 다음과 같다 [6,73–75].
창백하고 위축된 위점막(pale, atrophic gastric mucosa)
노출된 점막하 혈관(submucosal vessels)
위 주름의 소실(loss of gastric folds)
그러나 이러한 소견은 AAG에만 특이적인 것은 아니며, H. pylori 감염에 의한 위축성 위염(atrophic gastritis) 등 다른 형태의 만성 위염에서도 유사하게 나타날 수 있다. 몇몇 연구에서는 초기 단계(early-stage) AAG의 내시경 소견을 기술하였는데, 특히 다음과 같은 형태가 초기 자가면역성 위염에 비교적 특이적으로 제시되었다 [18].
또한, AAG의 또 다른 중요한 내시경 소견으로 다발성 위용종(multiple gastric polyps) 의 존재가 보고되었다. 최근 발표된 AGAPE 연구(AGAPE study) 에 따르면, AAG 환자에서 염증성 또는 과형성(polypoid hyperplastic) 등 비신생성(non-neoplastic) 용종의 발생 빈도가 상당히 높음을 확인하였다 [78]. 최근에는 협대역영상(narrow-band imaging, NBI) 을 활용하여 AAG 환자에서 장상피화생(gastric intestinal metaplasia) 을 탐지하는 정확도를 높이려는 시도가 이루어졌다. NBI는 높은 민감도(high sensitivity) 를 보였으나, pseudopyloric metaplasia와의 영상적 중첩(overlap) 으로 인해 특이도(specificity) 는 낮은 것으로 보고되었다 [79,80]. 또한, AI 기반 내시경 진단 시스템(SEER-SCOPE AI) 이 최근 개발되어, 다른 형태의 위염과 AAG를 전문가 수준의 정확도(expert-level accuracy) 로 구별할 수 있음이 입증되었으며, 이는 향후 AAG 내시경 진단의 정확도 향상에 기여할 잠재력을 보여주었다 [81]. 그럼에도 불구하고, AAG의 내시경 소견은 비특이적 특징(nonspecific features) 이 많고, 다른 형태의 위염과 중첩(overlap) 될 가능성이 높기 때문에 AAG의 확진(gold standard) 은 여전히 조직학적 진단(histopathology) 에 기반해야 한다 [7,27].
3.3.5. 자가면역성 위축성 위염(AAG)에서 현재 또는 과거의 헬리코박터 파일로리(Helicobacter pylori) 감염을 반드시 배제해야 하는가?
Position statement
: AAG의 진단 과정(diagnostic work-up)에서는 현재 또는 과거의 H. pylori 감염 여부를 확인하거나 배제하는 과정이 필수적이다. 이를 위해 조직병리학적 검사(histopathology), 혈청 IgG 항-H. pylori 항체 검사(serology assay), 그리고 환자의 병력(anamnestic data) 이 함께 평가되어야 한다.
AAG는 숙주(환자) 요인에 의해 유발되는 위 염증 질환(host-related gastric inflammatory condition) 으로, 환경적 요인(environmental factor)에 의해 발생하는 H. pylori 감염 관련 위축성 위염과 구분된다. 그러나 AAG의 병인에서 과거 혹은 현재의 H. pylori 감염이 어떤 역할을 하는지는 아직 명확히 규명되지 않았다. AAG 환자의 일부에서는 H. pylori 감염 자체가 자가면역성 염증반응(autoimmune inflammatory process) 을 유발할 수 있으며 [7], 그 주요 기전으로는 위벽세포의 H⁺,K⁺-ATPase 항원과 H. pylori 유래 항체 간의 항원모방(antigen mimicry) 이 제시된다 [40–44]. 최근 약 1,600명의 AAG 환자를 대상으로 한 다기관 연구(multicentre study) 에서는 H. pylori 비감염군(naïve AAG) 과 H. pylori 노출군(H. pylori–exposed AAG) 사이에 임상적 특징의 차이가 보고되었다. 비감염군에서는 H. pylori 노출군에 비해 다음과 같은 동반 소인이 더 흔했다 [14].
AAG의 가족력(1차 친족 내 발생) (p = 0.012)
제1형 당뇨병(type 1 diabetes) (p = 0.024)
악성빈혈(pernicious anaemia, PA) (p = 0.003)
조직학적으로 AAG와 H. pylori 관련 위축성 위염을 구분하는 가장 중요한 특징은 전정부(antral mucosa)가 보존(spared) 되어 있다는 점이다 [1,7]. 그러나 최근 한 연구에서는, 체부 위축(corpus atrophy)과 전정부 염증(antral gastritis)이 함께 존재하는 일부 환자군에서 H. pylori 제균치료 여부와 관계없이 장기 추적 시 전정부 점막이 회복되는 소견이 관찰되었으며, 이러한 경우는 AAG와 유사한 형태를 보일 수 있어 일차성(primary) AAG와 이차성(secondary) AAG를 구별하는 데 어려움을 야기한다고 보고하였다 [82]. 이러한 결과는 “H. pylori 비감염성 위염(naïve gastritis)은 전정부 점막이 보존된다”는 기존 개념과 상충된다 [7].
3.3.6. 자가면역성 위축성 위염(AAG)에서 현재의 조직학적 점수체계(Updated Sydney system, OLGA, OLGIM)는 유용한가?
Position statement
: OLGA 및 OLGIM 체계는 위암(GC) 위험 평가에 유용하다고 여겨지지만, 이들은 전정부(antrum)의 병변을 함께 고려하기 때문에, 전정부가 보존되는 AAG의 중증도(severity)를 과소평가(underestimate) 하는 경향이 있다.
현재 사용되는 조직학적 점수체계는 AAG의 평가에 유용하지만, 몇 가지 한계(limitation) 가 존재한다. 이들에는 다음이 포함된다.
Updated Sydney System: 위염의 분류(classification)를 위한 기본 체계로, 염증(inflammation), 위축(atrophy), 장상피화생(intestinal metaplasia)을 평가한다.
OLGA (Operative Link on Gastritis Assessment) 및 OLGIM (Operative Link on Gastric Intestinal Metaplasia Assessment):
위축성 위염과 장상피화생의 정도를 기반으로 위암 위험을 병기(staging) 로 분류한다.
Updated Sydney System은 여전히 조직학적 진단(histological diagnosis) 의 기본 틀로 사용되지만, 관찰자 간 차이(interobserver variability) 로 인해 재현성(reproducibility) 에 한계가 있다 [1,6,7]. 특히 위축과 염증의 정도를 평가하는 데 있어 병리학자 간 일치도는 낮거나 중등도 수준(low to moderate agreement) 으로, 위축 평가의 경우 κ(카파) = 0.31–0.6 범위에 머무른다 [86]. 반면, 장상피화생(intestinal metaplasia) 은 조직학적 특징이 명확하기 때문에 평가자 간 일치도가 더 높으며, κ = 0.62–0.9 로 보고되었다 [87]. OLGA 및 OLGIM 체계는 위축성 위염과 장상피화생의 정도를 평가하여 위암 위험도(risk stratification) 를 분류하는 데 널리 사용된다 [88]. 이 체계들은 광범위한 위축(atrophy) 또는 장상피화생(metaplasia) 을 보이는 고위험 환자를 선별하여 내시경 추적감시(endoscopic surveillance) 의 필요성을 판단하는 데 도움을 준다.
그러나 AAG의 병변은 대부분 위체부(corpus)에 국한되고 전정부는 보존되기 때문에, OLGA 및 OLGIM 체계에서는 높은 병기(high stage) 에 도달하지 못하는 경우가 많다. 이들 점수체계는 체부와 전정부의 위축 정도를 함께 합산하여 병기를 산정하므로, 전정부 위축이 없는 AAG는 낮은 병기(stage I–II) 로 분류되는 경향이 있다. 이로 인해 체부 제한성 위축(corpus-restricted atrophy) 의 실제 중증도가 과소평가될 수 있다. 결과적으로, OLGA 및 OLGIM 체계는 다병소성 위축성 위염(multifocal atrophic gastritis) 의 위암 위험 평가에는 여전히 유용하지만, 자가면역성 위축성 위염(AAG) 에 적용할 때에는 그 임상적 활용도(clinical applicability) 가 제한적이다 [7].
3.3.7. 현재의 자가면역성 위축성 위염(AAG) 진단 기준은 충분히 만족스러운가?
Position statement
: 현재의 AAG 진단 기준(diagnostic criteria) 은 여러 측면에서 완전히 만족스럽지 않다. 그 이유는 다음과 같다:
불완전하고 일관성 낮은 생물학적 표지자(biomarkers) 에 대한 의존,
혈청음성형(seronegative) 사례의 존재,
조직학적 진단의 어려움(histological challenges),
동서양 간 진단 기준의 불균질성(heterogeneity between Eastern and Western countries) 때문이다.
따라서 혈청학(serology), 내시경(endoscopy), 조직병리학(histopathology) 을 통합적으로 결합한 접근법이 가장 합리적인 진단 방법으로 권장된다.
현재 사용 중인 AAG의 진단 기준에는 여러 한계가 존재한다. 기존의 조직학적·혈청학적·생화학적 진단 방법은 도움이 되지만, 완전한 진단법이라고 보기 어렵다(3.3.2 및 3.3.6 참고). AAG는 H. pylori 관련 위축성 위염(atrophic gastritis) 과 중첩(overlap)될 수 있으며, 현재까지 보편적으로 인정된 진단 기준(universally accepted criteria) 은 없다.
조직학적 진단(histopathology-based diagnosis)의 핵심은 전정부(antral mucosa)의 보존(spared mucosa) 이며, 이는 H. pylori 감염을 배제(exclude) 하는 가장 신뢰할 만한 지표로 간주된다 [7]. 그러나 최근 연구에 따르면, 다병소성 위축성 위염(multifocal atrophic gastritis) 의 일부 환자에서는 전정부 점막이 위축되어 있더라도 장기 추적 시 점막이 회복(healing) 될 수 있으며, 이로 인해 AAG와 유사한 형태를 보이게 되어(primary vs. secondary AAG) 두 질환을 구분하기 어려워진다고 보고되었다 [82].
PCA (anti–H⁺,K⁺-ATPase 항체) 와 IFA (anti–intrinsic factor 항체) 는 AAG의 대표적 혈청 표지자이지만, 모든 환자에서 존재하지 않으며, 서구 국가(Western countries) 의 진단 기준에서는 이 항체들이 필수 요건(necessary criteria) 으로 간주되지 않는다 [1,7]. 그럼에도 미국 및 영국 진단지침(American and British guidelines) 은 이 항체 검사를 AAG 진단을 보조(supportive)하기 위한 평가 항목으로 권장하고 있다 [75,76].
반면, 동양(Eastern countries), 특히 일본의 진단 기준에 따르면, 다음 두 조건을 모두 만족할 경우 AAG로 간주한다 [80].
내시경적 및/또는 조직학적 소견(endoscopic and/or histopathological findings)
PCA 또는 IFA 양성(seropositivity)
AAG 환자의 약 20%는 조직학적으로 확진되었을 때 혈청 음성(seronegative) 상태를 보인다 [27,89]. 이는 특히 질환의 후기 단계(late stage) 와 고령 환자에서 흔하다. 질환이 진행하면서 위벽세포(parietal cell) 가 광범위하게 파괴되면, 면역계가 더 이상 반응하지 않아 PCA 수치가 자연적으로 감소 또는 소실될 수 있다. 또한, 고령에서의 면역기능 변화(immune senescence) 와 질환의 장기 경과(prolonged disease course) 도 혈청음성 상태에 기여할 수 있어, 항체검사에만 의존한 진단은 불충분하다.
AAG 진단의 골드 스탠다드(gold standard) 는 여전히 위생검(gastric biopsy)의 병리학적 확진(histopathological confirmation) 이며, 이는 RE.GA.IN 합의문(consensus) 에서도 명시되어 있다 [7]. 그러나 현실적으로 다음과 같은 문제점이 존재한다.
초기 병변(early-stage changes) 이 항상 명확하지 않을 수 있음
생검 부위가 불명확하거나(sampling site unspecified)
시료가 불충분(inadequate sampling) 하거나
Updated Sydney protocol 에 따라 채취되지 않는 경우 [75,90]
이러한 경우, 특히 생검 부위나 임상 병력이 불분명할 때, 호산구 침윤(eosinophil infiltration) 이 잠재적 진단 보조 지표(potential diagnostic marker) 로 제시되었으며, 이는 특히 소아 환자(pediatric patients) 에서 유용할 수 있다 [91,92]. 비침습적 검사(noninvasive tests) 측면에서, 혈청 바이오마커 패널(serological biomarker panel) 인 GastroPanel® 은 AAG의 조기 선별(early screening)에 유망하나, 기존 연구 대부분이 다병소성 위축성 위염(multifocal atrophic gastritis) 에 초점을 맞추었기 때문에 AAG에 대한 검증(validation) 이 추가로 필요하다 [27,55]. 또한, 비타민 B12, 혈색소(haemoglobin), 가스트린(gastrin), 크로모그라닌 A(chromogranin A) 등을 결합한 생화학적 점수체계(biochemical score) 가 제안되었으며, 좋은 진단 정확도를 보였으나, 이 역시 추가 검증이 필요하다 [93].
3.4. Management
3.4.1. 자가면역성 위염(AAG) 환자에서 동반된 헬리코박터 파일로리(H. pylori) 감염을 치료해야 하는가?
Position statement
: AAG 환자에서 H. pylori 감염이 동반되어 있다면 반드시 제균 치료를 시행해야 한다.
H. pylori는 세계보건기구(WHO) 산하 국제암연구소(International Agency for Research on Cancer, IARC)에 의해 1군(Group I) 발암인자로 분류되어 있다 [7, 94]. H. pylori 감염 환자는 위암 발생 위험이 비감염자에 비해 3~6배 높으며, 제균 치료 후 그 위험이 유의하게 감소한다 [95]. 무작위대조시험(RCT)의 메타분석에 따르면, 제균 치료를 받은 환자에서 위암 발생 위험(RR 0.54, 95% CI 0.40–0.72) 및 위암 관련 사망률(RR 0.61, 95% CI 0.40–0.92) 이 모두 감소하였다 [96].
H. pylori가 AAG로 진행하는 면역학적 과정을 직접적으로 유발할 수 있는지는 아직 명확히 입증되지 않았다 [1, 41, 97]. 그러나 H. pylori 감염은 AAG 환자에서 신생물(위암 등) 위험 증가와 연관될 수 있다.
초기의 연구들에서는 H. pylori 감염 여부가 불분명하거나(‘pre-H. pylori era’) 과거에 감염이 있었던 환자들을 포함한 집단에서 AAG 관련 위암 위험이 높다고 보고하였으나, 이러한 혼재된 병인(mixed aetiology) 으로 인해 순수한 AAG 환자의 위암 위험을 정확히 평가하기 어려웠다.
최근 발표된 장기 전향적 연구에서는 ‘순수 AAG(pure AAG)’ 환자 211명을 평균 10,541인년(person-years) 추적 관찰하였고, 저등급 이형성 5예만 발생하였으며 고등급 이형성이나 침윤성 위암은 한 건도 보고되지 않았다 [31]. 이러한 거의 부재한 위암 위험은 다른 연구자들에 의해서도 확인되었다 [29]. 반면, 일부 전향적 단일기관 및 후향적 다기관 연구에서는 AAG 환자의 위암 위험이 0은 아니지만 매우 낮은 수준으로 보고되었다 [14, 30]. 현재까지의 근거에 따르면, H. pylori 감염이 없거나 이미 소실된 AAG 환자에서도 위암 발생 가능성을 완전히 배제할 수는 없으나, 그 위험은 낮다.
특히, 다병소성 위축(multi-focal atrophy, 광범위 위축성 위염) 과 장상피화생(intestinal metaplasia) 의 존재는 위암 위험을 높이는 요인으로 알려져 있다 [74–76, 98, 99]. AAG 환자에서 H. pylori 감염이 현재 또는 과거에 존재한 경우, 위점막의 위축 및 화생 병변은 전정부의 점액선(H. pylori 매개) 과 체부 또는 위저부의 벽세포선(자가면역 매개) 을 모두 침범할 수 있다. 이러한 광범위한 위축성 변화(extensive atrophy) 는 순수한 벽세포선 제한적(autoimmune-restricted) 손상보다 위암 발생 위험이 더 높다 [100]. 따라서, AAG 환자에서 H. pylori 감염이 확인되면 제균 치료를 반드시 시행해야 하며, 이는 위점막 손상의 진행을 억제하고 위암 발생 가능성을 줄이기 위함이다 [7].
또한, 이중 빈혈(dimorphic anemia) 은 AAG 후기 단계에서 흔히 관찰되며, 평균 적혈구 용적(MCV)은 정상이나 적혈구 크기의 불균일(anisocytosis) 을 보인다. 이는 철결핍성 빈혈과 비타민 B12 결핍이 동시에 존재하기 때문이다 [101]. 한편, 철결핍성과 비타민 B12 결핍은 H. pylori 감염 자체와도 관련이 있을 수 있으므로 [94], AAG 환자에서 H. pylori 제균 치료는 위암 예방뿐 아니라 철분 및 비타민 B12 결핍 개선에도 도움이 된다.
3.4.2. AAG 환자에서 H. pylori 제균치료가 질환의 자연경과나 예후에 영향을 미칠 수 있는가?
Position statement
: 이미 발생한 위 병변을 H. pylori 제균치료로 호전시키기는 어렵다. 그러나 제균은 위 점막의 염증을 감소시키며, 장기적인 합병증을 예방하는 데 도움이 될 수 있다.
AAG 환자는 위암(gastric cancer, GC) 과 제1형 위 신경내분비종양(type 1 gastric neuroendocrine neoplasms, t1-gNENs) 발생 위험이 증가되어 있다 [1, 2, 8]. 최근의 연구들에 따르면 AAG에서 위암의 절대 위험은 낮은 것으로 보이지만 [13, 29–31], t1-gNENs는 내시경 및 조직학적 추적관찰을 시행한 환자의 4–12% 에서 관찰된다 [1]. 위암의 발암 과정은 다단계(multi-step)로 진행되며, 그 중 위축성 위염(atrophy) 과 장상피화생(intestinal metaplasia) 은 대표적인 전암 병변(precancerous conditions)으로 간주된다 [83].
AAG 환자에서도 H. pylori 감염은 위 점막의 만성 염증(chronic inflammation) 을 유발하는 추가적인 자극 요인으로 작용하여, 만성 위축성 위염, 장상피화생, 위암 의 발달에 기여할 수 있다. 따라서, 세균 제균이 이러한 병적 상태의 진행을 억제하거나 일부 회복을 유도할 수 있는 예방적 전략으로 간주될 수 있다 [7, 83, 94]. 다만, 위 체부(corpus)를 침범한 만성 위축성 위염에서 위산분비가 저하된 경우, 비침습적 검사(요소호기검사, 대변항원검사)를 이용한 H. pylori 감염의 검출 신뢰도는 낮을 수 있다 [85]. 그럼에도 불구하고, 감염이 확인되면 반드시 제균치료를 시행해야 한다 [83, 102].
그러나, 이미 위축성 위염과 장상피화생이 형성된 이후에는 제균치료로 이들 병변이 가역적으로 회복되는지 여부는 논란의 여지가 있다. 메타분석에 따르면 H. pylori 제균은 위축성 병변의 개선에는 장기적인 이익이 있으나, 장상피화생에 대해서는 거의 효과가 없거나 제한적인 것으로 보고되었다 [103–105].
즉, 장상피화생은 H. pylori 제균 이후에도 되돌리기 어렵거나 매우 제한적으로만 회복되는 ‘위암 발생의 비가역적 단계(point of no return)’ 로 간주된다.
그럼에도 불구하고, 위축성 위염과 장상피화생이 존재하는 환자에서도 H. pylori 제균은 병변의 추가 진행을 억제하기 위해 권장된다.
한편, gastrin-17의 지속적인 증가는 enterochromaffin-like (ECL) 세포의 증식, 이형성(dysplasia), 그리고 t1-gNENs 의 잘 알려진 위험 요인이다 [106]. AAG의 자연경과에서 선상(linear) 및 결절성(nodular) ECL 세포 과형성이 선종양(adenomatoid) 과형성/이형성 및 t1-gNENs 로 진행하는 양상은 주로 광범위한 위산분비세포(oxyntic mucosa) 위축을 가진 환자에서 관찰된다 [30, 31]. 이러한 위저선 위축(oxyntic atrophy) 과 선종양 과형성/이형성 및 t1-gNENs 간의 연관성은 잘 확립되어 있으며, 선종양 과형성/이형성은 t1-gNENs 발생의 예측 인자로 알려져 있다 [1, 107].
반면, H. pylori 감염은 t1-gNENs의 발생에 직접적인 병인적 역할을 하지 않는다.최근의 다기관 후향적 연구에 따르면, t1-gNENs는 H. pylori 비감염(AAG H. pylori-naïve) 환자의 10.1%, 감염력(H. pylori-exposed)이 있었던 AAG 환자의 8.1% 에서 발생하였으며, 이는 통계적으로 유의한 차이를 보이지 않았다 (보정 후 HR 0.74, 95% CI 0.41–1.35) [14]. 이전 연구에서는 H. pylori 제균 후 일부 환자에서 위산분비 기능 및 ECL 세포 과형성이 부분적으로 회복되며, 감염이 조직학적으로 완전히 치유된 환자의 절반 이상에서 ECL 세포 과형성이 감소함을 보고하였다 [108]. 그러나 이러한 변화가 t1-gNENs의 발생에 실제로 영향을 미치는지는 아직 입증되지 않았다. 결론적으로, AAG에서 H. pylori 감염과 제균치료는 t1-gNENs의 발생과 질병 예후에 실질적인 영향을 미치지 않는 것으로 보인다.
3.4.3. AAG 환자에서 제균치료 요법은 유효한가?
Position statement
: 현재까지 AAG 환자에서 H. pylori 제균을 위한 특정 치료 요법을 권고할 만큼의 근거는 부족하다. 그러나 프로톤펌프억제제(PPI)를 사용하지 않고도 제균이 가능한 것으로 보인다.
H. pylori 감염의 제균 치료 요법은 일반적으로 비스무트(bismuth) 기반 요법이 가장 많이 사용되며, 그 외에 순차요법(sequential therapy) 또는 복합요법(hybrid therapy) 이 사용된다 [109–111]. 무작위대조시험(RCT)에 따르면, 비스무트, 메트로니다졸(metronidazole), 테트라사이클린(tetracycline), PPI를 병용한 고전적 4제요법(bismuth quadruple therapy) 이 3제요법(triple therapy) 보다 H. pylori 제균율이 더 높았다 [112, 113]. 과거에는 이러한 다중 약제 복용의 복잡성이 단점이었으나, 단일 제형(single-pill) 비스무트 기반 요법(SPBT) 의 개발로 이를 극복할 수 있게 되었으며, 이 요법은 임상시험뿐 아니라 실제 진료에서도 높은 제균 성공률을 보였다 [109]. 다만, 지금까지의 제균치료 관련 연구들은 AAG 환자를 대상으로 한 연구는 거의 없었다.
AAG는 위산 분비 저하와 위내 pH 상승이 특징적이므로, 이러한 환자에서 PPI의 사용 필요성은 논란의 여지가 있다 [114]. 최근 한 연구에서는 위체부 위축성 위염(corpus atrophic gastritis) 환자 76명 중 H. pylori 감염이 조직학적으로 확인된 환자들을 대상으로, PPI를 사용하지 않는 변형 제균 요법의 내약성과 효과를 평가하였다. 1차 치료로 아목시실린 기반 병용 또는 순차 요법(amoxicillin-based therapy, ABT; n=30) 과 비스무트 단일 제형 요법(single-pill bismuth therapy, SPBT; n=46) 이 처방되었다. 전체 제균율은 90.1% (95% CI 69.4–115.1%) 로 나타났으며, SPBT의 제균율이 ABT보다 유의하게 높았다 (SPBT: 97.7%, 95% CI 70.4–132.0% vs ABT: 78.6%, 95% CI 49.2–118.9%, p = 0.013). 이 결과는 위체부 위축성 위염 환자에서도 PPI를 사용하지 않고 90% 이상의 제균 성공률을 달성할 수 있음을 보여준다 [115].
3.4.4. AAG 환자는 위 신생물 병변의 조기 진단을 위해 내시경 추적관찰(endoscopic surveillance)로부터 이득을 얻을 수 있는가?
Position statement
: AAG 환자는 위 제1형 신경내분비종양(gastric type 1 neuroendocrine neoplasms, t1-gNENs), 드물게는 위 이형성(gastric dysplasia) 또는 위암(gastric cancer, GC) 의 조기 진단을 위해 내시경 추적관찰로부터 임상적 이득을 얻는다는 충분한 근거가 있다. 다만, 적절한 추적 시기와 보다 정밀한 위험도 층화(risk stratification) 에 대해서는 추가적인 규명이 필요하다.
앞서 언급한 바와 같이, AAG 환자는 위 t1-gNENs 및 위암의 발생 위험이 증가되어 있다 [1, 2]. 최근 조직학적으로 확진된 AAG 또는 위체부 제한성 위염(corpus-restricted gastritis) 환자들을 대상으로 한 전향적 연구들에서도 위 t1-gNENs 발생 위험이 일관되게 높음이 확인되었으며, 위암 발생 위험에 대해서는 아직 상반된 결과가 보고되고 있다. 4.3~7년의 추적기간 동안, 두 연구 [29, 31] 에서는 각각 저등급 이형성(low-grade dysplasia) 5예 및 14예가 보고되었고, 다른 두 연구 [29, 30] 에서는 각각 고등급 이형성(high-grade dysplasia) 4예 및 1예가, 또 한 연구 [30]에서는 위암(GC) 6예가 발생하였다. 한편, 다기관 후향적 연구에서는 AAG 환자의 위암 발생 위험이 매우 낮지만 0은 아닌 것으로 보고되었다 [14].
이러한 결과의 차이는 연구마다 H. pylori 관련 AAG 환자 포함 비율의 차이에 기인할 수 있다. 예를 들어, 두 연구에서는 H. pylori 감염 환자를 제외하였으나, 한 연구에서는 현재 혹은 과거의 H. pylori 감염 환자를 배제하지 않았음에도, 새롭게 발생한 위암 또는 고등급 이형성은 모두 H. pylori 음성 환자에서 발생하였고, H. pylori 양성 환자에서는 저등급 이형성 2예만 보고되었다.
그러나, 다른 염증성 암(inflammatory cancers) 의 경우와 마찬가지로, 만성 염증이 일정 수준 이상의 조직 손상에 도달하면, 초기 유발 요인(trigger)과 무관하게 시간이 경과함에 따라 암으로 진행할 수 있음이 알려져 있다. 따라서, 위체부 위축(corpus atrophy) 또는 장상피화생(intestinal metaplasia) 이 오래 지속된 AAG 환자에서는 이러한 만성 염증성 손상이 신생물 합병증(neoplastic complications) 으로 진행할 수 있다.
가장 최근의 유럽 가이드라인(European guidelines) 은 AAG 환자에서 위 t1-gNENs와 위암의 조기 발견을 위해 3년마다 고품질(high-quality) 내시경 추적관찰을 시행할 것을 권고하고 있다 [74]. 반면, 미국 가이드라인(American guidelines) 은 AAG 환자에서 최적의 추적관찰 주기는 명확히 확립되지 않았다고 기술하며, 환자 개별 특성과 의사-환자 간 공동 의사결정(shared decision making) 을 기반으로 추적간격을 조정해야 한다고 제시한다 [75].
영국 가이드라인(British guidelines) 역시 AAG 자체에 대한 명시적인 추적관찰 권고는 없으며, 광범위한 위축(extensive atrophy) 또는 장상피화생 이 있는 환자에 한해 3년 간격의 내시경 추적관찰을 권장한다. 그러나 주목할 점은, 악성빈혈(pernicious anemia, PA) 을 위암의 강력한 위험요인 중 하나로 간주하고 있다는 것이다 [76]. 또한, 위암의 직계가족력(first-degree family history) 이 있거나 지속적인 H. pylori 감염이 존재하는 경우, 내시경 추적관찰은 1~2년마다 시행하는 것이 권장된다.
3.4.5. AAG 환자의 내시경 추적관찰은 전자 염색내시경(electronic chromoendoscopy)과 위 생검(random/targeted biopsy)을 병행하여 시행해야 하는가?
Position statement
: AAG 환자의 최적의 추적관찰 전략은 고해상도(high-definition) 내시경과 전자 염색내시경(electronic chromoendoscopy) 을 이용하여 이상 부위에 대한 표적생검(targeted biopsy) 과 전정부(antrum) 및 체부(corpus)의 무작위생검(random biopsy) 을 병행하는 것이다.
내시경적으로 AAG는 특히 초기 단계에서 정상 위점막과의 구별이 어렵다. 질병이 더 진행된 단계에서는 급성 염증 소견이 나타날 수 있으며, 이는 평탄해진 위체부 주름(flattened gastric corpus folds), 점막 부종(mucosal swelling), 발적(redness) 등으로 특징지어진다. 질환이 진행함에 따라 위체부(corpus)와 위저부(fundus)의 위축(atrophy) 이 명확해지며, 점막이 창백해지고(pale mucosa) 점막이 얇아지면서 점막하 혈관(submucosal vessels) 이 비쳐 보이는 소견이 관찰된다. 반면, 전정부(antrum) 는 대체로 정상으로 유지되는 경우가 많다 [74, 75, 80].
진단 정확도를 극대화하기 위해 내시경의사는 점막 시야의 최적화(optimal mucosal visualization) 를 보장해야 한다. 이를 위해 소포제(defoming agent) 및 점액용해제(mucolytic agent) 인 시메티콘(simethicone) 과 1% N-아세틸시스테인(N-acetylcysteine) 의 사용이 도움이 될 수 있으며, 단순한 물 세척(water irrigation)만으로는 효과적인 점막 세정이 어려울 수 있다 [73–77].
고해상도 내시경(high-definition endoscopy) 과 염색내시경(chromoendoscopy, CE) 의 병용은 위의 전암 병변(precancerous conditions) 및 조기 신생물 병변(early neoplastic lesions) 진단에 있어, 단독 백색광 내시경(high-definition white-light endoscopy)보다 우수하다고 알려져 있다 [73, 74]. 따라서, 가능하다면 전자 염색내시경(electronic CE) 을 확대관찰 유무와 관계없이 활용하는 것이 권장되며, 이를 통해
전암성 병변 진단,
위축 및 화생 병변의 병기 설정(staging)을 위한 생검 가이드,
조기 신생물 병변 탐지 에 도움을 받을 수 있다 [73–77].
비록 최신 내시경 기술의 해상도가 높아졌지만, 현재의 권고안들은 여전히 표준화된 생검 프로토콜(standardised biopsy protocol) 의 적용을 강조하고 있다. 즉, 최소 두 부위(antrum과 corpus) 에서 소만(lesser curvature) 과 대만(greater curvature) 을 각각 포함한 생검을 시행해야 하며, 두 개의 별도 용기(vial) 에 구분하여 담아야 한다. 또한, 내시경적으로 신생물 의심 병변이 관찰되는 부위에서는 추가적인 표적생검(targeted biopsy) 을 시행해야 한다 [73–77]. 가장 최근의 유럽 MAPS III 가이드라인 은, 기저 내시경(baseline endoscopy)에서 위축 또는 장상피화생이 관찰되었더라도 내시경적으로 명확한 병변이 보이지 않는 경우에는, 추적 내시경 시 루틴 위생검(routine gastric biopsy)을 반드시 시행할 필요는 없다고 명시하고 있다 [74].
3.4.6. AAG 환자에서 동반질환이나 관련 질환에 대한 선별검사는 유용한가?
Position statement
: 새롭게 진단된 모든 AAG 환자는 미량영양소 결핍(micronutrient deficiencies), 빈혈(anaemia), 그리고 자가면역 갑상선질환(autoimmune thyroid disease) 및 셀리악병(coeliac disease) 을 포함한 기타 연관 자가면역질환(associated autoimmunity) 에 대한 선별검사를 시행해야 한다.
AAG 환자는 여러 영양소의 흡수 장애(malabsorption) 위험이 높으며, 특히 비타민 B₁₂, 철(iron), 칼슘(calcium), 비타민 D 결핍이 흔하게 동반된다 [116, 117]. 또한, 이들은 다른 자가면역질환(autoimmune comorbidities) 이 병발할 가능성이 높다. 따라서, 초진 시(first evaluation) 모든 AAG 환자에서 미량영양소 결핍과 빈혈 여부를 선별검사(screening) 해야 한다 [1, 2, 101]. 더불어, 무증상(asymptomatic) 혹은 경증 증상(mildly symptomatic) 으로 나타날 수 있는 자가면역질환에 대해서도 선별검사가 필요하다. 대표적으로, 자가면역 갑상선질환(autoimmune thyroid disease) 의 확인을 위해
TSH (thyroid-stimulating hormone),
항갑상선과산화효소항체(anti-thyroid peroxidase antibody, anti-TPO),
항타이로글로불린항체(anti-thyroglobulin antibody, anti-Tg),
항-TSH 수용체항체(anti-TSH receptor antibody)
를 측정해야 한다.
또한, 셀리악병(coeliac disease) 의 선별을 위해서는 항-조직 트랜스글루타미나제 IgA 항체(anti-tissue transglutaminase IgA antibody) 검사를 시행해야 한다. 그 외의 질환들은 임상 증상 및 징후(clinical manifestations) 에 따라 선택적으로 평가할 수 있다. 한편, 공통가변면역결핍(common variable immune deficiency, CVID) 환자의 상당수에서 전반적 위축성 위염(atrophic pangastritis) 이 동반된다는 사실이 보고되어 있으므로, 이러한 경우에는 총 면역글로불린(total immunoglobulins) 과 IgA, IgG, IgM 의 측정이 권장된다 [1].
3.4.7. AAG 환자에서 미량영양소 결핍(micronutrient deficiencies)은 어떻게 치료해야 하는가?
Position statement
: AAG 환자는 비타민 B₁₂의 평생 보충요법(lifelong supplementation) 이 필요하며, 가능하면 비경구적(parenteral) 투여가 권장된다. 또한 엽산(folic acid) 은 비타민 B₁₂와 상승 작용(synergistic effect) 을 보이므로 함께 보충해야 한다. 그 외 철(iron) 및 비타민 D 와 같은 미량영양소는 정기적으로 검사하여 결핍 시 보충해야 한다.
비타민 B₁₂는 특히 임상적으로 중증 증상을 보이는 경우 비경구적(parenteral) 으로 보충해야 한다. 일반적으로 시아노코발라민(cyanocobalamin) 을 매월 1,000 IU에서 3개월마다 5,000 IU까지 근육주사(intramuscular injection)로 투여하는 것이 충분하다. 현재까지 AAG 환자를 대상으로 한 경구제제(oral) 또는 설하제제(sublingual formulations) 의 효과를 평가한 연구는 없다 [1, 118].
철분(iron)의 경우, 경구제(oral) 또는 비경구제(parenteral) 사용에 대한 AAG 환자 대상의 임상시험은 없다. 따라서, 일반적인 철결핍성 빈혈(iron deficiency anaemia) 치료 지침을 따르는 것이 권장된다. 즉,
경증 빈혈(mild anaemia) 또는 내약성이 좋은 경우 → pH 비의존성 제형(pH-independent formulations, 예: liposomal formulations) 의 경구 철분 보충을 우선 고려하고,
중등도~중증 빈혈 또는 경구제 부작용이 있는 경우 → 정맥주사제(intravenous formulations) 를 사용하는 것이 바람직하다.
최근 연구에서는 위체부 위축성 위염(corpus atrophic gastritis) 환자에서 정맥주사용 ferric carboxymaltose 투여의 효과를 평가한 결과, 치료 12주 후 78.4%의 환자에서 철결핍성 빈혈이 회복되었고, 24개월까지 44.6%에서 그 효과가 유지되었다고 보고되어, 정맥 철분요법이 유효(valid)한 치료 접근법임이 확인되었다 [119].
엽산(folic acid)은 비타민 B₁₂와 항상 병용 보충해야 하며, 이는 장기간 엽산 고갈(folic acid depletion)이나 ‘folate trap’ 현상을 예방하기 위함이다. 또한 호모시스테인(homocysteine) 수치를 측정하면 MTHFR 유전자 변이로 인한 혼란요인(confounding factor) 을 배제하고, 비타민 B₁₂ 및 엽산 보충 효과를 모니터링하는 데 도움이 된다.
기타 비타민 B군(B vitamins) 보충이 AAG에서 필수적인지는 명확히 밝혀지지 않았지만, 혈전색전증(thromboembolic manifestations) 이 있는 환자에서는 개별적으로 보충을 고려해야 한다. 또한 비타민 D 역시 결핍 시 보충해야 하며, 일부 연구에서는 AAG 환자에서 비타민 D 흡수 장애(malabsorption) 가 발생할 수 있음이 보고되었다 [120].
3.4.8. AAG 환자의 소화불량(dyspepsia) 증상은 어떻게 치료해야 하는가?
Position statement
: 프로톤펌프억제제(PPI) 는 AAG 환자에서 일상적으로 사용해서는 안 된다. 이는 신경내분비종양(neuroendocrine neoplasms) 발생 위험을 높일 수 있기 때문이다. 다만, 위출혈(gastric bleeding) 이나 바렛식도(Barrett’s oesophagus) 와 같은 특정 상황에서는 예외적으로 사용할 수 있다.
현재까지 AAG 환자의 소화불량 치료에 있어 위산분비억제제(antisecretory agents), 위장운동촉진제(prokinetics) 또는 기타 약제의 효과와 안전성에 대한 근거는 부족하다. 현재까지 AAG 환자를 대상으로 소화불량(dyspepsia) 또는 위식도역류질환(GERD) 치료에 관한 PPI나 위장운동촉진제, 기타 약제의 안전성과 유효성을 평가한 임상시험은 없다. 실제로, PPI의 장기적·광범위한 사용은 권장되지 않는다. 그 이유는 PPI 사용이 제1형 위 신경내분비종양(t1-gNENs) 의 발생 위험을 높이고, 드물지만 위암(GC) 위험을 증가시킬 수 있음이 보고되었기 때문이다 [1, 114].
그러나, AAG의 초기 단계(early phase) 에는 일부 환자에서 잔존 위산 분비(residual acid secretion) 가 남아 있을 수 있으며, pH-임피던스 검사(pH-impedance monitoring) 에서 위식도역류질환(GERD) 이 확인되는 경우가 있다. 이러한 환자에서는 PPI 단기 요법(short course of PPIs) 을 통해 증상 완화 및 합병증(예: 역류성 식도염, 바렛식도) 을 예방하는 것이 도움이 될 수 있다.
반면, 질환의 후기 단계(late phase) 에 접어든 AAG 환자들은 비산성 역류(non-acid reflux) 에 의해 증상을 경험할 수 있으며, pH-임피던스 검사로 확인된다 [121]. 이 경우 제산제(antacids) 투여로 증상이 완화되는 경우도 있으나, 치료는 대체로 어렵고 반응이 불완전하다.
위장운동촉진제(prokinetics) — 예를 들어 돔페리돈(domperidone), 레보설피리드(levosulpiride), 생강 추출물(ginger extracts) 등은 기능성 소화불량(functional dyspepsia) 치료에 준하여 사용할 수 있으나, AAG 환자를 대상으로 한 연구는 현재까지 없다. 한편, 일부 연구에서는 zinc-L-carnosine 이 위 점막세포에서 항염증 작용(anti-inflammatory property) 을 나타낼 수 있음이 보고되었다 [38].
4. Conclusions
본 합의문(position paper)은 자가면역성 위축성 위염(AAG) 분야에서 오랜 경험과 전문성을 가진 여러 전문가들이 모여, 현재의 지식과 과학적 근거를 바탕으로 AAG와 관련된 임상적·학문적 주요 쟁점들에 대해 답을 도출하고자 한 공동의 노력(convergent expert effort) 을 반영한다.
이 문헌에서 제시된 핵심 요점(key points)은 다음과 같다. 비록 최근 몇 년간 AAG에 대한 학문적 관심과 연구 수가 지속적으로 증가하고 있으나, 과학적 근거(scientific evidence) 는 여전히 부족하며, 여러 중요한 쟁점들이 명확히 규명되지 못한 상태로 남아 있다.
특히, 다음과 같은 임상적으로 중대한 문제(clinically relevant issues) 들이 여전히 충분한 근거를 확보하지 못하고 있다.
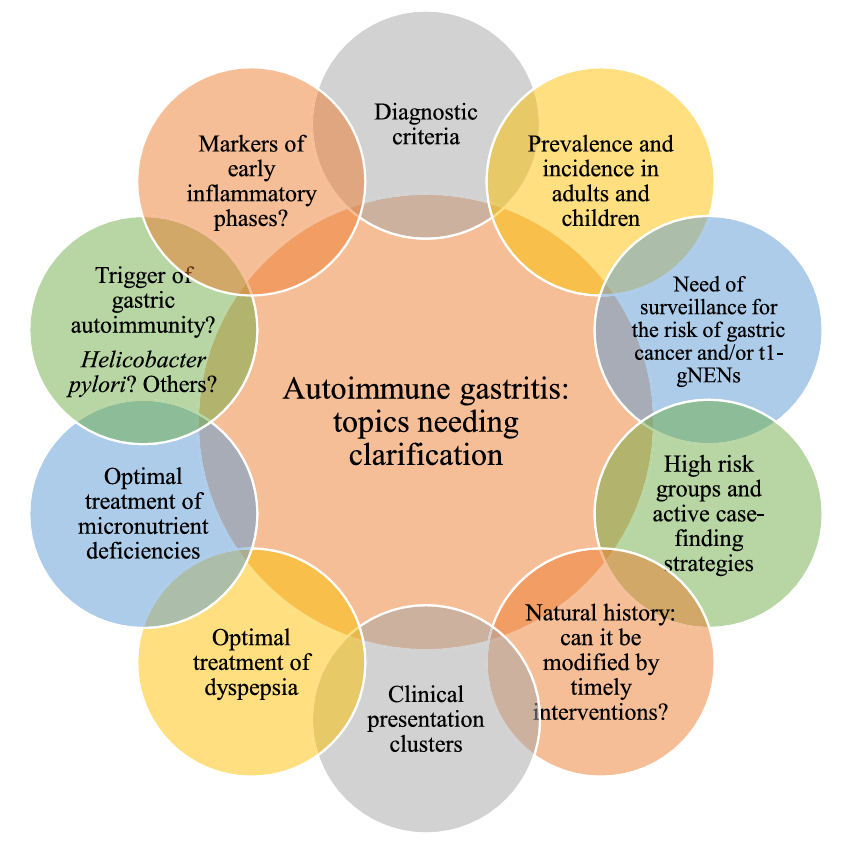
이들 주제는 대규모·고품질 연구(high-level evidence) 가 부족한 상태이며, 여전히 주로 단일 기관(single-centre)의 임상 경험과 관찰 결과에 의존하고 있다. 따라서, AAG 연구에는 여전히 많은 과제가 남아 있으며, 이 문헌에서 제시된 연구 의제(research agenda, Fig. 1) 가 그 필요성을 잘 보여준다.
Fig. 1. Agenda for future research in autoimmune gastritis.
국제적으로 통일된 진단 및 관리 기준(internationally shared criteria) 의 마련이 시급하다.
AAG에 대한 이해가 심화될수록,
정확하고 시의적절한 진단(correct and timely diagnosis) 이 가능해지고,
임상적 관리(clinical management) 와 환자의 삶의 질(quality of life) 이 향상되며,
이 과소평가 되어온 질환이 초래하는 경제적·사회적 부담(economic and social burden) 또한 감소할 것이다.
<Abstract>
Autoimmune atrophic gastritis (AAG) is a non-self-limiting immune-mediated disorder exerting growing interest. The main autoantigen, the beta subunit of the proton pump (H+, K+-ATPase), is localised on the oxyntic mucosa parietal cells, limiting the autoimmune inflammatory damage to this stomach compartment. Clinical manifestations of AAG may occur late, once corpus-fundus atrophy occurs, and are characterised by loss of gastric acidity, impaired iron and/or cobalamin malabsorption, and increased risk of gastric type 1 neuroendocrine neoplasms and possibly gastric adenocarcinoma. Many topics regarding epidemiology, clinical features, pathogenesis, diagnosis, and management remain to be clarified. AAG patients are frequently misdiagnosed or diagnosed with delay. AAG still represents a clinical challenge and a great opportunity for advancing our knowledge on gastrointestinal autoimmune diseases and gastric precancerous conditions. The timely and correct diagnosis of AAG patients is clinically relevant to avoid potentially harmful consequences due to micronutrient deficiencies and related anaemia and neoplastic complications. The current position paper addresses AAG in adults and reflects the views of the Autoimmune gastRitis Italian netwOrk Study grOup (ARIOSO) on its epidemiology, clinical features, pathogenesis, diagnosis, and management. Improving the understanding of AAG would facilitate timely and accurate diagnosis, enhance clinical management and patients' quality of life, and reduce the economic and social burden of this underrecognized condition.
Keywords: Atrophic gastritis; Autoimmune gastritis; Gastric cancer; Gastric neuroendocrine neoplasm; Helicobacter pylori; Iron deficiency anaemia; Natural history, pernicious anaemia; Position paper.
자가면역성 위축성 위염(Autoimmune atrophic gastritis, AAG)은 자가제한적(self-limiting) 으로 경과하지 않는 면역 매개성 질환(immune-mediated disorder) 으로, 최근 점차 많은 관심을 받고 있다. AAG의 주요 자가항원(autoantigen) 은 프로톤 펌프(proton pump, H⁺, K⁺-ATPase) 의 β-소단위체(beta subunit) 로, 이는 위저선 점막(oxyntic mucosa)의 벽세포(parietal cell) 에 위치한다. 따라서 자가면역성 염증 손상은 위의 이 부위로 국한된다.
🔹 임상적 특징 (Clinical manifestations)
AAG의 임상 증상은 대개 체부-저부 위축(corpus-fundus atrophy) 이 진행된 후 늦게(late) 나타나며, 다음과 같은 특징을 보인다.
위산 결핍(loss of gastric acidity)
철(iron) 및/또는 코발라민(cobalamin, 비타민 B₁₂) 흡수 장애
위 제1형 신경내분비종양(gastric type 1 neuroendocrine neoplasms) 발생 위험 증가
위선암(gastric adenocarcinoma) 위험 가능성
🔹 미해결 과제 (Unresolved issues)
AAG와 관련된 역학(epidemiology), 임상 양상(clinical features), 병태생리(pathogenesis), 진단(diagnosis), 치료 및 관리(management) 등 여러 측면에서 여전히 명확히 규명되지 않은 부분이 많다. AAG 환자들은 오진(misdiagnosis) 되거나 진단이 지연(delayed diagnosis) 되는 경우가 빈번하다.
🔹 임상적 중요성 (Clinical relevance)
AAG는 여전히 임상적 도전(clinical challenge) 이자, 위장관 자가면역질환(gastrointestinal autoimmune diseases) 및 위 전암성 병변(gastric precancerous conditions) 에 대한 지식을 확장할 수 있는 중요한 기회를 제공한다.
AAG 환자의 신속하고 정확한 진단(timely and correct diagnosis) 은 임상적으로 매우 중요하다. 이는 미량영양소 결핍(micronutrient deficiencies) 및 관련 빈혈(anemia), 그리고 신생물(neoplastic) 합병증과 같은 잠재적으로 유해한 결과를 예방하는 데 필수적이다.
🔹 ARIOSO 연구그룹의 입장 (ARIOSO Position Paper)
본 입장 논문(position paper) 은 성인 AAG 환자(adult AAG) 를 대상으로 하며, 자가면역성 위염 이탈리아 네트워크 연구그룹 (Autoimmune gastRitis Italian netwOrk Study grOup, ARIOSO) 의 역학, 임상 양상, 병태생리, 진단 및 관리에 대한 견해(views) 를 반영한다.
🔹 결론 (Conclusion)
AAG에 대한 이해를 향상시키는 것은
신속하고 정확한 진단(timely and accurate diagnosis) 을 촉진하고,
임상적 관리(clinical management) 와 환자의 삶의 질(quality of life) 을 개선하며,
이 과소인식된 질환(underrecognized condition) 으로 인한 경제적·사회적 부담(economic and social burden) 을 줄이는 데 기여할 것이다.
References
[1] Lenti MV, Rugge M, Lahner E, et al. Autoimmune gastritis. Nat Rev Dis Primers 2020;6:56.
[2] Lahner E, Zagari R, Zullo A, et al. Chronic atrophic gastritis: natural history, diagnosis and therapeutic management. A position paper by the Italian society of hospital gastroenterologists and digestive endoscopists [AIGO], the Italian Society of Digestive Endoscopy [SIED], the Italian Society of Gastroenterology [SIGE], and the Italian Society of Internal Medicine [SIMI]. Dig Liver Dis 2019;51:1621–32.
[3] Lenti M, Miceli E, Cococcia S, et al. Determinants of diagnostic delay in autoimmune atrophic gastritis. Aliment Pharmacol Ther 2019;50:167–75. doi:10.1111/apt.15317.
[4] Gattrell W, Logullo P, van Zuuren E, et al. ACCORD (ACcurate COnsensus Reporting Document): a reporting guideline for consensus methods in biomedicine developed via a modified Delphi. PLoS Med 2024;21:e1004326.
[5] Strickland R, Mackay I. A reappraisal of the nature and significance of chronic atrophic gastritis. Am J Dig Dis 1973;18:426–40. doi:10.1007/BF01071995.
[6] Dixon M, Genta R, Yardley J, et al. Classification and grading of gastritis. The updated Sydney System. International Workshop on the Histopathology of Gastritis, Houston 1994. Am J Surg Pathol 1996;20:1161–81.
[7] Rugge M, Genta R, Malfertheiner P, et al. RE.GA.IN; RE GA IN. RE.GA.IN.: the real-world Gastritis Initiative-updating the updates. Gut 2024;73:407–41.
[8] Carmel R. Prevalence of undiagnosed pernicious anemia in the elderly. Arch Intern Med 1996;156:1097–100.
[9] Rustgi S, Bijlani P, Shah S. Autoimmune gastritis, with or without pernicious anemia: epidemiology, risk factors, and clinical management. Ther Adv Gastroenterol 2021;14:17562848211038771.
[10] Massironi S, Zilli A, Elvevi A, et al. The changing face of chronic autoimmune atrophic gastritis: an updated comprehensive perspective. Autoimmun Rev 2019;18:215–22. doi:10.1016/j.autrev.2018.08.011.
[11] Li M, Huang Y, Liang X, Lu H. Prevalence of autoimmune gastritis worldwide: a systematic review and meta-analysis. Helicobacter 2025;30(4):e70065. doi:10.1111/hel.70065.
[12] Miceli E, Lenti M, Padula D, et al. Common features of patients with autoimmune atrophic gastritis. Clin Gastroenterol Hepatol 2012;10:812–14.
[13] Lahner E, Dilaghi E, Cingolani S, et al. Gender-sex differences in autoimmune atrophic gastritis. Transl Res 2022;248:1–10.
[14] Lenti M, Miceli E, Lahner E, et al. Distinguishing features of autoimmune gastritis depending on previous Helicobacter pylori infection or positivity to anti-parietal cell antibodies: results from the autoimmune gastRitis Italian netwOrk study grOup (ARIOSO). Am J Gastroenterol 2024;119:2408–17.
[15] Carabotti M, Lahner E, Esposito G, et al. Upper gastrointestinal symptoms in autoimmune gastritis: a cross-sectional study. Medicine 2017;96:e5784.
[16] Song H, Held M, Sandin S, et al. Increase in the prevalence of atrophic gastritis among adults age 35 to 44 years old in Northern Sweden between 1990 and 2009. Clin Gastroenterol Hepatol 2015;13:1592–600.
[17] Kalkan Ç, Soykan I. Polyautoimmunity in autoimmune gastritis. Eur J Intern Med 2016;31:79–83.
[18] Kotera T, Ayaki M, Sumi N, et al. Characteristic endoscopic findings in early-stage autoimmune gastritis. Endosc Int Open 2024;12:E332–8.
[19] Chen Y, Ji X, Zhao W, et al. A real-world study on the characteristics of autoimmune gastritis: a single-center retrospective cohort in China. Clin Res Hepatol Gastroenterol 2025;49:102556.
[20] Wang X, Lu C, Ding Y, et al. A retrospective study on clinical features of autoimmune gastritis: impact of age, sex, and autoimmune thyroid disease in China. Gut Liver 2025 [Epub ahead of print]. doi:10.5009/gnl240448.
[21] Azzouz Y, Abidi S, Chbicheb S. Retrospective cross-sectional study of 34 cases of pernicious anemia at Mohammed V Military Training Hospital, Morocco. Pan Afr Med J 2023;45:79.
[22] Doh K, Thiam I, Halim A, et al. Pathological overview of chronic gastritis in Senegal: results of upper gastrointestinal tract endoscopies. Med Sante Trop 2017;27:439–42 English.
[23] Gonzalez A, Latorre G, Paredes L, et al. Mucocutaneous manifestations in autoimmune gastritis: a prospective case-control study. Am J Gastroenterol 2021;116:2374–84.
[24] Lenti M, Miceli E, Joudaki S, et al. Impact of an active case-finding strategy in autoimmune gastritis. Eur J Intern Med 2024;130:179–81.
[25] Toh B, van Driel I, Gleeson P. Pernicious anemia. N Engl J Med 1997;337:1441–8.
[26] Green R, Allen L, Bjørke-Monsen A, et al. Vitamin B12 deficiency. Nat Rev Dis Primers 2017;3:17040.
[27] Dottori L, Pivetta G, Annibale B, et al. Update on serum biomarkers in autoimmune atrophic gastritis. Clin Chem 2023 Oct 3;69(10):1114–31.
[28] Miceli E, Vanoli A, Lenti M, et al. Natural history of autoimmune atrophic gastritis: a prospective, single centre, long-term experience. Aliment Pharmacol Ther 2019;50:1172–80.
[29] Miceli E, Lenti M, Gentile A, et al. Long-term natural history of autoimmune gastritis: results from a prospective monocentric series. Am J Gastroenterol 2024;119:837–45.
[30] Dilaghi E, Dottori L, Pivetta G, et al. Incidence and predictors of gastric neoplastic lesions in corpus-restricted atrophic gastritis: a single-center cohort study. Am J Gastroenterol 2023;118:2157–65.
[31] Rugge M, Bricca L, Guzzinati S, et al. Autoimmune gastritis: long-term natural history in naïve Helicobacter pylori-negative patients. Gut 2023;72:30–8.
[32] Lenti M, Miceli E, Vanoli A, et al. Time course and risk factors of evolution from potential to overt autoimmune gastritis. Dig Liver Dis 2022;54:642– 644.
[33] Lenti M, Broglio G, Di Sabatino A. Unravelling the risk of developing gastric cancer in autoimmune gastritis. Gut 2023;72:1429–30.
[34] Lahner E, Dilaghi E, Dottori L, et al. Not all that is corpus restricted is necessarily autoimmune. Gut 2023 Nov 24;72(12):2384–5.
[35] Hoft S, Brennan M, Carrero J, et al. Unveiling cancer-related metaplastic cells in both Helicobacter pylori infection and autoimmune gastritis. Gastroenterology 2025;168:53–67.
[36] D’Elios M, Bergman M, Azzurri A, et al. H(+),K(+)-atpase (proton pump) is the target autoantigen of Th1-type cytotoxic T cells in autoimmune gastritis. Gastroenterology Feb 2001;120(2):377–86.
[37] Della Bella C, Antico A, Panozzo M, et al. Gastric Th17 cells specific for H+/K+-ATPase and serum IL-17 signature in Gastric autoimmunity. Front Immunol 2022 Jul 11;13:952674.
[38] Lenti M, Facciotti F, Miceli E, et al. Mucosal overexpression of thymic stromal lymphopoietin and proinflammatory cytokines in patients with autoimmune atrophic gastritis. Clin Transl Gastroenterol 2022;13(7):e00510 Epub 2022 Jun 13. doi:10.14309/ctg.0000000000000510.
[39] Lenti M, Vanoli A, Miceli E, et al. Increase of deep intraepithelial lymphocytes in the oxyntic mucosa of patients with potential and overt autoimmune gastritis. Front Immunol 2022;13:866167 Published 2022 May 4. doi:10.3389/ fimmu.2022.866167.
[40] Amedei A, Bergman M, Appelmelk B, et al. Molecular mimicry between Helicobacter pylori antigens and H+, K+ –adenosine triphosphatase in human gastric autoimmunity. J Exp Med 2003 Oct 20;198(8):1147–56.
[41] D’Elios M, Appelmelk B, Amedei A, et al. Gastric autoimmunity: the role of Helicobacter pylori and molecular mimicry. Trends Mol Med Jul 2004;10(7):316–23.
[42] Appelmelk B, Faller G, Claeys D, et al. Bugs on trial: the case of Helicobacter pylori and autoimmunity. Immunol Today Jul 1998;19(7):296–9.
[43] D’Elios M, Bergman M, Amedei A, et al. Helicobacter pylori and gastric autoimmunity. Microbes Infect Dec 2004;6(15):1395–401.
[44] Bergman M, Vandenbroucke-Grauls C, et al. The story so far: helicobacter pylori and gastric autoimmunity. Int Rev Immunol 2005;24(1–2):63–91 Jan-Apr.
[45] Lahner E, Spoletini M, Buzzetti R, et al. HLA-DRB1×03 and DRB1×04 are associated with atrophic gastritis in an Italian population. Dig Liver Dis 2010;42(12):854–9.
[46] Oksanen A, Haimila K, Rautelin H, et al. Immunogenetic characteristics of patients with autoimmune gastritis. World J Gastroenterol 2010; 16(3):354–8.
[47] Lahner E, Gentile G, Purchiaroni F, et al. Single nucleotide polymorphisms related to vitamin B12 serum levels in autoimmune gastritis patients with or without pernicious anaemia. Dig Liver Dis 2015;47(4):285–90.
[48] Lenti M, Cococcia S, Miceli E, et al. Red flags for the diagnosis of autoimmune gastritis. Clin Res Hepatol Gastroenterol Jan 2022;46(1):101780.
[49] Castellana C, Eusebi L, Dajti E, et al. Autoimmune Atrophic Gastritis: a clinical review. Cancers (Basel) 28 Mar 2024;16(7).
[50] Prinz N, Tittel S, Bachran R, et al. Characteristics of patients with type 1 diabetes and additional autoimmune disease in the DPV registry. J Clin Endocrinol Metab 18 Aug 2021;106(9):e3381-e89.
[51] Boutzios G, Koukoulioti E, Goules A, et al. Hashimoto thyroiditis, anti-parietal cell antibodies: associations with autoimmune diseases and malignancies. Front Endocrinol (Lausanne) 2022;13:860880.
[52] Bjørklund G, Pivin M, Hangan T, et al. Autoimmune polyendocrine syndrome type 1: clinical manifestations, pathogenetic features, and management approach. Autoimmun Rev Aug 2022;21(8):103135.
[53] Singh S, Chakole S, Agrawal S, et al. A comprehensive review of upper gastrointestinal symptom management in autoimmune gastritis: current insights and future directions. Cureus Aug 2023;15(8):e43418.
[54] Miceli E, Di Stefano M, Lenti M, et al. Pregnancy-related complications in autoimmune atrophic gastritis: a monocentric experience. Dig Liver Dis Jan 2023;55(1):146–8.
[55] Bakulina N, Tikhonov S, Malkov V, et al. Noninvasive screening of autoimmune atrophic gastritis in asymptomatic subjects by serological biomarker test (GastroPanel(®)). Anticancer Res Mar 2022;42(3):1517–26.
[56] Lukens M, Koelman C, Curvers J, et al. Comparison of different immunoassays for the detection of antibodies against intrinsic factor and parietal cells. J Immunol Methods 2020;487:112867.
[57] Lahner E, Norman G, Severi C, et al. Reassessment of intrinsic factor and parietal cell autoantibodies in atrophic gastritis with respect to cobalamin deficiency. Am J Gastroenterol 2009;104:2071–9.
[58] Lahner E, Brigatti C, Marzinotto I, et al. Luminescent immunoprecipitation system (LIPS) for detection of autoantibodies against ATP4A and ATP4B subunits of gastric proton pump H+, K+-ATPase in atrophic body gastritis patients. Clin Trans Gastroenterol 2017;8:e215.
[59] Zhang Y, Weck M, Schottker B, et al. Gastric parietal cell antibodies, Helicobacter pylori infection, and chronic atrophic gastritis: evidence from a large population-based study in Germany. Cancer Epidemiol Biomark Prev 2013;22:821–6.
[60] Rusak E, Chobot A, Krzywicka A, et al. Anti-parietal cell antibodies - diagnostic significance. Adv Med Sci 2016;61:175–9.
[61] Bizzaro N, Antico A. Diagnosis and classification of pernicious anemia. Autoimmun Rev 2014;13:565–8.
[62] Marzinotto I, Dottori L, Baldaro F, et al. Intrinsic factor autoantibodies by luminescent immuno-precipitation system in patients with corpus atrophic gastritis. J Transl Autoimmun 2021;4:100131.
[63] Rehfeld J, Bardram L, Hilsted L, et al. Pitfalls in diagnostic gastrin measurements. Clin Chem 2012;58:831–6.
[64] Syrjänen K, Eskelinen M, Peetsalu A, et al. Gastropanel® biomarker assay: the most comprehensive test for Helicobacter pylori infection and its clinical sequelae. A critical review. Anticancer Res 2019;39:1091–104.
[65] Hattori Y, Tashiro H, Kawamoto T, et al. Sensitivity and specificity of mass screening for gastric cancer using the measurement of serum pepsinogens. Jpn J Cancer Res 1995;86:1210–15.
[66] Huang Y, Yu J, Kang W, et al. Significance of serum pepsinogens as a biomarker for gastric cancer and atrophic gastritis screening: a systematic review and metaanalysis. PLoS ONE 2015;10:e0142080.
[67] Zagari R, Rabitti S, Greenwood D, et al. Systematic review with metaanalysis: diagnostic performance of the combination of pepsinogen, gastrin-17 and anti-Helicobacter pylori antibodies serum assays for the diagnosis of atrophic gastritis. Aliment Pharmacol Ther 2017;46:657–67.
[68] Kishikawa H, Nakamura K, Ojiro K, et al. Relevance of pepsinogen, gastrin, and endoscopic atrophy in the diagnosis of autoimmune gastritis. Sci Rep 2022;12:4202.
[69] Antico A, Tampoia M, Villalta D, et al. Clinical usefulness of the serological gastric biopsy for the diagnosis of chronic autoimmune gastritis. Clin Dev Immunol 2012;2012:520970.
[70] Lahner E, Marzinotto I, Lampasona V, et al. Autoantibodies toward ATP4A and ATP4B subunits of gastric proton pump H+, K+- ATPase are reliable serological pre-endoscopic markers of corpus atrophic gastritis. Clin Transl Gastroenterol 2020;11:e00240.
[71] Krike P, Shums Z, Polaka I, et al. The diagnostic value of anti-parietal cell and intrinsic factor antibodies, pepsinogens, and gastrin-17 in corpus-restricted atrophic gastritis. Diagn (Basel) 2022;12:2784.
[72] Chapelle N, Martin J, Osmola M, et al. Serum pepsinogens can help to discriminate between H. pylori-induced and auto-immune atrophic gastritis: results from a prospective multicenter study. Dig Liver Dis 2023;55:1345–51.
[73] Pimentel-Nunes P, Libânio D, Marcos-Pinto R, et al. Management of epithelial precancerous conditions and lesions in the stomach (MAPS II): european Society of Gastrointestinal Endoscopy (ESGE), European Helicobacter and Microbiota Study Group (EHMSG), European Society of Pathology (ESP), and Sociedade Portuguesa de Endoscopia Digestiva (SPED) guideline update 2019. Endoscopy 2019;51:365–88 39.
[74] Dinis-Ribeiro M, Libânio D, Uchima H, et al. Management of epithelial precancerous conditions and early neoplasia of the stomach (MAPS III): european Society of Gastrointestinal Endoscopy (ESGE), European Helicobacter and Microbiota Study Group (EHMSG) and European Society of Pathology (ESP) Guideline update 2025. Endoscopy 2025;57(5):504–54. doi:10.1055/ a-2529-5025.
[75] Shah S, Piazuelo M, Kuipers E, et al. AGA Clinical Practice update on the diagnosis and management of atrophic gastritis: expert review. Gastroenterology 2021;161:1325–1332.e7.
[76] Banks M, Graham D, Jansen M, et al. British Society of Gastroenterology guidelines on the diagnosis and management of patients at risk of gastric adenocarcinoma. Gut 2019;68:1545–75.
[77] Morgan D, Corral J, Li D, et al. ACG Clinical guideline: diagnosis and management of gastric premalignant conditions. Am J Gastroenterol 2025;120:709–37.
[78] Massironi S, Gallo C, Lahner E, et al. Occurrence and characteristics of endoscopic gastric polyps in patients with autoimmune gastritis (AGAPE study): a multicentric cross-sectional study. Dig Liver Dis 2025;57:198–205.
[79] Dilaghi E, Esposito G, Pivetta G, et al. Endoscopic diagnosis of gastric intestinal metaplasia in patients with autoimmune gastritis using narrow-band imaging: does pseudopyloric metaplasia muddy the waters? Endosc Int Open Apr 2022;10:E434-e40.
[80] Kamada T, Watanabe H, Furuta T, et al. Diagnostic criteria and endoscopic and histological findings of autoimmune gastritis in Japan. J Gastroenterol 2023;58:185–95.
[81] Chen S, Xu L, Yan L, et al. A novel endoscopic artificial intelligence system to assist in the diagnosis of autoimmune gastritis: a multicenter study. Endoscopy 2025;57:299–309.
[82] Dottori L, Palumbo C, Dilaghi E, et al. Antral mucosa healing at long-term follow-up in patients with corpus atrophic gastritis and concomitant antral gastritis may mimic autoimmune gastritis. Dig Liver Dis 2025;57:333–9.
[83] Correa P. Human gastric carcinogenesis: a multistep and multifactorial process: first American cancer society award lecture on cancer epidemiology and prevention. Cancer Res 1992;52:6735–40 PMID: 1458460.
[84] Hoft S, Noto C, DiPaolo R. Two distinct etiologies of gastric cancer: infection and autoimmunity. Front Cell Dev Biol 2021;9:752346. doi:10.3389/fcell.2021. 752346.
[85] Lahner E, Vaira D, Figura N, et al. Role of noninvasive tests (C-urea breath test and stool antigen test) as additional tools in diagnosis of Helicobacter pylori infection in patients with atrophic body gastritis. Helicobacter 2004;9:436–42.
[86] Aydin O, Egilmez R, Karabacak T, et al. Interobserver variation in histopathological assessment of Helicobacter pylori gastritis. World J Gastroenterol 2003;9:2232–5.
[87] Chen X, van der Hulst R, Bruno M, et al. Interobserver variation in the histopathological scoring of Helicobacter pylori related gastritis. J Clin Pathol 1999;52:612–15.
[88] Rugge M, Fassan M, Pizzi M, et al. Operative link for gastritis assessment vs operative link on intestinal metaplasia assessment. World J Gastroenterol 2011;17:4596–601.
[89] Conti L, Lenti M, Di Sabatino A, et al. Seronegative autoimmune atrophic gastritis is more common in elderly patients. Dig Liver Dis 2020;52:1310–14.
[90] Lenti M, Miceli E, Padula D, et al. The challenging diagnosis of autoimmune atrophic gastritis. Scand J Gastroenterol 2017;52:471–2.
[91] Bettington M, Brown I. Autoimmune gastritis: novel clues to histological diagnosis. Pathology 2013;45:145–9.
[92] Lenti M, Joudaki S, Miceli E, Lahner E, Massironi S, Votto M, Licari A, Caimmi S, Bramuzzo M, Di Leo G, Crocco M, Malerba F, Francavilla R, Lionetti P, Alvisi P, Panceri R, Zuin G, Villanacci V, Barp J, Fuoti M, Oliva S, Aloi M, Distante M, Assa A, Dotan Y, Amato A, Romano C, Staiano A, Miele E, Strisciuglio C, Fioretti M, Zingone F, Cananzi M, De Giacomo C, Di Nardo G, Quadrelli A, Vanoli A, Paulli M, Annibale B, Marseglia G, Di Sabatino A. Pediatric autoimmune gastritis: an international, multicentric study. J Pediatr Gastroenterol Nutr 12 Aug 2025 Epub ahead of print. PMID: 40798919. doi:10.1002/jpn3.70187.
[93] Miceli E, Padula D, Lenti M, et al. A laboratory score in the diagnosis of autoimmune atrophic gastritis: a prospective study. J Clin Gastroenterol 2015;49:e1–5.
[94] Malfertheiner P, Camargo M, El-Omar E, et al. Helicobacter pylori infection. Nat Rev Dis Primers 2023;9:19.
[95] Forman D, Newell D, Fullerton F, et al. Association between infection with Helicobacter pylori and risk of gastric cancer: evidence from a prospective investigation. BMJ 1991;302:1302–5.
[96] Ford A, Yuan Y, Moayyedi P. Helicobacter pylori eradication therapy to prevent gastric cancer: systematic review and meta-analysis. Gut 2020;69:2113–21.
[97] Presotto F, Sabini B, Cecchetto A, et al. Helicobacter pylori infection and gastric autoimmune diseases: is there a link? Helicobacter 2003;8:578–84.
[98] Rugge M, Genta R, Fassan M, et al. OLGA gastritis staging for the prediction of gastric cancer risk: a long-term follow-up study of 7436 patients. Am J Gastroenterol 2018;113:1621–8.
[99] Capelle L, de Vries A, Haringsma J, et al. The staging of gastritis with the OLGA system by using intestinal metaplasia as an accurate alternative for atrophic gastritis. Gastrointest Endosc 2010;71:1150–8.
[100] Graham D, Rugge M, Genta R. Diagnosis: gastric intestinal metaplasia - what to do next? Curr Opin Gastroenterol 2019;35:535–43.
[101] Lenti M, Lahner E, Bergamaschi G, et al. Cell blood count alterations and patterns of anaemia in autoimmune atrophic gastritis at diagnosis: a multicentre study. J Clin Med 2019;8:1992.
[102] Doorakkers E, Lagergren J, Engstrand L, et al. Helicobacter pylori eradication treatment and the risk of gastric adenocarcinoma in a western population. Gut 2018;67:2092–6.
[103] Rokkas T, Pistiolas D, Sechopoulos P, et al. The long-term impact of Helicobacter pylori eradication on gastric histology: a systematic review and metaanalysis. Helicobacter 2007;12:32–8 Suppl 2.
[104] Zhu F, Zhang X, Li P, et al. Effect of Helicobacter pylori eradication on gastric precancerous lesions: a systematic review and metaanalysis. Helicobacter 2023;28:e13013. doi:10.1111/hel.13013.
[105] Liang Y, Yang Y, Nong R, et al. Do atrophic gastritis and intestinal metaplasia reverse after Helicobacter pylori eradication? Helicobacter 2024;29:e13042. doi:10.1111/hel.13042.
[106] Annibale B, Azzoni C, Corleto V, et al. Atrophic body gastritis patients with enterochromaffin-like cell dysplasia are at increased risk for the development of type I gastric carcinoid. Eur J Gastroenterol Hepatol 2001;13:1449–56.
[107] Vanoli A, La Rosa S, Luinetti O, et al. Histologic changes in type A chronic atrophic gastritis indicating increased risk of neuroendocrine tumor development: the predictive role of dysplastic and severely hyperplastic enterochromaffin-like cell lesions. Hum Pathol 2013;44:1827–37.
[108] Annibale B, Aprile M, D’Ambra G, et al. Cure of Helicobacter pylori infection in atrophic body gastritis patients does not improve mucosal atrophy but reduces hypergastrinemia and its related effects on body ECL-cell hyperplasia. Aliment Pharmacol Ther 2000;14:625–34.
[109] Malfertheiner P, Megraud F, Rokkas T, et al. Management of Helicobacter pylori infection: the Maastricht VI/Florence consensus report. Gut Epub ahead print August 2022. doi:10.1136/gutjnl-2022-327745.
[110] De Francesco V, Bellesia A, Ridola L, et al. Firstline therapies for Helicobacter pylori eradication: a ritical reappraisal of updated guidelines. Ann Gastroenterol 2017;30:373–9.
[111] Chey W, Leontiadis G, Howden C, et al. ACG clinical guideline: treatment of Helicobacter pylori infection. Am J Gastroenterol 2017;112:212–38.
[112] Zagari R, Dajti E, Cominardi A, et al. Standard bismuth quadruple therapy versus concomitant therapy for the first-line treatment of Helicobacter pylori infection: a systematic review and metaanalysis of randomised controlled trials. J Clin Med 2023;12:3258.
[113] Nyssen O, Bordin D, Tepes B, et al. European Registry on Helicobacter pylori Management (Hp-EuReg): patterns and trends in first-line empirical eradication prescription and outcomes of 5 years and 21 33 patients. Gut 2021;70:40–54.
[114] Lahner E, Carabotti M, Annibale B. Treatment of Helicobacter pylori infection in atrophic gastritis. World J Gastroenterol 2018;24:2373–80.
[115] Dilaghi E, Mosciatti L, Dottori L, et al. Therapeutic regimens against Helicobacter pylori infection without proton pump inhibitors in patients with corpus atrophic gastritis: a real-life single-centre longitudinal observational study. Ther Adv Gastroenterol 2025;18:17562848241308035 Published 2025 Jan 14. doi:10.1177/17562848241308035.
[116] Lenti M, Hammer H, Tacheci I, et al. European consensus on malabsorptionUEG & SIGE, LGA, SPG, SRGH, CGS, ESPCG, EAGEN, ESPEN, and ESPGHAN. Part 1: definitions, clinical phenotypes, and diagnostic testing for malabsorption. United Eur Gastroenterol J 2025 Mar 25 Epub ahead of print. PMID: 40129317. doi:10.1002/ueg2.70012.
[117] Lenti M, Hammer H, Tacheci I, et al. European consensus on MalabsorptionUEG & SIGE, LGA, SPG, SRGH, CGS, ESPCG, EAGEN, ESPEN, and ESPGHAN: part 2: screening, special populations, nutritional goals, supportive care, primary care perspective. United Eur Gastroenterol J 2025 Mar 15 Epub ahead of print. PMID: 40088199. doi:10.1002/ueg2.70011.
[118] Esposito G, Dottori L, Pivetta G, et al. Pernicious anemia: the hematological presentation of a multifaceted disorder caused by cobalamin deficiency. Nutrients 2022;14:1672.
[119] Dottori L, Corleone Tsar’kov D, Dilaghi E, et al. Efficacy and safety of intravenous ferric carboxymaltose treatment of iron deficiency anaemia in patients with Corpus atrophic gastritis: a retrospective study. Nutrients 2023;15:4199.
[120] Massironi S, Cavalcoli F, Zilli A. Relevance of vitamin D deficiency in patients with chronic autoimmune atrophic gastritis: a prospective study. BMC Gastroenterol 2018;18:172.
[121] Carabotti M, Esposito G, Lahner E, et al. Gastroesophageal reflux symptoms and microscopic esophagitis in a cohort of consecutive patients affected by atrophic body gastritis: a pilot study. Scand J Gastroenterol 2019;54:35–40.


Lahner E, Lenti MV, Massironi S, Zingone F, Miceli E, Della Bella C, Facciotti F, Pelizzaro F, Annibale B, D'Elios MM, Sabatino AD.
Dig Liver Dis. 2026 Jan;58(1):38-50. doi: 10.1016/j.dld.2025.10.015.
1. Introduction
자가면역성 위축성 위염(AAG)은 자가면역 기전으로 발생하는 non-self-limiting 질환으로, 최근 들어 의학 및 과학계에서 점점 더 주목받고 있다. 주요 자가항원은 프로톤 펌프(H⁺, K⁺-ATPase)의 β 아단위로 밝혀졌으며, 이는 위저선(oxyntic mucosa)의 벽세포(parietal cell)에 국한되어 존재하기 때문에, 자가면역성 염증손상 또한 이 부위에 한정되어 유문부(antrum)는 보존된다.
AAG의 임상 증상은 대개 비교적 후기 단계에 나타나며, 이는 위저부-체부 점막의 위축이 진행되어 위산 분비의 상실(hypo- 또는 achlorhydria)이 일어나고, pseudopyloric metaplasia나 intestinal metaplasia가 동반될 때 나타난다. 임상적으로는 위산 분비 저하, 철분 및/또는 코발라민(cobalamin) 흡수장애, 소화불량, 그리고 제1형 위신경내분비종양(type 1 gastric neuroendocrine neoplasm, t1-gNEN) 및 위암(gastric cancer, GC) 발생 위험의 증가가 특징적이다. 다만, 후자의 연관성은 여전히 논란의 여지가 있다.
다른 자가면역질환들과 마찬가지로, AAG는 종종 자가면역성 갑상선질환(autoimmune thyroid disease)과 함께 발생하며, 제1형 당뇨병(type 1 diabetes), 애디슨병(Addison’s disease) 등과도 동반될 수 있다 [1,2].
최근 몇 년간 AAG에 대한 연구가 활발히 이루어졌음에도 불구하고, 역학, 임상 양상, 병태생리, 진단, 치료 및 관리에 관한 여러 주제는 여전히 명확히 규명되지 않았다. 많은 환자들이 오진(misdiagnosis)되거나 진단이 지연(delay in diagnosis)되는 경우가 많으며 [3], 이는 미량영양소 결핍 및 이로 인한 빈혈, 나아가 신생물(neoplasm) 합병증 등 잠재적으로 해로운 결과를 초래할 수 있다. 따라서 AAG 환자의 조기이자 정확한 진단은 임상적으로 매우 중요하며, 이는 환자의 삶의 질 향상뿐만 아니라 사회적·경제적 부담을 줄이는 데에도 기여할 수 있다.
본 입장문(position paper)은 성인에서의 자가면역성 위축성 위염(AAG)에 대한 최신 지견을 다루며, Autoimmune gastRitis Italian netwOrk Study grOup (ARIOSO)의 견해를 반영하고 있다.
2. Material and methods
본 입장문(position paper)의 참여자들은 자가면역성 위축성 위염(AAG)과 관련된 주요 주제들 가운데, 현재의 임상진료 및 논란이 있는 쟁점들에 초점을 맞추어 일련의 진술문(statements)을 작성하고 제안하였다. 표 1에는 이번 AAG 입장문에 참여한 연구자들의 주요 특성이 요약되어 있다.
각 주제별로 2~3명의 전문가가 포함된 작업 그룹(working party) 이 구성되었으며, AAG와 관련된 문헌을 대상으로 PubMed, EMBASE, Scopus, Cochrane Library, Google Scholar 등 주요 전자 데이터베이스를 이용하여 2025년 3월까지 발표된 연구를 포괄적으로 검색하였다. 검색 주제에는 유병률(prevalence)과 발생률(incidence), 임상양상 및 증상(clinical presentation and symptoms), 진단(diagnosis), 치료(treatment), 추적관찰(follow-up) 이 포함되었다. 검색 전략은 MeSH 용어인 “atrophic gastritis”, “autoimmune gastritis”, “Helicobacter pylori”, “gastric cancer”, “gastric dysplasia”, “gastric intestinal metaplasia”, “gastric neuroendocrine tumours”, “pernicious anaemia”를 사용하였으며, 이들을 다양한 조합으로 불린 연산자(Boolean operators) 인 AND, OR, NOT을 활용하여 검색하였다. 문헌 검색은 영어로 작성된 논문으로 제한하였으며, 편집자에게 보내는 서신(letters to the editor), 증례보고(case reports), 학회 초록(meeting abstracts) 등은 제외하였다.
진술문 개발과 확정을 위해 수정 델파이(modified Delphi) 방법이 사용되었다. 각 진술문은 두 차례의 이메일 라운드를 통해 참여자들 간에 공유되었으며, 이 과정에서 과학적·임상적 타당성, 명확성과 가독성 향상, 중복 제거 등을 논의하였다. 모든 참여자들의 전원 합의(full agreement) 가 이루어질 때까지 진술문은 반복적으로 수정되었고, 이후 최종 초안이 승인되었다 [4].
표 2는 포함된 진술문의 개요를 보여준다. 본 입장문의 구성은 각 진술문(statement), 근거 수준(evidence level, EL), 권고 등급(recommendation grade, RG), 그리고 근거 요약(summary of evidence) 으로 이루어져 있다. 이 문서는 ACCORD (ACcurate COnsensus Reporting Document) 가이드라인 [4]에 따라 작성되었다. 다만, 각 진술문에 대한 공식적인 등급화(formal grading) 는 생략되었다. 그 이유는, 첫째 본 문서가 입장문(position paper) 이며, 둘째 대부분의 질문들이 PICO(Problem, Intervention, Comparison, Outcome) 틀을 따르지 않고 AAG의 임상적 쟁점과 전반적 질문을 다루기 때문이다.
3. Statements
3.1. Epidemiological and clinical topics
3.1.1. 자가면역성 위축성 위염(AAG)은 희귀질환이거나 특정 지역에만 제한된 질환으로 보아야 하는가?
Position statement
: AAG는 희귀질환으로 간주되어서는 안 된다. 이 질환은 성별, 연령, 인종에 관계없이 전 인구집단에서 보고되었으며, 전 세계 추정 유병률은 약 3.8%로 보고된다.
AAG는 Addison에 의해 처음 기술된 이후, Helicobacter pylori (H. pylori) 의 발견으로 역학적 특성이 더욱 명확히 규명되었다. 이 발견을 통해 H. pylori 관련 위축성 위염과 자가면역성 위축성 위염(AAG) 이 구분될 수 있게 되었다 [1, 5–7]. 그 이전까지 대부분의 연구는 악성빈혈(pernicious anaemia, PA) 에만 초점을 맞추었으며, 이는 60세 이상 인구의 약 2%에서 유병률이 보고되었다 [8]. 조직학적으로 확진된 AAG의 전 세계 유병률은 연구에 따라 0.3–2.7% [9], 또는 0.5–4.5% [1,10] 로 추정되어 왔다. 또한, 최근 AAG의 역학에 관한 체계적 문헌고찰(systematic review) 에서는 전 세계 유병률이 약 3.8%로 보고되었으나, 포함된 연구들 간의 이질성이 매우 커서 일부는 혈청검사(serology) 만을 근거로 진단하여 실제보다 과대평가(overestimation) 되었을 가능성도 있다 [11]. 이 유병률 수치는 성별(여성에서 더 흔하며, 여성:남성 비는 약 2:1) [12,13], 연령(연령 증가에 따라 발생률 증가), 그리고 지리적 요인에 따라 달라질 수 있다 [1]. AAG의 역학을 보고한 대부분의 연구는 유럽(특히 이탈리아, 북유럽, 터키) 에서 수행되었으며 [1,10–17], 이로 인해 한동안 백인(Caucasian) 또는 터키계 인구에 주로 발생하는 질환으로 여겨졌다. 그러나 최근 수십 년간 일본 [18], 중국 [19,20], 아프리카 [21,22], 남아메리카 [23] 등 세계 여러 지역에서도 AAG 사례들이 보고되고 있다. 따라서 일부 연구가 부족한 지역(under-represented areas) 에서는 AAG의 실제 유병률이 과소평가(underestimated) 되었을 가능성이 높다. 한 이탈리아 연구에서는 비선택적 외래 환자군을 대상으로 혈청학적 선별검사(serological screening) 를 광범위하게 적용했을 때, AAG의 혈청학적 유병률은 10.6%, 조직학적으로 확진된 유병률은 4.3%로 보고되었다 [24].
3.1.2. 자가면역성 위축성 위염(AAG)은 악성빈혈(pernicious anaemia, PA)과 동일한 용어로 간주해야 하는가?
Position statement
: PA는 AAG의 동의어로 사용되어서는 안 된다.
PA는 AAG의 하나의 임상적 표현형(manifestation) 으로, 대개 질병의 후기 단계에서 나타나는 소견이다. PA는 오랫동안 자가면역성 위축성 위염(AAG) 환자를 지칭하는 용어로 혼용되어 왔다. 이는 비타민 B12(코발라민) 흡수 장애와 결핍으로 인해 발생하는 거대적아구성(megaloblastic), 대적혈구성 빈혈(macrocytic anaemia) 의 형태로 나타나며, 일부에서는 범혈구감소증(pancytopenia) 으로까지 진행하기도 한다 [25]. 이러한 형태의 빈혈은 오랫동안 AAG의 가장 대표적인 임상 양상으로 기술되어 왔으며 [1,8], 대개 진단 지연 없이 비교적 빠르게 AAG로 진단되는 경우가 많았다 [3]. 그러나 최근 들어 질환에 대한 이해와 진단기준이 발전함에 따라, 이 외에도 다양한 임상양상이 보고되고 있다(후술 참조). 따라서 전문가 합의에 따르면, 임상 스펙트럼이 훨씬 더 넓은 AAG를 단순히 PA와 동일시하는 것은 부적절하며, PA를 AAG의 동의어로 사용하는 것은 권장되지 않는다. 또한, 거대적아구성·대적혈구성 빈혈은 AAG 이외의 원인으로 인한 비타민 B12 결핍에서도 발생할 수 있다. 예를 들어, 식이 제한(dietary restriction), 위장관 수술 이력(previous gastrointestinal surgery), 헬리코박터 파일로리 감염(H. pylori infection) 등에서도 유사한 빈혈이 나타날 수 있다 [26].
3.1.3. 자가면역성 위축성 위염(AAG)은 임상적으로 ‘무증상 질환(clinically silent disease)’으로 간주되어야 하는가?
Position statement
: AAG는 위장관 증상이나 혈액학적 이상을 넘어서는 다양한 임상 양상을 보이는 질환이다. 진단 시점에서 최대 30%의 환자는 무증상(asymptomatic) 일 수 있다.
AAG의 임상 스펙트럼은 완전히 무증상인 상태에서부터 다음과 같은 다양한 임상 증상에 이르기까지 매우 광범위하다.
위장관 증상(Gastrointestinal symptoms): 소화불량(dyspepsia), 복통(abdominal pain), 체중감소(weight loss) 등
신경학적 이상(Neurological abnormalities): 기분 변화(mood alterations), 정신과적 증상(psychic manifestations), 감각이상(paraesthesia), 치매(dementia) 등이 있으며, 일부는 비가역적(irreversible) 일 수 있음
혈액학적 이상(Haematological alterations): 빈혈(anaemia, 비타민 B12 결핍성 또는 철결핍성), 범혈구감소증
생식 관련 이상(Fertility issues)
심혈관계 이상(Cardiovascular manifestations): 고호모시스테인혈증(hyperhomocysteinaemia)에 이차적으로 발생
기타 자가면역질환과의 연관성: 자가면역 다선증후군(autoimmune polyglandular syndromes), 자가면역성 갑상선질환(autoimmune thyroid disease) 등 [1,3,10–15,17,24].
현재까지의 연구에 따르면, AAG 환자의 약 30%까지는 뚜렷한 증상 없이 진단되거나 [12,15], 의료기관을 방문할 정도로 명확하지 않은 미묘한 임상 증상(nuanced manifestations) 만을 보일 수 있다. 일부 환자에서는 왜 특정 임상양상(예: PA)은 나타나지만 다른 양상(예: 신경학적 이상)은 나타나지 않는지 명확히 알려져 있지 않다. 이에 대해 유전적 요인(genetic factors) 이 AAG의 임상 표현형(clinical manifestation)에 영향을 미칠 수 있다는 가설이 제기되어 있다(3.2.3절 참조). 비타민 B12 결핍은 임상적으로 증상이 나타나기까지 수년에 걸쳐 서서히 진행되므로 [26], AAG 환자는 오랜 기간 동안 무증상 상태로 존재할 수 있다. 따라서 AAG 가족력이 있는 1차 친족(first-degree relatives) 이나 다른 자가면역질환을 가진 개인에 대해 혈청학적 선별검사(serological screening) 를 시행하면, 증상이 나타나기 전 무증상 단계에서 AAG를 조기 진단(early diagnosis) 할 수 있다 [24,27].
3.1.4. 자가면역성 위축성 위염(AAG)의 자연경과: 시간이 지나면서 어떤 변화가 일어나는가?
Position statement
: AAG는 점진적으로 악화되는 진행성 질환(progressively worsening condition) 으로, 거의 모든 경우에서 위축(gastric atrophy)이 경도에서 중등도, 중증 단계로 진행한다. AAG의 합병증으로는 위 신경내분비종양(gastric neuroendocrine neoplasms, gNENs) 이 잘 알려져 있으며, 환자의 약 10–15%에서 발생한다. 또한 위암(gastric cancer, GC) 도 드물지만 발생할 수 있다.
최근 수년간 AAG의 자연경과(natural history) 에 대한 몇몇 연구가 발표되었으며, 이들 연구의 중앙 추적관찰기간(median follow-up time) 은 약 10년 정도이며, 일부 연구에서는 최대 20년 이상 장기간 관찰된 환자들도 포함되었다 [28–32]. 이러한 연구들은 AAG가 시간이 지남에 따라 점진적으로 악화되는 질환임을 일관되게 보여주었다. 초기 단계의 AAG, 즉 위축이 없는 상태에서 벽세포 자가항체(parietal cell autoantibodies, PCA) 가 존재하는 경우를 잠재성 자가면역성 위염(potential autoimmune gastritis) 이라 한다. 이들은 시간이 지나면서 명확한 형태의 AAG(overt AAG) 로 발전할 위험이 있다.
관찰 연구에 따르면, 약 절반의 환자(약 50%)가 5년 내에 체부 위축(corpus atrophy) 으로 진행하며, 장기간 추적할 경우 약 75%까지 위축이 발생한다 [29,32]. 대부분의 경우, AAG 환자들은 경도의 위축에서 중증 위축으로 진행하지만 [29,30], 신생물 합병증(neoplastic complications) 으로 발전하는 경우는 소수(minority) 에 해당한다. 그 중 가장 흔한 것은 제1형 위 신경내분비종양(type 1 gNENs) [28–32]이며, 그 다음이 위암(GC) [30]이다.
AAG의 자연경과를 다룬 거의 모든 연구에서, t1-gNEN 발생 위험은 일관되게 보고되었으며, AAG 환자의 평생 유병률(lifetime risk) 은 약 10–15%로 추정된다 [28–32]. 반면, AAG 환자가 위암(GC) 발생 위험이 증가하는지 여부는 여전히 논란이 있다 [31,33,34]. 대부분의 연구들은 순수 AAG(pure AAG) 에서 위암 위험이 매우 낮거나 거의 없다고 보고하였으나 [28,29,31], 과거에 헬리코박터 파일로리 감염(H. pylori infection)의 병력이 있는 환자에서는 [29,34] 이 위험이 유의하게 증가할 수 있음이 제시되었다. 다만, AAG의 자연경과를 다룬 기존 연구들은 대부분 3차 의료기관(tertiary referral centre) 에서 수행된 것으로, 이들 기관에서는 내시경 감시(endoscopic surveillance) 가 매우 적극적으로 이루어지므로, 그 결과를 일반 인구집단에 그대로 적용하기는 어렵다.
병태생리학적 관점에서, 최근 연구에 따르면 AAG 환자의 위점막에서 H. pylori 위염과 유사하게 ANPEP/CD13을 발현하는 암 관련 화생세포(cancer-related metaplastic cells) 가 관찰되었다 [35]. 이 발견은 AAG가 일부 환자에서는 실제로 위암으로 진행할 수 있음을 시사하며, 이를 명확히 규명하기 위해서는 추가적인 전향적 연구(prospective studies) 가 필요하다.
3.2. Pathogenetic topics
3.2.1. 자가면역성 위축성 위염(AAG)의 주요 병인적 특징은 무엇인가?
Position statement
: AAG는 위저선(oxyntic mucosa)의 림프단핵세포(lymphomononuclear cell) 침윤 증가와 염증성 사이토카인(pro-inflammatory cytokine)의 과생산이 특징이다. 위축이 진행되기 전의 초기, 전(前)위축기(pre-atrophic phase) 에서는 위저선 점막 내상피 림프구침윤(intraepithelial lymphocytosis) 이 증가하는 것이 특징적이다.
AAG는 위체부(corpus)와 위저부(fundus)에 국한된 염증성 자가면역 질환으로, 위벽세포(parietal cell)의 파괴와 위저선 점막의 위축(atrophy) 을 특징으로 한다. 이로 인해 내인자(intrinsic factor) 결핍과 저산증 또는 무산증(hypo-/achlorhydria) 이 발생하며, 흔히 그레이브스병(Basedow–Graves’ disease), 하시모토 갑상선염(Hashimoto’s thyroiditis) 등 다른 자가면역질환과 동반된다. AAG의 병리학적 소견은 위 점막고유층(lamina propria)과 점막하층(submucosa) 에 존재하는 림프구 및 형질세포(plasma cell)의 침윤과, 위벽세포(parietal cell) 및 주세포(zyminogenic cell) 의 지속적인 파괴 과정으로 요약된다 [1,2]. AAG의 병인에서 핵심은 위벽세포의 H⁺,K⁺-ATPase 및 내인자(intrinsic factor)에 특이적인 T세포 반응과 이들을 표적으로 하는 자가항체(autoantibodies) 의 생성이다. 즉, H⁺,K⁺-ATPase에 대한 항체(anti-parietal cell antibody, PCA) 와 내인자에 대한 항체(anti-intrinsic factor antibody, IFA) 가 주요 면역 표적이다. AAG에서의 위점막 염증 및 손상의 주요 유발자는 H⁺,K⁺-ATPase 및 내인자에 특이적인 CD4⁺ T세포이며, 이들은 다음과 같은 기전을 통해 위점막 손상을 일으킨다:
IFN-γ, TNF-α, IL-17 등의 염증성 사이토카인 분비,
Fas–Fas ligand 경로를 통한 세포사멸(apoptosis) 유도,
perforin 매개 세포독성(perforin-mediated cytotoxicity) 을 통한 벽세포 직접 파괴,
B세포 도움(helper activity) 을 통한 자가항체 생성 촉진 [1,36].
면역형광검사(immunofluorescence) 결과, IL-7R과 TSLP(thymic stromal lymphopoietin) 의 발현이 AAG 환자에서 현저히 증가되어 있음이 보고되었다 [37]. 또한, CD38⁺ 형질 B세포(plasma B cell) 가 건강한 대조군에 비해 AAG 환자의 점막고유층에서 유의하게 더 많이 관찰된다 [38].
임상적으로 AAG의 초기 염증 단계(initial inflammatory events) 를 규명한 연구는 아직 부족하다. 최근 한 연구에서는, 위축이 없는 상태에서 벽세포 자가항체(PCA) 가 존재하는 환자군을 잠재성 자가면역성 위염(potential autoimmune gastritis) 으로 정의하고, 이들의 위체부 점막(corpus mucosa) 에서 상피내 림프구(intraepithelial lymphocyte, IEL) 침윤 양상을 분석하였다. 그 결과, CD3⁺ IEL의 깊은 층(deep zone) 에서의 침윤이 특징적이었으며,
100개의 상피세포당 7개 이상의 deep CD3⁺ IEL (>7/100 epithelial cells) 이 자가면역성 위염의 존재 및 중증도를 구분하는 지표로 사용될 수 있음을 확인하였다 (AUC = 0.842). 이는 위저선 점막에서의 deep CD3⁺ IEL 증가가 잠재성 AAG의 조직학적 표지(marker) 가 될 수 있음을 시사한다 [39].
3.2.2. 헬리코박터 파일로리(Helicobacter pylori) 감염은 자가면역성 위축성 위염(AAG)의 병인에 관여하는가?
Position statement
: 일부 AAG 환자에서 H. pylori 감염은 질환의 병인(pathogenesis)에 중요한 역할을 하며, 이는 자가면역 반응(autoimmune process)을 유발하거나 촉발(trigger) 하여 AAG의 전형적인 병리학적 병변을 일으키는 것으로 보인다. 반면, H. pylori 감염력이 전혀 없는 환자군(subset)의 질환 발생 기전과 병인적 기초는 아직 명확히 밝혀지지 않았다.
H. pylori는 위벽세포의 주요 자가항원인 H⁺,K⁺-ATPase와 구조적으로 유사한(epitope similarity) 항원 결정기(epitope) 를 발현하는 것으로 알려져 있다. 이러한 구조적 유사성은 분자적 모방(molecular mimicry) 기전을 통해 H. pylori 감염이 자가면역 반응을 유도할 수 있는 근거를 제공한다. 실제로, H. pylori에 감염된 AAG 환자에서는 위점막 내에 침윤한 CD4⁺ T 헬퍼세포가 자기 위벽세포의 H⁺,K⁺-ATPase 및 다양한 위 단백질의 항원결정기(epitope) 를 교차인식(cross-recognition) 하는 것이 확인되었다. 이러한 T세포는 활성화 후 다음과 같은 병리적 반응을 일으킨다:
IFN-γ, TNF-α 등의 염증성 사이토카인 생성,
Fas ligand 매개 세포사멸(Fas–FasL-mediated apoptosis) 및 perforin 매개 세포독성(perforin-mediated cytotoxicity) 을 통한 위벽세포 파괴,
H⁺,K⁺-ATPase에 대한 자가항체(anti-H⁺,K⁺-ATPase antibody) 생성 촉진.
이와 같은 기전으로 H. pylori 감염은 위 자가면역 반응을 유발하거나 악화시켜 위축(atrophy)을 일으킬 수 있다 [40,41].
또한, H. pylori에 감염된 AAG 환자들은 혈청 내에서 H⁺,K⁺-ATPase에 대한 자가항체가 순환(circulating autoantibody) 하는데, 이 항체는 H. pylori 제균치료 이후 유의하게 감소하는 것으로 보고되었다 [42–44].
H. pylori 감염이 명확히 진단된 AAG 환자에 대한 연구는 많지 않지만, 조직학적으로 위체부에 국한된 위축(corpus-restricted atrophy) 을 보인 연속 환자군을 대상으로 한 한 관찰연구에서는
조직검사 또는 혈청학적으로 H. pylori 양성이 각각 9.8% 및 35.8%,
과거 제균치료 이력이 있는 경우가 3.3%로 보고되었다 [30].
또한, 최근 다기관 연구에 따르면 AAG 환자의 27.7%에서 과거 H. pylori 감염력이 확인되었다 [14].
결론적으로, 위체부 국한 위축(corpus-restricted atrophy) 으로 진단된 일부 AAG 환자에서는 활동성 H. pylori 감염 또는 과거 H. pylori 노출의 흔적이 존재하며, 이는 H. pylori 감염이 AAG의 병인에 부분적으로 기여할 가능성과 자가면역성 위염과 H. pylori 위염이 중첩(overlap) 또는 공존(co-presence) 할 수 있음을 시사한다.
3.2.3. 자가면역성 위축성 위염(AAG)의 병인에서 유전학은 어떤 역할을 하는가?
Position statement
: AAG 환자에서 특정 HLA 하플로타입(HLA haplotype) 이 다른 자가면역질환들과 공통적으로 관찰되지만, 현재까지의 연구 자료는 매우 제한적(scarce) 이다.
AAG의 병인에는 위 자가면역 반응(gastric autoimmunity) 의 발생을 촉진하는 여러 유전적 요인(genetic factors) 이 관여하는 것으로 알려져 있다.
그 예로,
특정 MHC class II 하플로타입이 존재하여 H⁺,K⁺-ATPase, 내인자(intrinsic factor), 또는 H⁺,K⁺-ATPase–H. pylori 교차반응성 항원(epitope) 을 제시할 수 있는 경우,
자가반응성 T세포(autoreactive T cell) 의 생존을 촉진시키는 유전적 요인,
위점막 면역관용(gastric tolerance)의 붕괴,
H. pylori 감염으로 유도되는 염증반응, 특히 IFN-γ, TNF-α, IL-17 등의 사이토카인 과생산,
그리고 Fas ligand 및 perforin 매개 세포독성 반응의 만성적 지속 활성화 등이 포함된다.
이러한 요인들은 복합적으로 작용하여 위벽세포(parietal cell)에 대한 자가면역 공격(autoimmune attack) 을 촉진한다 [1,37,41].
반면, AAG 환자에서 HLA 하플로타입을 직접 분석한 연구는 매우 제한적이다.
이탈리아 연구(Italian study) 에서는 89명의 AAG 환자를 대상으로 HLA-DRB1 유전형을 평가한 결과, 절반 이상에서 HLA-DRB1*03 또는 *04 대립유전자(allele) 가 발견되었으며, 이는 일반적으로 여러 자가면역질환과 연관된 하플로타입으로 알려져 있다. 이 결과는 AAG가 자가면역성 소인을 가진 개인에서 발생할 가능성을 시사한다 [45].
핀란드 연구(Finnish study) 에서는 12명의 AAG 환자를 분석하였고, HLA-DRB1*04 및 DQB1*03 대립유전자가 AAG 발생에 유전적 소인(predisposition) 을 줄 수 있는 반면, HLA-B8–DRB1*03 은 관련이 없음을 보고하였다 [46].
또 다른 연구에서는 transcobalamin 2 (TCN2) 유전자 다형성(polymorphic variant) 이 비타민 B12 혈중 농도 감소와 연관되며, 이러한 변이가 악성빈혈(pernicious anaemia, PA) 을 동반한 AAG 환자에서 대조군보다 더 흔하게 발견되었다고 보고하였다 [47]. 이는 AAG의 임상 표현형(예: PA 동반 여부) 또한 유전적 요인에 의해 부분적으로 결정될 수 있음을 시사한다.
3.2.4. 위 자가항체(gastric autoantibodies)는 AAG의 병인에 어떤 역할을 하는가?
Position statement
: 위저선(oxyntic mucosa)의 위축성 손상을 직접적으로 유발하는 데 있어 위 자가항체의 역할은 아직 명확히 규명되지 않았다.
위벽세포의 H⁺,K⁺-ATPase에 대한 자가항체(parietal cell antibody, PCA) 와 내인자에 대한 자가항체(intrinsic factor antibody, IFA) 는 이론적으로 여러 기전을 통해 AAG 환자의 위점막 손상을 일으킬 수 있다고 여겨진다. 그러나 이러한 작용이 인체에서 실제로 입증된 사례는 없다. 또한 일부 AAG 환자에서는 혈청학적으로 자가항체가 검출되지 않는 음성형(seronegative type) 으로 나타나기도 하며, 이는 자가항체 이외의 다른 조직 손상 기전이 존재함을 시사한다. PCA는 항체의존성 세포독성(antibody-dependent cellular cytotoxicity, ADCC) 기전을 통해 위벽세포의 파괴(parietal cell killing) 를 촉진할 가능성이 있다. 반면, IFA는 내인자(intrinsic factor)의 기능적 결핍을 일으켜 비타민 B12 흡수 장애 → 결핍 → 악성빈혈(pernicious anaemia, PA) 로 이어지고, 이에 따른 신경학적 이상(neurological involvement) 및 비타민 B12 결핍으로 인한 여러 임상적 후속 결과(clinical sequelae) 를 초래한다 [1,44,48].
3.3. Diagnostic topics
3.3.1. 자가면역성 위축성 위염(AAG)에 대한 선별검사는 일반 인구집단 전체에 적용해야 하는가, 아니면 고위험군에 한정해야 하는가?
Position statement
: AAG 선별검사는 고위험군에서 분명한 이점을 가지지만, 현재 이용 가능한 근거에 따르면 일반 인구집단을 대상으로 한 보편적 선별검사(general population screening) 는 정당화되지 않는다. 따라서 보다 표적화된(targeted) 접근이 비용 효율적(cost-effective)이며, 임상적으로도 타당하며, 조기 진단율을 향상시킬 수 있을 것으로 보인다.
일반 인구를 대상으로 AAG 선별검사를 시행하기 위해서는 혈청검사(laboratory tests), 내시경 검사(endoscopy), 조직학적 평가(histological evaluation) 등이 필요하며, 이는 상당한 보건의료 비용(healthcare expenditures) 을 요구한다. AAG의 유병률이 최근 증가 추세를 보이고 있으나,
한 탐색적 연구(case-finding study)에서 15.5%의 유병률이 보고되었음에도 불구하고 [24], 전체 인구 수준에서의 임상적 유병률(clinical prevalence) 은 여전히 약 2%에서 5% 수준으로 낮게 유지되고 있다 [7,49]. 따라서 광범위한 선별검사를 시행할 경우 위양성(false positive) 결과가 다수 발생할 가능성이 높으며, 이는 불필요한 진단적 시술과 환자의 불안 증가(patient anxiety) 를 초래할 수 있다. 또한, 이러한 대규모 선별 프로그램을 관리·운영하는 데 필요한 보건의료 인프라의 부담은 잠재적 이익을 상회할 수 있으며, 일반 인구집단에서의 무증상 또는 초기 단계(subclinical/early-stage) 질환의 발견이 실제로 비용 대비 효용(cost-effectiveness)을 갖는지는 여전히 불분명하다. AAG의 조기 발견이 장기적인 합병증을 예방할 수 있다는 점은 분명하지만,
그로 인한 전체적인 진단 효율(yield) 이 의료 시스템이 감당해야 할 경제적·물리적 부담을 정당화할 만큼 크지는 않다는 것이 현재의 근거이다.
따라서 보다 효율적이고 비용 효율적인 접근법은 AAG의 유병률이 유의하게 높은 고위험군(high-risk population) 에 선별검사를 집중하는 것이다 [24,27]. 이러한 고위험군에는 다음과 같은 집단이 포함된다.
자가면역질환 가족력(family history of autoimmune diseases) 이 있는 사람
악성빈혈(pernicious anaemia, PA) 환자
제1형 당뇨병(type 1 diabetes) 환자 [50]
자가면역성 갑상선염(autoimmune thyroiditis) 환자 [51]
자가면역 다선증후군(autoimmune polyendocrine syndromes) 환자 [52]
소화불량 증상(dyspepsia) 을 호소하는 환자 [53]
불임(fertility issues) 이 있는 환자 — 최근 연구에서는 이와 AAG 간의 관련 가능성이 제시되고 있음 [54].
이러한 집단에서는 AAG의 유병률이 약 5~10%로 보고되며, 이들에서의 조기 발견(early detection) 은 악성빈혈이나 위종양(gastric malignancies) 과 같은 합병증의 예방 및 관리에 있어 매우 중요하다 [33].
3.3.2. 고위험군에서 자가면역성 위축성 위염(AAG)을 진단하기 위한 비침습적 선별검사(noninvasive screening tools)는 존재하며 유효한가?
Position statement
: 현재 AAG를 절대적으로 정확히 진단할 수 있는 단일 비침습적 검사법은 존재하지 않는다. 그러나 혈청 자가항체(anti-parietal cell antibody, PCA; anti-intrinsic factor antibody, IFA) 와 기타 혈청 표지자(펩시노겐, 가스트린-17 등) 을 조합하면, 약 80% 정도의 진단 정확도(overall accuracy) 를 보이며, 모든 경우에서 조직학적 확진(histological confirmation) 이 필요하다.
AAG의 확진은 위내시경(gastroscopy) 중 시행한 조직검사(biopsy)의 병리학적 판독(histopathology) 을 기반으로 한다. 내시경 전 선별검사(pre-endoscopic screening) 로서 혈청 표지자 검사는 AAG가 의심되는 임상 상황(예: 자가면역성 갑상선질환, 제1형 당뇨병 환자 등) 에서 유용하다. 이 중 한 항목이라도 양성일 경우, 내시경과 생검을 통해 확진 또는 배제해야 한다. 반면, 철결핍성 빈혈(iron-deficiency anaemia) 의 원인이 불명확하거나, 비타민 B12 결핍, 원인불명의 소화불량(dyspepsia), 위암 가족력(family history of GC) 이 있는 경우에는 혈청검사보다는 조기 내시경 및 전정부·체부 생검을 시행하여 조직학적으로 AAG 또는 다른 질환을 감별해야 한다 [27]. 이 접근법은 최근 발표된 RE.GA.IN 합의문(consensus) 과 일치한다 [7].
현재 이용 가능한 비침습적 표지자는 두 가지 그룹으로 구분된다.
위 자가면역 관련 표지자(autoimmunity-related markers)
PCA (anti-H⁺,K⁺-ATPase 항체)
IFA (anti-intrinsic factor 항체)
위저선 점막 손상 및 위산분비 저하를 반영하는 표지자(functional/atrophy-related markers)
펩시노겐(PG I, PG II, PG I/II 비율)
가스트린(Gastrin-17)
첫 번째 그룹은 AAG와 주로 연관, 두 번째 그룹은 H. pylori 감염에 의한 위축성 위염과 더 밀접한 관련이 있다 [1,7,27].
PCA는 AAG의 대표적 혈청 표지자이며 [1], 여러 ELISA 키트에서 민감도 80–100%, 특이도 90–99%를 보였다. 간접면역형광법(IIF)은 민감도 95–99%, 특이도 99%였으나, 정량적 측정이 가능한 ELISA가 임상적으로 더 선호된다 [56,57]. 아직 상용화되지 않은 용액상 발광면역침강검사(LIPS) 는 PCA의 두 아단위(ATP4A, ATP4B)를 개별적으로 검출할 수 있으며, 민감도 100%, 특이도 90%를 보였다 [58]. 그러나 PCA 양성은 건강인에서도 약 9%, H. pylori 관련 비위축성 또는 다병소성 위축성 위염 환자에서는 최대 20%까지 보고된다 [59,60]. 위축이 없는 PCA 양성 환자를 연 1회 내시경으로 추적한 결과, 중앙 추적기간 2년 내 약 절반이 명확한 AAG(overt AAG)로 진행하였다 [32]. 따라서 PCA 양성은 잠재성 AAG(potential autoimmune gastritis)의 초기 표지자로 간주될 수 있다. 반면, PCA 음성이라고 해서 AAG를 배제할 수는 없으며, 혈청음성형(seronegative AAG) 도 보고된 바 있다 [1,2].
IFA는 일반적으로 악성빈혈(pernicious anaemia, PA) 의 혈청 표지자로 간주되며 [61], 민감도 32–37%, 특이도 95–100%를 보인다 [57,58]. 흥미롭게도, PA나 비타민 B12 결핍이 없는 체부위축(corpus atrophy) 환자에서도 IFA 양성이 나타날 수 있으며 [57,62], 이는 임상적 PA 발생 수년 전의 초기 표지자(early marker) 일 가능성이 제시되었다 [26]. PCA와 IFA를 병합하여 평가하면 진단 신뢰도가 향상된다 [27,57,62].
가스트린(Gastrin) 증가는 위산 분비 저하로 인한 양성 되먹임(positive feedback) 결과이다 [1,2]. 그러나 프로톤펌프억제제(PPI) 사용이나 활성 H. pylori 감염이 존재하면 위체부 위축이 없어도 고가스트린혈증(hypergastrinaemia) 이 발생할 수 있다 [27]. 과거의 방사면역분석(RIA)은 현재 상용 ELISA 키트로 대체되었다 [63].
펩시노겐(PG) 은 위축의 또 다른 혈청 표지자이다.
위체부의 주세포(chief cell)는 PGI 및 PGII를 분비하고,
전정부의 유문샘은 PGII만 분비한다 [64].
체부 점막 위축이 진행되면 PGI는 감소하나 PGII는 유지, 결과적으로 PGI/PGII 비율의 점진적 감소가 나타나며, 이는 위암 위험 증가와도 관련이 있다 [65]. PG 수치는 PPI의 영향을 받지 않지만, PGI/II 비율의 저하는 H. pylori 관련 다병소성 위축성 위염에서도 관찰될 수 있다 [27]. 메타분석에 따르면, 펩시노겐을 이용한 위축성 위염 진단의 민감도 69%, 특이도 88%였다 [66].
또한, 가스트린-17을 포함한 전체 패널 검사의 체계적 문헌고찰에서는 AAG 진단에 대한 민감도 70.4%, 특이도 98.4%로 보고되었다 [67]. 다른 연구에서는 가스트린의 민감도 83.9%, 특이도 93.4%, PGI의 민감도 90.3%, 특이도 91%, PGI/PGII 비율의 민감도 83.9%, 특이도 93.7%를 보고하였다 [68].
“혈청 위 생검 검사(serum gastric biopsy)”라는 개념은 이러한 비침습적 내시경 전 평가를 지칭하기 위해 제안된 용어이다 [69]. PCA와 PGI를 병합할 경우 민감도 87%, 특이도 78%로 보고되었으며 [70], 최근의 연구에서는 PCA, IFA, PGI/II, Gastrin-17을 함께 평가한 결과, PGI/II 비율이 단독으로는 민감도 79%, 특이도 90% (AUC 0.90) 로 가장 우수하였고, PCA + PGI/II 조합 시에는 민감도 97%, 특이도 78% (AUC 0.93) 로 향상되었다 [71]. 또한, 내시경 및 생검을 시행한 344명의 환자(그중 44명은 AAG 확진)를 대상으로 한 다변량 분석에서 PGI 수치가 AAG와 유의하게 연관(p<0.001) 되었음이 보고되었다 [72].
3.3.3. 자가면역성 위축성 위염(AAG)의 진단은 위 전정부(antrum)와 체부(corpus) 생검의 조직학적 평가에 근거해야 하는가?
Position statement
: AAG의 진단은 반드시 조직학적 근거(histological grounds) 에 기반해야 하며, 전정부와 체부 양측의 조직 평가가 모든 경우에서 필수적이다. 이는 위염의 유형(classification of gastritis) 을 정확히 분류하기 위함이다.
AAG의 진단은 전정부(antrum)와 체부(corpus) 에서 채취한 위 생검조직의 병리학적 평가(histological evaluation) 를 근거로 해야 한다. 또한, AAG가 의심되는 환자에서는 정확한 내시경 관찰(accurate endoscopic examination) 이 매우 중요하다 [1,2,7,73–77]. 이러한 접근법은 AAG를 다른 형태의 만성 위염(chronic gastritis), 예를 들어 H. pylori 관련 위염(H. pylori–associated gastritis) 과 구분하는 데 도움을 준다. 후자는 주로 전정부(antrum) 를 침범하는 반면, AAG는 체부(corpus) 및 저부(fundus) 에 국한된 염증을 보이는 것이 특징이다.
특히, AAG와 H. pylori 감염이 공존(coexist) 하는 경우도 존재하며, 이러한 상황에서는 위암(gastric cancer, GC) 의 위험이 더욱 증가할 수 있다 [1,2,7]. 따라서 위의 모든 부위(stomach compartments) 에서 생검을 시행하는 것은 위점막 전체의 병변을 포괄적으로 평가(comprehensive evaluation) 하고, 정확한 질환 분류 및 추적감시(surveillance) 를 가능하게 하는 핵심적 절차이다. 내시경 생검은 Sydney system의 최신 개정판(updated Sydney system) 을 따라 시행해야 하며, 이는 다음과 같이 구성된다 [6].
전정부(antrum): 2개 생검
체부(body/corpus): 2개 생검
절흔부(incisura angularis): 1개 생검
또한, 의심 병변(suspicious regions) 이 관찰될 경우에는 반드시 별도의 시료(separate sampling) 로 추가 생검(additional biopsy) 을 시행해야 한다.
3.3.4. 자가면역성 위축성 위염(AAG) 진단을 위한 내시경적 기준은 존재하며, 그 타당성이 입증되었는가?
Position statement
: AAG의 내시경 소견은 병변의 심한 정도(severity) 에 따라 다양하며, 비특이적(nonspecific) 인 경우가 많다. 따라서 내시경 소견만으로 AAG를 진단할 수 있는 표준화된 분류(classification)는 존재하지 않는다.
내시경 검사와 병리학적 평가(histopathology)는 AAG 진단에서 모두 중요한 역할을 하지만, 내시경 단독 진단의 독립적 타당성(independent validity) 은 여전히 연구 중이다. AAG의 전형적인 내시경 소견은 다음과 같다 [6,73–75].
창백하고 위축된 위점막(pale, atrophic gastric mucosa)
노출된 점막하 혈관(submucosal vessels)
위 주름의 소실(loss of gastric folds)
그러나 이러한 소견은 AAG에만 특이적인 것은 아니며, H. pylori 감염에 의한 위축성 위염(atrophic gastritis) 등 다른 형태의 만성 위염에서도 유사하게 나타날 수 있다. 몇몇 연구에서는 초기 단계(early-stage) AAG의 내시경 소견을 기술하였는데, 특히 다음과 같은 형태가 초기 자가면역성 위염에 비교적 특이적으로 제시되었다 [18].
대나무 마디 모양(bamboo joint-like appearance)
연어알 모양 부종(salmon roe-like swelling)
또한, AAG의 또 다른 중요한 내시경 소견으로 다발성 위용종(multiple gastric polyps) 의 존재가 보고되었다. 최근 발표된 AGAPE 연구(AGAPE study) 에 따르면, AAG 환자에서 염증성 또는 과형성(polypoid hyperplastic) 등 비신생성(non-neoplastic) 용종의 발생 빈도가 상당히 높음을 확인하였다 [78]. 최근에는 협대역영상(narrow-band imaging, NBI) 을 활용하여 AAG 환자에서 장상피화생(gastric intestinal metaplasia) 을 탐지하는 정확도를 높이려는 시도가 이루어졌다. NBI는 높은 민감도(high sensitivity) 를 보였으나, pseudopyloric metaplasia와의 영상적 중첩(overlap) 으로 인해 특이도(specificity) 는 낮은 것으로 보고되었다 [79,80]. 또한, AI 기반 내시경 진단 시스템(SEER-SCOPE AI) 이 최근 개발되어, 다른 형태의 위염과 AAG를 전문가 수준의 정확도(expert-level accuracy) 로 구별할 수 있음이 입증되었으며, 이는 향후 AAG 내시경 진단의 정확도 향상에 기여할 잠재력을 보여주었다 [81]. 그럼에도 불구하고, AAG의 내시경 소견은 비특이적 특징(nonspecific features) 이 많고, 다른 형태의 위염과 중첩(overlap) 될 가능성이 높기 때문에 AAG의 확진(gold standard) 은 여전히 조직학적 진단(histopathology) 에 기반해야 한다 [7,27].
3.3.5. 자가면역성 위축성 위염(AAG)에서 현재 또는 과거의 헬리코박터 파일로리(Helicobacter pylori) 감염을 반드시 배제해야 하는가?
Position statement
: AAG의 진단 과정(diagnostic work-up)에서는 현재 또는 과거의 H. pylori 감염 여부를 확인하거나 배제하는 과정이 필수적이다. 이를 위해 조직병리학적 검사(histopathology), 혈청 IgG 항-H. pylori 항체 검사(serology assay), 그리고 환자의 병력(anamnestic data) 이 함께 평가되어야 한다.
AAG는 숙주(환자) 요인에 의해 유발되는 위 염증 질환(host-related gastric inflammatory condition) 으로, 환경적 요인(environmental factor)에 의해 발생하는 H. pylori 감염 관련 위축성 위염과 구분된다. 그러나 AAG의 병인에서 과거 혹은 현재의 H. pylori 감염이 어떤 역할을 하는지는 아직 명확히 규명되지 않았다. AAG 환자의 일부에서는 H. pylori 감염 자체가 자가면역성 염증반응(autoimmune inflammatory process) 을 유발할 수 있으며 [7], 그 주요 기전으로는 위벽세포의 H⁺,K⁺-ATPase 항원과 H. pylori 유래 항체 간의 항원모방(antigen mimicry) 이 제시된다 [40–44]. 최근 약 1,600명의 AAG 환자를 대상으로 한 다기관 연구(multicentre study) 에서는 H. pylori 비감염군(naïve AAG) 과 H. pylori 노출군(H. pylori–exposed AAG) 사이에 임상적 특징의 차이가 보고되었다. 비감염군에서는 H. pylori 노출군에 비해 다음과 같은 동반 소인이 더 흔했다 [14].
AAG의 가족력(1차 친족 내 발생) (p = 0.012)
제1형 당뇨병(type 1 diabetes) (p = 0.024)
악성빈혈(pernicious anaemia, PA) (p = 0.003)
조직학적으로 AAG와 H. pylori 관련 위축성 위염을 구분하는 가장 중요한 특징은 전정부(antral mucosa)가 보존(spared) 되어 있다는 점이다 [1,7]. 그러나 최근 한 연구에서는, 체부 위축(corpus atrophy)과 전정부 염증(antral gastritis)이 함께 존재하는 일부 환자군에서 H. pylori 제균치료 여부와 관계없이 장기 추적 시 전정부 점막이 회복되는 소견이 관찰되었으며, 이러한 경우는 AAG와 유사한 형태를 보일 수 있어 일차성(primary) AAG와 이차성(secondary) AAG를 구별하는 데 어려움을 야기한다고 보고하였다 [82]. 이러한 결과는 “H. pylori 비감염성 위염(naïve gastritis)은 전정부 점막이 보존된다”는 기존 개념과 상충된다 [7].
3.3.6. 자가면역성 위축성 위염(AAG)에서 현재의 조직학적 점수체계(Updated Sydney system, OLGA, OLGIM)는 유용한가?
Position statement
: OLGA 및 OLGIM 체계는 위암(GC) 위험 평가에 유용하다고 여겨지지만, 이들은 전정부(antrum)의 병변을 함께 고려하기 때문에, 전정부가 보존되는 AAG의 중증도(severity)를 과소평가(underestimate) 하는 경향이 있다.
현재 사용되는 조직학적 점수체계는 AAG의 평가에 유용하지만, 몇 가지 한계(limitation) 가 존재한다. 이들에는 다음이 포함된다.
Updated Sydney System: 위염의 분류(classification)를 위한 기본 체계로, 염증(inflammation), 위축(atrophy), 장상피화생(intestinal metaplasia)을 평가한다.
OLGA (Operative Link on Gastritis Assessment) 및 OLGIM (Operative Link on Gastric Intestinal Metaplasia Assessment):
위축성 위염과 장상피화생의 정도를 기반으로 위암 위험을 병기(staging) 로 분류한다.
Updated Sydney System은 여전히 조직학적 진단(histological diagnosis) 의 기본 틀로 사용되지만, 관찰자 간 차이(interobserver variability) 로 인해 재현성(reproducibility) 에 한계가 있다 [1,6,7]. 특히 위축과 염증의 정도를 평가하는 데 있어 병리학자 간 일치도는 낮거나 중등도 수준(low to moderate agreement) 으로, 위축 평가의 경우 κ(카파) = 0.31–0.6 범위에 머무른다 [86]. 반면, 장상피화생(intestinal metaplasia) 은 조직학적 특징이 명확하기 때문에 평가자 간 일치도가 더 높으며, κ = 0.62–0.9 로 보고되었다 [87]. OLGA 및 OLGIM 체계는 위축성 위염과 장상피화생의 정도를 평가하여 위암 위험도(risk stratification) 를 분류하는 데 널리 사용된다 [88]. 이 체계들은 광범위한 위축(atrophy) 또는 장상피화생(metaplasia) 을 보이는 고위험 환자를 선별하여 내시경 추적감시(endoscopic surveillance) 의 필요성을 판단하는 데 도움을 준다.
그러나 AAG의 병변은 대부분 위체부(corpus)에 국한되고 전정부는 보존되기 때문에, OLGA 및 OLGIM 체계에서는 높은 병기(high stage) 에 도달하지 못하는 경우가 많다. 이들 점수체계는 체부와 전정부의 위축 정도를 함께 합산하여 병기를 산정하므로, 전정부 위축이 없는 AAG는 낮은 병기(stage I–II) 로 분류되는 경향이 있다. 이로 인해 체부 제한성 위축(corpus-restricted atrophy) 의 실제 중증도가 과소평가될 수 있다. 결과적으로, OLGA 및 OLGIM 체계는 다병소성 위축성 위염(multifocal atrophic gastritis) 의 위암 위험 평가에는 여전히 유용하지만, 자가면역성 위축성 위염(AAG) 에 적용할 때에는 그 임상적 활용도(clinical applicability) 가 제한적이다 [7].
3.3.7. 현재의 자가면역성 위축성 위염(AAG) 진단 기준은 충분히 만족스러운가?
Position statement
: 현재의 AAG 진단 기준(diagnostic criteria) 은 여러 측면에서 완전히 만족스럽지 않다. 그 이유는 다음과 같다:
불완전하고 일관성 낮은 생물학적 표지자(biomarkers) 에 대한 의존,
혈청음성형(seronegative) 사례의 존재,
조직학적 진단의 어려움(histological challenges),
동서양 간 진단 기준의 불균질성(heterogeneity between Eastern and Western countries) 때문이다.
따라서 혈청학(serology), 내시경(endoscopy), 조직병리학(histopathology) 을 통합적으로 결합한 접근법이 가장 합리적인 진단 방법으로 권장된다.
현재 사용 중인 AAG의 진단 기준에는 여러 한계가 존재한다. 기존의 조직학적·혈청학적·생화학적 진단 방법은 도움이 되지만, 완전한 진단법이라고 보기 어렵다(3.3.2 및 3.3.6 참고). AAG는 H. pylori 관련 위축성 위염(atrophic gastritis) 과 중첩(overlap)될 수 있으며, 현재까지 보편적으로 인정된 진단 기준(universally accepted criteria) 은 없다.
조직학적 진단(histopathology-based diagnosis)의 핵심은 전정부(antral mucosa)의 보존(spared mucosa) 이며, 이는 H. pylori 감염을 배제(exclude) 하는 가장 신뢰할 만한 지표로 간주된다 [7]. 그러나 최근 연구에 따르면, 다병소성 위축성 위염(multifocal atrophic gastritis) 의 일부 환자에서는 전정부 점막이 위축되어 있더라도 장기 추적 시 점막이 회복(healing) 될 수 있으며, 이로 인해 AAG와 유사한 형태를 보이게 되어(primary vs. secondary AAG) 두 질환을 구분하기 어려워진다고 보고되었다 [82].
PCA (anti–H⁺,K⁺-ATPase 항체) 와 IFA (anti–intrinsic factor 항체) 는 AAG의 대표적 혈청 표지자이지만, 모든 환자에서 존재하지 않으며, 서구 국가(Western countries) 의 진단 기준에서는 이 항체들이 필수 요건(necessary criteria) 으로 간주되지 않는다 [1,7]. 그럼에도 미국 및 영국 진단지침(American and British guidelines) 은 이 항체 검사를 AAG 진단을 보조(supportive)하기 위한 평가 항목으로 권장하고 있다 [75,76].
반면, 동양(Eastern countries), 특히 일본의 진단 기준에 따르면, 다음 두 조건을 모두 만족할 경우 AAG로 간주한다 [80].
내시경적 및/또는 조직학적 소견(endoscopic and/or histopathological findings)
PCA 또는 IFA 양성(seropositivity)
AAG 환자의 약 20%는 조직학적으로 확진되었을 때 혈청 음성(seronegative) 상태를 보인다 [27,89]. 이는 특히 질환의 후기 단계(late stage) 와 고령 환자에서 흔하다. 질환이 진행하면서 위벽세포(parietal cell) 가 광범위하게 파괴되면, 면역계가 더 이상 반응하지 않아 PCA 수치가 자연적으로 감소 또는 소실될 수 있다. 또한, 고령에서의 면역기능 변화(immune senescence) 와 질환의 장기 경과(prolonged disease course) 도 혈청음성 상태에 기여할 수 있어, 항체검사에만 의존한 진단은 불충분하다.
AAG 진단의 골드 스탠다드(gold standard) 는 여전히 위생검(gastric biopsy)의 병리학적 확진(histopathological confirmation) 이며, 이는 RE.GA.IN 합의문(consensus) 에서도 명시되어 있다 [7]. 그러나 현실적으로 다음과 같은 문제점이 존재한다.
초기 병변(early-stage changes) 이 항상 명확하지 않을 수 있음
생검 부위가 불명확하거나(sampling site unspecified)
시료가 불충분(inadequate sampling) 하거나
Updated Sydney protocol 에 따라 채취되지 않는 경우 [75,90]
이러한 경우, 특히 생검 부위나 임상 병력이 불분명할 때, 호산구 침윤(eosinophil infiltration) 이 잠재적 진단 보조 지표(potential diagnostic marker) 로 제시되었으며, 이는 특히 소아 환자(pediatric patients) 에서 유용할 수 있다 [91,92]. 비침습적 검사(noninvasive tests) 측면에서, 혈청 바이오마커 패널(serological biomarker panel) 인 GastroPanel® 은 AAG의 조기 선별(early screening)에 유망하나, 기존 연구 대부분이 다병소성 위축성 위염(multifocal atrophic gastritis) 에 초점을 맞추었기 때문에 AAG에 대한 검증(validation) 이 추가로 필요하다 [27,55]. 또한, 비타민 B12, 혈색소(haemoglobin), 가스트린(gastrin), 크로모그라닌 A(chromogranin A) 등을 결합한 생화학적 점수체계(biochemical score) 가 제안되었으며, 좋은 진단 정확도를 보였으나, 이 역시 추가 검증이 필요하다 [93].
3.4. Management
3.4.1. 자가면역성 위염(AAG) 환자에서 동반된 헬리코박터 파일로리(H. pylori) 감염을 치료해야 하는가?
Position statement
: AAG 환자에서 H. pylori 감염이 동반되어 있다면 반드시 제균 치료를 시행해야 한다.
H. pylori는 세계보건기구(WHO) 산하 국제암연구소(International Agency for Research on Cancer, IARC)에 의해 1군(Group I) 발암인자로 분류되어 있다 [7, 94]. H. pylori 감염 환자는 위암 발생 위험이 비감염자에 비해 3~6배 높으며, 제균 치료 후 그 위험이 유의하게 감소한다 [95]. 무작위대조시험(RCT)의 메타분석에 따르면, 제균 치료를 받은 환자에서 위암 발생 위험(RR 0.54, 95% CI 0.40–0.72) 및 위암 관련 사망률(RR 0.61, 95% CI 0.40–0.92) 이 모두 감소하였다 [96].
H. pylori가 AAG로 진행하는 면역학적 과정을 직접적으로 유발할 수 있는지는 아직 명확히 입증되지 않았다 [1, 41, 97]. 그러나 H. pylori 감염은 AAG 환자에서 신생물(위암 등) 위험 증가와 연관될 수 있다.
초기의 연구들에서는 H. pylori 감염 여부가 불분명하거나(‘pre-H. pylori era’) 과거에 감염이 있었던 환자들을 포함한 집단에서 AAG 관련 위암 위험이 높다고 보고하였으나, 이러한 혼재된 병인(mixed aetiology) 으로 인해 순수한 AAG 환자의 위암 위험을 정확히 평가하기 어려웠다.
최근 발표된 장기 전향적 연구에서는 ‘순수 AAG(pure AAG)’ 환자 211명을 평균 10,541인년(person-years) 추적 관찰하였고, 저등급 이형성 5예만 발생하였으며 고등급 이형성이나 침윤성 위암은 한 건도 보고되지 않았다 [31]. 이러한 거의 부재한 위암 위험은 다른 연구자들에 의해서도 확인되었다 [29]. 반면, 일부 전향적 단일기관 및 후향적 다기관 연구에서는 AAG 환자의 위암 위험이 0은 아니지만 매우 낮은 수준으로 보고되었다 [14, 30]. 현재까지의 근거에 따르면, H. pylori 감염이 없거나 이미 소실된 AAG 환자에서도 위암 발생 가능성을 완전히 배제할 수는 없으나, 그 위험은 낮다.
특히, 다병소성 위축(multi-focal atrophy, 광범위 위축성 위염) 과 장상피화생(intestinal metaplasia) 의 존재는 위암 위험을 높이는 요인으로 알려져 있다 [74–76, 98, 99]. AAG 환자에서 H. pylori 감염이 현재 또는 과거에 존재한 경우, 위점막의 위축 및 화생 병변은 전정부의 점액선(H. pylori 매개) 과 체부 또는 위저부의 벽세포선(자가면역 매개) 을 모두 침범할 수 있다. 이러한 광범위한 위축성 변화(extensive atrophy) 는 순수한 벽세포선 제한적(autoimmune-restricted) 손상보다 위암 발생 위험이 더 높다 [100]. 따라서, AAG 환자에서 H. pylori 감염이 확인되면 제균 치료를 반드시 시행해야 하며, 이는 위점막 손상의 진행을 억제하고 위암 발생 가능성을 줄이기 위함이다 [7].
또한, 이중 빈혈(dimorphic anemia) 은 AAG 후기 단계에서 흔히 관찰되며, 평균 적혈구 용적(MCV)은 정상이나 적혈구 크기의 불균일(anisocytosis) 을 보인다. 이는 철결핍성 빈혈과 비타민 B12 결핍이 동시에 존재하기 때문이다 [101]. 한편, 철결핍성과 비타민 B12 결핍은 H. pylori 감염 자체와도 관련이 있을 수 있으므로 [94], AAG 환자에서 H. pylori 제균 치료는 위암 예방뿐 아니라 철분 및 비타민 B12 결핍 개선에도 도움이 된다.
3.4.2. AAG 환자에서 H. pylori 제균치료가 질환의 자연경과나 예후에 영향을 미칠 수 있는가?
Position statement
: 이미 발생한 위 병변을 H. pylori 제균치료로 호전시키기는 어렵다. 그러나 제균은 위 점막의 염증을 감소시키며, 장기적인 합병증을 예방하는 데 도움이 될 수 있다.
AAG 환자는 위암(gastric cancer, GC) 과 제1형 위 신경내분비종양(type 1 gastric neuroendocrine neoplasms, t1-gNENs) 발생 위험이 증가되어 있다 [1, 2, 8]. 최근의 연구들에 따르면 AAG에서 위암의 절대 위험은 낮은 것으로 보이지만 [13, 29–31], t1-gNENs는 내시경 및 조직학적 추적관찰을 시행한 환자의 4–12% 에서 관찰된다 [1]. 위암의 발암 과정은 다단계(multi-step)로 진행되며, 그 중 위축성 위염(atrophy) 과 장상피화생(intestinal metaplasia) 은 대표적인 전암 병변(precancerous conditions)으로 간주된다 [83].
AAG 환자에서도 H. pylori 감염은 위 점막의 만성 염증(chronic inflammation) 을 유발하는 추가적인 자극 요인으로 작용하여, 만성 위축성 위염, 장상피화생, 위암 의 발달에 기여할 수 있다. 따라서, 세균 제균이 이러한 병적 상태의 진행을 억제하거나 일부 회복을 유도할 수 있는 예방적 전략으로 간주될 수 있다 [7, 83, 94]. 다만, 위 체부(corpus)를 침범한 만성 위축성 위염에서 위산분비가 저하된 경우, 비침습적 검사(요소호기검사, 대변항원검사)를 이용한 H. pylori 감염의 검출 신뢰도는 낮을 수 있다 [85]. 그럼에도 불구하고, 감염이 확인되면 반드시 제균치료를 시행해야 한다 [83, 102].
그러나, 이미 위축성 위염과 장상피화생이 형성된 이후에는 제균치료로 이들 병변이 가역적으로 회복되는지 여부는 논란의 여지가 있다. 메타분석에 따르면 H. pylori 제균은 위축성 병변의 개선에는 장기적인 이익이 있으나, 장상피화생에 대해서는 거의 효과가 없거나 제한적인 것으로 보고되었다 [103–105].
즉, 장상피화생은 H. pylori 제균 이후에도 되돌리기 어렵거나 매우 제한적으로만 회복되는 ‘위암 발생의 비가역적 단계(point of no return)’ 로 간주된다.
그럼에도 불구하고, 위축성 위염과 장상피화생이 존재하는 환자에서도 H. pylori 제균은 병변의 추가 진행을 억제하기 위해 권장된다.
한편, gastrin-17의 지속적인 증가는 enterochromaffin-like (ECL) 세포의 증식, 이형성(dysplasia), 그리고 t1-gNENs 의 잘 알려진 위험 요인이다 [106]. AAG의 자연경과에서 선상(linear) 및 결절성(nodular) ECL 세포 과형성이 선종양(adenomatoid) 과형성/이형성 및 t1-gNENs 로 진행하는 양상은 주로 광범위한 위산분비세포(oxyntic mucosa) 위축을 가진 환자에서 관찰된다 [30, 31]. 이러한 위저선 위축(oxyntic atrophy) 과 선종양 과형성/이형성 및 t1-gNENs 간의 연관성은 잘 확립되어 있으며, 선종양 과형성/이형성은 t1-gNENs 발생의 예측 인자로 알려져 있다 [1, 107].
반면, H. pylori 감염은 t1-gNENs의 발생에 직접적인 병인적 역할을 하지 않는다.최근의 다기관 후향적 연구에 따르면, t1-gNENs는 H. pylori 비감염(AAG H. pylori-naïve) 환자의 10.1%, 감염력(H. pylori-exposed)이 있었던 AAG 환자의 8.1% 에서 발생하였으며, 이는 통계적으로 유의한 차이를 보이지 않았다 (보정 후 HR 0.74, 95% CI 0.41–1.35) [14]. 이전 연구에서는 H. pylori 제균 후 일부 환자에서 위산분비 기능 및 ECL 세포 과형성이 부분적으로 회복되며, 감염이 조직학적으로 완전히 치유된 환자의 절반 이상에서 ECL 세포 과형성이 감소함을 보고하였다 [108]. 그러나 이러한 변화가 t1-gNENs의 발생에 실제로 영향을 미치는지는 아직 입증되지 않았다. 결론적으로, AAG에서 H. pylori 감염과 제균치료는 t1-gNENs의 발생과 질병 예후에 실질적인 영향을 미치지 않는 것으로 보인다.
3.4.3. AAG 환자에서 제균치료 요법은 유효한가?
Position statement
: 현재까지 AAG 환자에서 H. pylori 제균을 위한 특정 치료 요법을 권고할 만큼의 근거는 부족하다. 그러나 프로톤펌프억제제(PPI)를 사용하지 않고도 제균이 가능한 것으로 보인다.
H. pylori 감염의 제균 치료 요법은 일반적으로 비스무트(bismuth) 기반 요법이 가장 많이 사용되며, 그 외에 순차요법(sequential therapy) 또는 복합요법(hybrid therapy) 이 사용된다 [109–111]. 무작위대조시험(RCT)에 따르면, 비스무트, 메트로니다졸(metronidazole), 테트라사이클린(tetracycline), PPI를 병용한 고전적 4제요법(bismuth quadruple therapy) 이 3제요법(triple therapy) 보다 H. pylori 제균율이 더 높았다 [112, 113]. 과거에는 이러한 다중 약제 복용의 복잡성이 단점이었으나, 단일 제형(single-pill) 비스무트 기반 요법(SPBT) 의 개발로 이를 극복할 수 있게 되었으며, 이 요법은 임상시험뿐 아니라 실제 진료에서도 높은 제균 성공률을 보였다 [109]. 다만, 지금까지의 제균치료 관련 연구들은 AAG 환자를 대상으로 한 연구는 거의 없었다.
AAG는 위산 분비 저하와 위내 pH 상승이 특징적이므로, 이러한 환자에서 PPI의 사용 필요성은 논란의 여지가 있다 [114]. 최근 한 연구에서는 위체부 위축성 위염(corpus atrophic gastritis) 환자 76명 중 H. pylori 감염이 조직학적으로 확인된 환자들을 대상으로, PPI를 사용하지 않는 변형 제균 요법의 내약성과 효과를 평가하였다. 1차 치료로 아목시실린 기반 병용 또는 순차 요법(amoxicillin-based therapy, ABT; n=30) 과 비스무트 단일 제형 요법(single-pill bismuth therapy, SPBT; n=46) 이 처방되었다. 전체 제균율은 90.1% (95% CI 69.4–115.1%) 로 나타났으며, SPBT의 제균율이 ABT보다 유의하게 높았다 (SPBT: 97.7%, 95% CI 70.4–132.0% vs ABT: 78.6%, 95% CI 49.2–118.9%, p = 0.013). 이 결과는 위체부 위축성 위염 환자에서도 PPI를 사용하지 않고 90% 이상의 제균 성공률을 달성할 수 있음을 보여준다 [115].
3.4.4. AAG 환자는 위 신생물 병변의 조기 진단을 위해 내시경 추적관찰(endoscopic surveillance)로부터 이득을 얻을 수 있는가?
Position statement
: AAG 환자는 위 제1형 신경내분비종양(gastric type 1 neuroendocrine neoplasms, t1-gNENs), 드물게는 위 이형성(gastric dysplasia) 또는 위암(gastric cancer, GC) 의 조기 진단을 위해 내시경 추적관찰로부터 임상적 이득을 얻는다는 충분한 근거가 있다. 다만, 적절한 추적 시기와 보다 정밀한 위험도 층화(risk stratification) 에 대해서는 추가적인 규명이 필요하다.
앞서 언급한 바와 같이, AAG 환자는 위 t1-gNENs 및 위암의 발생 위험이 증가되어 있다 [1, 2]. 최근 조직학적으로 확진된 AAG 또는 위체부 제한성 위염(corpus-restricted gastritis) 환자들을 대상으로 한 전향적 연구들에서도 위 t1-gNENs 발생 위험이 일관되게 높음이 확인되었으며, 위암 발생 위험에 대해서는 아직 상반된 결과가 보고되고 있다. 4.3~7년의 추적기간 동안, 두 연구 [29, 31] 에서는 각각 저등급 이형성(low-grade dysplasia) 5예 및 14예가 보고되었고, 다른 두 연구 [29, 30] 에서는 각각 고등급 이형성(high-grade dysplasia) 4예 및 1예가, 또 한 연구 [30]에서는 위암(GC) 6예가 발생하였다. 한편, 다기관 후향적 연구에서는 AAG 환자의 위암 발생 위험이 매우 낮지만 0은 아닌 것으로 보고되었다 [14].
이러한 결과의 차이는 연구마다 H. pylori 관련 AAG 환자 포함 비율의 차이에 기인할 수 있다. 예를 들어, 두 연구에서는 H. pylori 감염 환자를 제외하였으나, 한 연구에서는 현재 혹은 과거의 H. pylori 감염 환자를 배제하지 않았음에도, 새롭게 발생한 위암 또는 고등급 이형성은 모두 H. pylori 음성 환자에서 발생하였고, H. pylori 양성 환자에서는 저등급 이형성 2예만 보고되었다.
그러나, 다른 염증성 암(inflammatory cancers) 의 경우와 마찬가지로, 만성 염증이 일정 수준 이상의 조직 손상에 도달하면, 초기 유발 요인(trigger)과 무관하게 시간이 경과함에 따라 암으로 진행할 수 있음이 알려져 있다. 따라서, 위체부 위축(corpus atrophy) 또는 장상피화생(intestinal metaplasia) 이 오래 지속된 AAG 환자에서는 이러한 만성 염증성 손상이 신생물 합병증(neoplastic complications) 으로 진행할 수 있다.
가장 최근의 유럽 가이드라인(European guidelines) 은 AAG 환자에서 위 t1-gNENs와 위암의 조기 발견을 위해 3년마다 고품질(high-quality) 내시경 추적관찰을 시행할 것을 권고하고 있다 [74]. 반면, 미국 가이드라인(American guidelines) 은 AAG 환자에서 최적의 추적관찰 주기는 명확히 확립되지 않았다고 기술하며, 환자 개별 특성과 의사-환자 간 공동 의사결정(shared decision making) 을 기반으로 추적간격을 조정해야 한다고 제시한다 [75].
영국 가이드라인(British guidelines) 역시 AAG 자체에 대한 명시적인 추적관찰 권고는 없으며, 광범위한 위축(extensive atrophy) 또는 장상피화생 이 있는 환자에 한해 3년 간격의 내시경 추적관찰을 권장한다. 그러나 주목할 점은, 악성빈혈(pernicious anemia, PA) 을 위암의 강력한 위험요인 중 하나로 간주하고 있다는 것이다 [76]. 또한, 위암의 직계가족력(first-degree family history) 이 있거나 지속적인 H. pylori 감염이 존재하는 경우, 내시경 추적관찰은 1~2년마다 시행하는 것이 권장된다.
3.4.5. AAG 환자의 내시경 추적관찰은 전자 염색내시경(electronic chromoendoscopy)과 위 생검(random/targeted biopsy)을 병행하여 시행해야 하는가?
Position statement
: AAG 환자의 최적의 추적관찰 전략은 고해상도(high-definition) 내시경과 전자 염색내시경(electronic chromoendoscopy) 을 이용하여 이상 부위에 대한 표적생검(targeted biopsy) 과 전정부(antrum) 및 체부(corpus)의 무작위생검(random biopsy) 을 병행하는 것이다.
내시경적으로 AAG는 특히 초기 단계에서 정상 위점막과의 구별이 어렵다. 질병이 더 진행된 단계에서는 급성 염증 소견이 나타날 수 있으며, 이는 평탄해진 위체부 주름(flattened gastric corpus folds), 점막 부종(mucosal swelling), 발적(redness) 등으로 특징지어진다. 질환이 진행함에 따라 위체부(corpus)와 위저부(fundus)의 위축(atrophy) 이 명확해지며, 점막이 창백해지고(pale mucosa) 점막이 얇아지면서 점막하 혈관(submucosal vessels) 이 비쳐 보이는 소견이 관찰된다. 반면, 전정부(antrum) 는 대체로 정상으로 유지되는 경우가 많다 [74, 75, 80].
진단 정확도를 극대화하기 위해 내시경의사는 점막 시야의 최적화(optimal mucosal visualization) 를 보장해야 한다. 이를 위해 소포제(defoming agent) 및 점액용해제(mucolytic agent) 인 시메티콘(simethicone) 과 1% N-아세틸시스테인(N-acetylcysteine) 의 사용이 도움이 될 수 있으며, 단순한 물 세척(water irrigation)만으로는 효과적인 점막 세정이 어려울 수 있다 [73–77].
고해상도 내시경(high-definition endoscopy) 과 염색내시경(chromoendoscopy, CE) 의 병용은 위의 전암 병변(precancerous conditions) 및 조기 신생물 병변(early neoplastic lesions) 진단에 있어, 단독 백색광 내시경(high-definition white-light endoscopy)보다 우수하다고 알려져 있다 [73, 74]. 따라서, 가능하다면 전자 염색내시경(electronic CE) 을 확대관찰 유무와 관계없이 활용하는 것이 권장되며, 이를 통해
전암성 병변 진단,
위축 및 화생 병변의 병기 설정(staging)을 위한 생검 가이드,
조기 신생물 병변 탐지 에 도움을 받을 수 있다 [73–77].
비록 최신 내시경 기술의 해상도가 높아졌지만, 현재의 권고안들은 여전히 표준화된 생검 프로토콜(standardised biopsy protocol) 의 적용을 강조하고 있다. 즉, 최소 두 부위(antrum과 corpus) 에서 소만(lesser curvature) 과 대만(greater curvature) 을 각각 포함한 생검을 시행해야 하며, 두 개의 별도 용기(vial) 에 구분하여 담아야 한다. 또한, 내시경적으로 신생물 의심 병변이 관찰되는 부위에서는 추가적인 표적생검(targeted biopsy) 을 시행해야 한다 [73–77]. 가장 최근의 유럽 MAPS III 가이드라인 은, 기저 내시경(baseline endoscopy)에서 위축 또는 장상피화생이 관찰되었더라도 내시경적으로 명확한 병변이 보이지 않는 경우에는, 추적 내시경 시 루틴 위생검(routine gastric biopsy)을 반드시 시행할 필요는 없다고 명시하고 있다 [74].
3.4.6. AAG 환자에서 동반질환이나 관련 질환에 대한 선별검사는 유용한가?
Position statement
: 새롭게 진단된 모든 AAG 환자는 미량영양소 결핍(micronutrient deficiencies), 빈혈(anaemia), 그리고 자가면역 갑상선질환(autoimmune thyroid disease) 및 셀리악병(coeliac disease) 을 포함한 기타 연관 자가면역질환(associated autoimmunity) 에 대한 선별검사를 시행해야 한다.
AAG 환자는 여러 영양소의 흡수 장애(malabsorption) 위험이 높으며, 특히 비타민 B₁₂, 철(iron), 칼슘(calcium), 비타민 D 결핍이 흔하게 동반된다 [116, 117]. 또한, 이들은 다른 자가면역질환(autoimmune comorbidities) 이 병발할 가능성이 높다. 따라서, 초진 시(first evaluation) 모든 AAG 환자에서 미량영양소 결핍과 빈혈 여부를 선별검사(screening) 해야 한다 [1, 2, 101]. 더불어, 무증상(asymptomatic) 혹은 경증 증상(mildly symptomatic) 으로 나타날 수 있는 자가면역질환에 대해서도 선별검사가 필요하다. 대표적으로, 자가면역 갑상선질환(autoimmune thyroid disease) 의 확인을 위해
TSH (thyroid-stimulating hormone),
항갑상선과산화효소항체(anti-thyroid peroxidase antibody, anti-TPO),
항타이로글로불린항체(anti-thyroglobulin antibody, anti-Tg),
항-TSH 수용체항체(anti-TSH receptor antibody)
를 측정해야 한다.
또한, 셀리악병(coeliac disease) 의 선별을 위해서는 항-조직 트랜스글루타미나제 IgA 항체(anti-tissue transglutaminase IgA antibody) 검사를 시행해야 한다. 그 외의 질환들은 임상 증상 및 징후(clinical manifestations) 에 따라 선택적으로 평가할 수 있다. 한편, 공통가변면역결핍(common variable immune deficiency, CVID) 환자의 상당수에서 전반적 위축성 위염(atrophic pangastritis) 이 동반된다는 사실이 보고되어 있으므로, 이러한 경우에는 총 면역글로불린(total immunoglobulins) 과 IgA, IgG, IgM 의 측정이 권장된다 [1].
3.4.7. AAG 환자에서 미량영양소 결핍(micronutrient deficiencies)은 어떻게 치료해야 하는가?
Position statement
: AAG 환자는 비타민 B₁₂의 평생 보충요법(lifelong supplementation) 이 필요하며, 가능하면 비경구적(parenteral) 투여가 권장된다. 또한 엽산(folic acid) 은 비타민 B₁₂와 상승 작용(synergistic effect) 을 보이므로 함께 보충해야 한다. 그 외 철(iron) 및 비타민 D 와 같은 미량영양소는 정기적으로 검사하여 결핍 시 보충해야 한다.
비타민 B₁₂는 특히 임상적으로 중증 증상을 보이는 경우 비경구적(parenteral) 으로 보충해야 한다. 일반적으로 시아노코발라민(cyanocobalamin) 을 매월 1,000 IU에서 3개월마다 5,000 IU까지 근육주사(intramuscular injection)로 투여하는 것이 충분하다. 현재까지 AAG 환자를 대상으로 한 경구제제(oral) 또는 설하제제(sublingual formulations) 의 효과를 평가한 연구는 없다 [1, 118].
철분(iron)의 경우, 경구제(oral) 또는 비경구제(parenteral) 사용에 대한 AAG 환자 대상의 임상시험은 없다. 따라서, 일반적인 철결핍성 빈혈(iron deficiency anaemia) 치료 지침을 따르는 것이 권장된다. 즉,
경증 빈혈(mild anaemia) 또는 내약성이 좋은 경우 → pH 비의존성 제형(pH-independent formulations, 예: liposomal formulations) 의 경구 철분 보충을 우선 고려하고,
중등도~중증 빈혈 또는 경구제 부작용이 있는 경우 → 정맥주사제(intravenous formulations) 를 사용하는 것이 바람직하다.
최근 연구에서는 위체부 위축성 위염(corpus atrophic gastritis) 환자에서 정맥주사용 ferric carboxymaltose 투여의 효과를 평가한 결과, 치료 12주 후 78.4%의 환자에서 철결핍성 빈혈이 회복되었고, 24개월까지 44.6%에서 그 효과가 유지되었다고 보고되어, 정맥 철분요법이 유효(valid)한 치료 접근법임이 확인되었다 [119].
엽산(folic acid)은 비타민 B₁₂와 항상 병용 보충해야 하며, 이는 장기간 엽산 고갈(folic acid depletion)이나 ‘folate trap’ 현상을 예방하기 위함이다. 또한 호모시스테인(homocysteine) 수치를 측정하면 MTHFR 유전자 변이로 인한 혼란요인(confounding factor) 을 배제하고, 비타민 B₁₂ 및 엽산 보충 효과를 모니터링하는 데 도움이 된다.
기타 비타민 B군(B vitamins) 보충이 AAG에서 필수적인지는 명확히 밝혀지지 않았지만, 혈전색전증(thromboembolic manifestations) 이 있는 환자에서는 개별적으로 보충을 고려해야 한다. 또한 비타민 D 역시 결핍 시 보충해야 하며, 일부 연구에서는 AAG 환자에서 비타민 D 흡수 장애(malabsorption) 가 발생할 수 있음이 보고되었다 [120].
3.4.8. AAG 환자의 소화불량(dyspepsia) 증상은 어떻게 치료해야 하는가?
Position statement
: 프로톤펌프억제제(PPI) 는 AAG 환자에서 일상적으로 사용해서는 안 된다. 이는 신경내분비종양(neuroendocrine neoplasms) 발생 위험을 높일 수 있기 때문이다. 다만, 위출혈(gastric bleeding) 이나 바렛식도(Barrett’s oesophagus) 와 같은 특정 상황에서는 예외적으로 사용할 수 있다.
현재까지 AAG 환자의 소화불량 치료에 있어 위산분비억제제(antisecretory agents), 위장운동촉진제(prokinetics) 또는 기타 약제의 효과와 안전성에 대한 근거는 부족하다. 현재까지 AAG 환자를 대상으로 소화불량(dyspepsia) 또는 위식도역류질환(GERD) 치료에 관한 PPI나 위장운동촉진제, 기타 약제의 안전성과 유효성을 평가한 임상시험은 없다. 실제로, PPI의 장기적·광범위한 사용은 권장되지 않는다. 그 이유는 PPI 사용이 제1형 위 신경내분비종양(t1-gNENs) 의 발생 위험을 높이고, 드물지만 위암(GC) 위험을 증가시킬 수 있음이 보고되었기 때문이다 [1, 114].
그러나, AAG의 초기 단계(early phase) 에는 일부 환자에서 잔존 위산 분비(residual acid secretion) 가 남아 있을 수 있으며, pH-임피던스 검사(pH-impedance monitoring) 에서 위식도역류질환(GERD) 이 확인되는 경우가 있다. 이러한 환자에서는 PPI 단기 요법(short course of PPIs) 을 통해 증상 완화 및 합병증(예: 역류성 식도염, 바렛식도) 을 예방하는 것이 도움이 될 수 있다.
반면, 질환의 후기 단계(late phase) 에 접어든 AAG 환자들은 비산성 역류(non-acid reflux) 에 의해 증상을 경험할 수 있으며, pH-임피던스 검사로 확인된다 [121]. 이 경우 제산제(antacids) 투여로 증상이 완화되는 경우도 있으나, 치료는 대체로 어렵고 반응이 불완전하다.
위장운동촉진제(prokinetics) — 예를 들어 돔페리돈(domperidone), 레보설피리드(levosulpiride), 생강 추출물(ginger extracts) 등은 기능성 소화불량(functional dyspepsia) 치료에 준하여 사용할 수 있으나, AAG 환자를 대상으로 한 연구는 현재까지 없다. 한편, 일부 연구에서는 zinc-L-carnosine 이 위 점막세포에서 항염증 작용(anti-inflammatory property) 을 나타낼 수 있음이 보고되었다 [38].
4. Conclusions
본 합의문(position paper)은 자가면역성 위축성 위염(AAG) 분야에서 오랜 경험과 전문성을 가진 여러 전문가들이 모여, 현재의 지식과 과학적 근거를 바탕으로 AAG와 관련된 임상적·학문적 주요 쟁점들에 대해 답을 도출하고자 한 공동의 노력(convergent expert effort) 을 반영한다.
이 문헌에서 제시된 핵심 요점(key points)은 다음과 같다. 비록 최근 몇 년간 AAG에 대한 학문적 관심과 연구 수가 지속적으로 증가하고 있으나, 과학적 근거(scientific evidence) 는 여전히 부족하며, 여러 중요한 쟁점들이 명확히 규명되지 못한 상태로 남아 있다.
특히, 다음과 같은 임상적으로 중대한 문제(clinically relevant issues) 들이 여전히 충분한 근거를 확보하지 못하고 있다.
Helicobacter pylori 감염의 역할(role of H. pylori infection)
진단 기준(diagnostic criteria)
추적 감시(surveillance)의 필요성
치료 접근법(treatment issues)
이들 주제는 대규모·고품질 연구(high-level evidence) 가 부족한 상태이며, 여전히 주로 단일 기관(single-centre)의 임상 경험과 관찰 결과에 의존하고 있다. 따라서, AAG 연구에는 여전히 많은 과제가 남아 있으며, 이 문헌에서 제시된 연구 의제(research agenda, Fig. 1) 가 그 필요성을 잘 보여준다.
Fig. 1. Agenda for future research in autoimmune gastritis.
국제적으로 통일된 진단 및 관리 기준(internationally shared criteria) 의 마련이 시급하다.
AAG에 대한 이해가 심화될수록,
정확하고 시의적절한 진단(correct and timely diagnosis) 이 가능해지고,
임상적 관리(clinical management) 와 환자의 삶의 질(quality of life) 이 향상되며,
이 과소평가 되어온 질환이 초래하는 경제적·사회적 부담(economic and social burden) 또한 감소할 것이다.
<Abstract>
Autoimmune atrophic gastritis (AAG) is a non-self-limiting immune-mediated disorder exerting growing interest. The main autoantigen, the beta subunit of the proton pump (H+, K+-ATPase), is localised on the oxyntic mucosa parietal cells, limiting the autoimmune inflammatory damage to this stomach compartment. Clinical manifestations of AAG may occur late, once corpus-fundus atrophy occurs, and are characterised by loss of gastric acidity, impaired iron and/or cobalamin malabsorption, and increased risk of gastric type 1 neuroendocrine neoplasms and possibly gastric adenocarcinoma. Many topics regarding epidemiology, clinical features, pathogenesis, diagnosis, and management remain to be clarified. AAG patients are frequently misdiagnosed or diagnosed with delay. AAG still represents a clinical challenge and a great opportunity for advancing our knowledge on gastrointestinal autoimmune diseases and gastric precancerous conditions. The timely and correct diagnosis of AAG patients is clinically relevant to avoid potentially harmful consequences due to micronutrient deficiencies and related anaemia and neoplastic complications. The current position paper addresses AAG in adults and reflects the views of the Autoimmune gastRitis Italian netwOrk Study grOup (ARIOSO) on its epidemiology, clinical features, pathogenesis, diagnosis, and management. Improving the understanding of AAG would facilitate timely and accurate diagnosis, enhance clinical management and patients' quality of life, and reduce the economic and social burden of this underrecognized condition.
Keywords: Atrophic gastritis; Autoimmune gastritis; Gastric cancer; Gastric neuroendocrine neoplasm; Helicobacter pylori; Iron deficiency anaemia; Natural history, pernicious anaemia; Position paper.
자가면역성 위축성 위염(Autoimmune atrophic gastritis, AAG)은 자가제한적(self-limiting) 으로 경과하지 않는 면역 매개성 질환(immune-mediated disorder) 으로, 최근 점차 많은 관심을 받고 있다. AAG의 주요 자가항원(autoantigen) 은 프로톤 펌프(proton pump, H⁺, K⁺-ATPase) 의 β-소단위체(beta subunit) 로, 이는 위저선 점막(oxyntic mucosa)의 벽세포(parietal cell) 에 위치한다. 따라서 자가면역성 염증 손상은 위의 이 부위로 국한된다.
🔹 임상적 특징 (Clinical manifestations)
AAG의 임상 증상은 대개 체부-저부 위축(corpus-fundus atrophy) 이 진행된 후 늦게(late) 나타나며, 다음과 같은 특징을 보인다.
위산 결핍(loss of gastric acidity)
철(iron) 및/또는 코발라민(cobalamin, 비타민 B₁₂) 흡수 장애
위 제1형 신경내분비종양(gastric type 1 neuroendocrine neoplasms) 발생 위험 증가
위선암(gastric adenocarcinoma) 위험 가능성
🔹 미해결 과제 (Unresolved issues)
AAG와 관련된 역학(epidemiology), 임상 양상(clinical features), 병태생리(pathogenesis), 진단(diagnosis), 치료 및 관리(management) 등 여러 측면에서 여전히 명확히 규명되지 않은 부분이 많다. AAG 환자들은 오진(misdiagnosis) 되거나 진단이 지연(delayed diagnosis) 되는 경우가 빈번하다.
🔹 임상적 중요성 (Clinical relevance)
AAG는 여전히 임상적 도전(clinical challenge) 이자, 위장관 자가면역질환(gastrointestinal autoimmune diseases) 및 위 전암성 병변(gastric precancerous conditions) 에 대한 지식을 확장할 수 있는 중요한 기회를 제공한다.
AAG 환자의 신속하고 정확한 진단(timely and correct diagnosis) 은 임상적으로 매우 중요하다. 이는 미량영양소 결핍(micronutrient deficiencies) 및 관련 빈혈(anemia), 그리고 신생물(neoplastic) 합병증과 같은 잠재적으로 유해한 결과를 예방하는 데 필수적이다.
🔹 ARIOSO 연구그룹의 입장 (ARIOSO Position Paper)
본 입장 논문(position paper) 은 성인 AAG 환자(adult AAG) 를 대상으로 하며, 자가면역성 위염 이탈리아 네트워크 연구그룹 (Autoimmune gastRitis Italian netwOrk Study grOup, ARIOSO) 의 역학, 임상 양상, 병태생리, 진단 및 관리에 대한 견해(views) 를 반영한다.
🔹 결론 (Conclusion)
AAG에 대한 이해를 향상시키는 것은
신속하고 정확한 진단(timely and accurate diagnosis) 을 촉진하고,
임상적 관리(clinical management) 와 환자의 삶의 질(quality of life) 을 개선하며,
이 과소인식된 질환(underrecognized condition) 으로 인한 경제적·사회적 부담(economic and social burden) 을 줄이는 데 기여할 것이다.
References
[1] Lenti MV, Rugge M, Lahner E, et al. Autoimmune gastritis. Nat Rev Dis Primers 2020;6:56.
[2] Lahner E, Zagari R, Zullo A, et al. Chronic atrophic gastritis: natural history, diagnosis and therapeutic management. A position paper by the Italian society of hospital gastroenterologists and digestive endoscopists [AIGO], the Italian Society of Digestive Endoscopy [SIED], the Italian Society of Gastroenterology [SIGE], and the Italian Society of Internal Medicine [SIMI]. Dig Liver Dis 2019;51:1621–32.
[3] Lenti M, Miceli E, Cococcia S, et al. Determinants of diagnostic delay in autoimmune atrophic gastritis. Aliment Pharmacol Ther 2019;50:167–75. doi:10.1111/apt.15317.
[4] Gattrell W, Logullo P, van Zuuren E, et al. ACCORD (ACcurate COnsensus Reporting Document): a reporting guideline for consensus methods in biomedicine developed via a modified Delphi. PLoS Med 2024;21:e1004326.
[5] Strickland R, Mackay I. A reappraisal of the nature and significance of chronic atrophic gastritis. Am J Dig Dis 1973;18:426–40. doi:10.1007/BF01071995.
[6] Dixon M, Genta R, Yardley J, et al. Classification and grading of gastritis. The updated Sydney System. International Workshop on the Histopathology of Gastritis, Houston 1994. Am J Surg Pathol 1996;20:1161–81.
[7] Rugge M, Genta R, Malfertheiner P, et al. RE.GA.IN; RE GA IN. RE.GA.IN.: the real-world Gastritis Initiative-updating the updates. Gut 2024;73:407–41.
[8] Carmel R. Prevalence of undiagnosed pernicious anemia in the elderly. Arch Intern Med 1996;156:1097–100.
[9] Rustgi S, Bijlani P, Shah S. Autoimmune gastritis, with or without pernicious anemia: epidemiology, risk factors, and clinical management. Ther Adv Gastroenterol 2021;14:17562848211038771.
[10] Massironi S, Zilli A, Elvevi A, et al. The changing face of chronic autoimmune atrophic gastritis: an updated comprehensive perspective. Autoimmun Rev 2019;18:215–22. doi:10.1016/j.autrev.2018.08.011.
[11] Li M, Huang Y, Liang X, Lu H. Prevalence of autoimmune gastritis worldwide: a systematic review and meta-analysis. Helicobacter 2025;30(4):e70065. doi:10.1111/hel.70065.
[12] Miceli E, Lenti M, Padula D, et al. Common features of patients with autoimmune atrophic gastritis. Clin Gastroenterol Hepatol 2012;10:812–14.
[13] Lahner E, Dilaghi E, Cingolani S, et al. Gender-sex differences in autoimmune atrophic gastritis. Transl Res 2022;248:1–10.
[14] Lenti M, Miceli E, Lahner E, et al. Distinguishing features of autoimmune gastritis depending on previous Helicobacter pylori infection or positivity to anti-parietal cell antibodies: results from the autoimmune gastRitis Italian netwOrk study grOup (ARIOSO). Am J Gastroenterol 2024;119:2408–17.
[15] Carabotti M, Lahner E, Esposito G, et al. Upper gastrointestinal symptoms in autoimmune gastritis: a cross-sectional study. Medicine 2017;96:e5784.
[16] Song H, Held M, Sandin S, et al. Increase in the prevalence of atrophic gastritis among adults age 35 to 44 years old in Northern Sweden between 1990 and 2009. Clin Gastroenterol Hepatol 2015;13:1592–600.
[17] Kalkan Ç, Soykan I. Polyautoimmunity in autoimmune gastritis. Eur J Intern Med 2016;31:79–83.
[18] Kotera T, Ayaki M, Sumi N, et al. Characteristic endoscopic findings in early-stage autoimmune gastritis. Endosc Int Open 2024;12:E332–8.
[19] Chen Y, Ji X, Zhao W, et al. A real-world study on the characteristics of autoimmune gastritis: a single-center retrospective cohort in China. Clin Res Hepatol Gastroenterol 2025;49:102556.
[20] Wang X, Lu C, Ding Y, et al. A retrospective study on clinical features of autoimmune gastritis: impact of age, sex, and autoimmune thyroid disease in China. Gut Liver 2025 [Epub ahead of print]. doi:10.5009/gnl240448.
[21] Azzouz Y, Abidi S, Chbicheb S. Retrospective cross-sectional study of 34 cases of pernicious anemia at Mohammed V Military Training Hospital, Morocco. Pan Afr Med J 2023;45:79.
[22] Doh K, Thiam I, Halim A, et al. Pathological overview of chronic gastritis in Senegal: results of upper gastrointestinal tract endoscopies. Med Sante Trop 2017;27:439–42 English.
[23] Gonzalez A, Latorre G, Paredes L, et al. Mucocutaneous manifestations in autoimmune gastritis: a prospective case-control study. Am J Gastroenterol 2021;116:2374–84.
[24] Lenti M, Miceli E, Joudaki S, et al. Impact of an active case-finding strategy in autoimmune gastritis. Eur J Intern Med 2024;130:179–81.
[25] Toh B, van Driel I, Gleeson P. Pernicious anemia. N Engl J Med 1997;337:1441–8.
[26] Green R, Allen L, Bjørke-Monsen A, et al. Vitamin B12 deficiency. Nat Rev Dis Primers 2017;3:17040.
[27] Dottori L, Pivetta G, Annibale B, et al. Update on serum biomarkers in autoimmune atrophic gastritis. Clin Chem 2023 Oct 3;69(10):1114–31.
[28] Miceli E, Vanoli A, Lenti M, et al. Natural history of autoimmune atrophic gastritis: a prospective, single centre, long-term experience. Aliment Pharmacol Ther 2019;50:1172–80.
[29] Miceli E, Lenti M, Gentile A, et al. Long-term natural history of autoimmune gastritis: results from a prospective monocentric series. Am J Gastroenterol 2024;119:837–45.
[30] Dilaghi E, Dottori L, Pivetta G, et al. Incidence and predictors of gastric neoplastic lesions in corpus-restricted atrophic gastritis: a single-center cohort study. Am J Gastroenterol 2023;118:2157–65.
[31] Rugge M, Bricca L, Guzzinati S, et al. Autoimmune gastritis: long-term natural history in naïve Helicobacter pylori-negative patients. Gut 2023;72:30–8.
[32] Lenti M, Miceli E, Vanoli A, et al. Time course and risk factors of evolution from potential to overt autoimmune gastritis. Dig Liver Dis 2022;54:642– 644.
[33] Lenti M, Broglio G, Di Sabatino A. Unravelling the risk of developing gastric cancer in autoimmune gastritis. Gut 2023;72:1429–30.
[34] Lahner E, Dilaghi E, Dottori L, et al. Not all that is corpus restricted is necessarily autoimmune. Gut 2023 Nov 24;72(12):2384–5.
[35] Hoft S, Brennan M, Carrero J, et al. Unveiling cancer-related metaplastic cells in both Helicobacter pylori infection and autoimmune gastritis. Gastroenterology 2025;168:53–67.
[36] D’Elios M, Bergman M, Azzurri A, et al. H(+),K(+)-atpase (proton pump) is the target autoantigen of Th1-type cytotoxic T cells in autoimmune gastritis. Gastroenterology Feb 2001;120(2):377–86.
[37] Della Bella C, Antico A, Panozzo M, et al. Gastric Th17 cells specific for H+/K+-ATPase and serum IL-17 signature in Gastric autoimmunity. Front Immunol 2022 Jul 11;13:952674.
[38] Lenti M, Facciotti F, Miceli E, et al. Mucosal overexpression of thymic stromal lymphopoietin and proinflammatory cytokines in patients with autoimmune atrophic gastritis. Clin Transl Gastroenterol 2022;13(7):e00510 Epub 2022 Jun 13. doi:10.14309/ctg.0000000000000510.
[39] Lenti M, Vanoli A, Miceli E, et al. Increase of deep intraepithelial lymphocytes in the oxyntic mucosa of patients with potential and overt autoimmune gastritis. Front Immunol 2022;13:866167 Published 2022 May 4. doi:10.3389/ fimmu.2022.866167.
[40] Amedei A, Bergman M, Appelmelk B, et al. Molecular mimicry between Helicobacter pylori antigens and H+, K+ –adenosine triphosphatase in human gastric autoimmunity. J Exp Med 2003 Oct 20;198(8):1147–56.
[41] D’Elios M, Appelmelk B, Amedei A, et al. Gastric autoimmunity: the role of Helicobacter pylori and molecular mimicry. Trends Mol Med Jul 2004;10(7):316–23.
[42] Appelmelk B, Faller G, Claeys D, et al. Bugs on trial: the case of Helicobacter pylori and autoimmunity. Immunol Today Jul 1998;19(7):296–9.
[43] D’Elios M, Bergman M, Amedei A, et al. Helicobacter pylori and gastric autoimmunity. Microbes Infect Dec 2004;6(15):1395–401.
[44] Bergman M, Vandenbroucke-Grauls C, et al. The story so far: helicobacter pylori and gastric autoimmunity. Int Rev Immunol 2005;24(1–2):63–91 Jan-Apr.
[45] Lahner E, Spoletini M, Buzzetti R, et al. HLA-DRB1×03 and DRB1×04 are associated with atrophic gastritis in an Italian population. Dig Liver Dis 2010;42(12):854–9.
[46] Oksanen A, Haimila K, Rautelin H, et al. Immunogenetic characteristics of patients with autoimmune gastritis. World J Gastroenterol 2010; 16(3):354–8.
[47] Lahner E, Gentile G, Purchiaroni F, et al. Single nucleotide polymorphisms related to vitamin B12 serum levels in autoimmune gastritis patients with or without pernicious anaemia. Dig Liver Dis 2015;47(4):285–90.
[48] Lenti M, Cococcia S, Miceli E, et al. Red flags for the diagnosis of autoimmune gastritis. Clin Res Hepatol Gastroenterol Jan 2022;46(1):101780.
[49] Castellana C, Eusebi L, Dajti E, et al. Autoimmune Atrophic Gastritis: a clinical review. Cancers (Basel) 28 Mar 2024;16(7).
[50] Prinz N, Tittel S, Bachran R, et al. Characteristics of patients with type 1 diabetes and additional autoimmune disease in the DPV registry. J Clin Endocrinol Metab 18 Aug 2021;106(9):e3381-e89.
[51] Boutzios G, Koukoulioti E, Goules A, et al. Hashimoto thyroiditis, anti-parietal cell antibodies: associations with autoimmune diseases and malignancies. Front Endocrinol (Lausanne) 2022;13:860880.
[52] Bjørklund G, Pivin M, Hangan T, et al. Autoimmune polyendocrine syndrome type 1: clinical manifestations, pathogenetic features, and management approach. Autoimmun Rev Aug 2022;21(8):103135.
[53] Singh S, Chakole S, Agrawal S, et al. A comprehensive review of upper gastrointestinal symptom management in autoimmune gastritis: current insights and future directions. Cureus Aug 2023;15(8):e43418.
[54] Miceli E, Di Stefano M, Lenti M, et al. Pregnancy-related complications in autoimmune atrophic gastritis: a monocentric experience. Dig Liver Dis Jan 2023;55(1):146–8.
[55] Bakulina N, Tikhonov S, Malkov V, et al. Noninvasive screening of autoimmune atrophic gastritis in asymptomatic subjects by serological biomarker test (GastroPanel(®)). Anticancer Res Mar 2022;42(3):1517–26.
[56] Lukens M, Koelman C, Curvers J, et al. Comparison of different immunoassays for the detection of antibodies against intrinsic factor and parietal cells. J Immunol Methods 2020;487:112867.
[57] Lahner E, Norman G, Severi C, et al. Reassessment of intrinsic factor and parietal cell autoantibodies in atrophic gastritis with respect to cobalamin deficiency. Am J Gastroenterol 2009;104:2071–9.
[58] Lahner E, Brigatti C, Marzinotto I, et al. Luminescent immunoprecipitation system (LIPS) for detection of autoantibodies against ATP4A and ATP4B subunits of gastric proton pump H+, K+-ATPase in atrophic body gastritis patients. Clin Trans Gastroenterol 2017;8:e215.
[59] Zhang Y, Weck M, Schottker B, et al. Gastric parietal cell antibodies, Helicobacter pylori infection, and chronic atrophic gastritis: evidence from a large population-based study in Germany. Cancer Epidemiol Biomark Prev 2013;22:821–6.
[60] Rusak E, Chobot A, Krzywicka A, et al. Anti-parietal cell antibodies - diagnostic significance. Adv Med Sci 2016;61:175–9.
[61] Bizzaro N, Antico A. Diagnosis and classification of pernicious anemia. Autoimmun Rev 2014;13:565–8.
[62] Marzinotto I, Dottori L, Baldaro F, et al. Intrinsic factor autoantibodies by luminescent immuno-precipitation system in patients with corpus atrophic gastritis. J Transl Autoimmun 2021;4:100131.
[63] Rehfeld J, Bardram L, Hilsted L, et al. Pitfalls in diagnostic gastrin measurements. Clin Chem 2012;58:831–6.
[64] Syrjänen K, Eskelinen M, Peetsalu A, et al. Gastropanel® biomarker assay: the most comprehensive test for Helicobacter pylori infection and its clinical sequelae. A critical review. Anticancer Res 2019;39:1091–104.
[65] Hattori Y, Tashiro H, Kawamoto T, et al. Sensitivity and specificity of mass screening for gastric cancer using the measurement of serum pepsinogens. Jpn J Cancer Res 1995;86:1210–15.
[66] Huang Y, Yu J, Kang W, et al. Significance of serum pepsinogens as a biomarker for gastric cancer and atrophic gastritis screening: a systematic review and metaanalysis. PLoS ONE 2015;10:e0142080.
[67] Zagari R, Rabitti S, Greenwood D, et al. Systematic review with metaanalysis: diagnostic performance of the combination of pepsinogen, gastrin-17 and anti-Helicobacter pylori antibodies serum assays for the diagnosis of atrophic gastritis. Aliment Pharmacol Ther 2017;46:657–67.
[68] Kishikawa H, Nakamura K, Ojiro K, et al. Relevance of pepsinogen, gastrin, and endoscopic atrophy in the diagnosis of autoimmune gastritis. Sci Rep 2022;12:4202.
[69] Antico A, Tampoia M, Villalta D, et al. Clinical usefulness of the serological gastric biopsy for the diagnosis of chronic autoimmune gastritis. Clin Dev Immunol 2012;2012:520970.
[70] Lahner E, Marzinotto I, Lampasona V, et al. Autoantibodies toward ATP4A and ATP4B subunits of gastric proton pump H+, K+- ATPase are reliable serological pre-endoscopic markers of corpus atrophic gastritis. Clin Transl Gastroenterol 2020;11:e00240.
[71] Krike P, Shums Z, Polaka I, et al. The diagnostic value of anti-parietal cell and intrinsic factor antibodies, pepsinogens, and gastrin-17 in corpus-restricted atrophic gastritis. Diagn (Basel) 2022;12:2784.
[72] Chapelle N, Martin J, Osmola M, et al. Serum pepsinogens can help to discriminate between H. pylori-induced and auto-immune atrophic gastritis: results from a prospective multicenter study. Dig Liver Dis 2023;55:1345–51.
[73] Pimentel-Nunes P, Libânio D, Marcos-Pinto R, et al. Management of epithelial precancerous conditions and lesions in the stomach (MAPS II): european Society of Gastrointestinal Endoscopy (ESGE), European Helicobacter and Microbiota Study Group (EHMSG), European Society of Pathology (ESP), and Sociedade Portuguesa de Endoscopia Digestiva (SPED) guideline update 2019. Endoscopy 2019;51:365–88 39.
[74] Dinis-Ribeiro M, Libânio D, Uchima H, et al. Management of epithelial precancerous conditions and early neoplasia of the stomach (MAPS III): european Society of Gastrointestinal Endoscopy (ESGE), European Helicobacter and Microbiota Study Group (EHMSG) and European Society of Pathology (ESP) Guideline update 2025. Endoscopy 2025;57(5):504–54. doi:10.1055/ a-2529-5025.
[75] Shah S, Piazuelo M, Kuipers E, et al. AGA Clinical Practice update on the diagnosis and management of atrophic gastritis: expert review. Gastroenterology 2021;161:1325–1332.e7.
[76] Banks M, Graham D, Jansen M, et al. British Society of Gastroenterology guidelines on the diagnosis and management of patients at risk of gastric adenocarcinoma. Gut 2019;68:1545–75.
[77] Morgan D, Corral J, Li D, et al. ACG Clinical guideline: diagnosis and management of gastric premalignant conditions. Am J Gastroenterol 2025;120:709–37.
[78] Massironi S, Gallo C, Lahner E, et al. Occurrence and characteristics of endoscopic gastric polyps in patients with autoimmune gastritis (AGAPE study): a multicentric cross-sectional study. Dig Liver Dis 2025;57:198–205.
[79] Dilaghi E, Esposito G, Pivetta G, et al. Endoscopic diagnosis of gastric intestinal metaplasia in patients with autoimmune gastritis using narrow-band imaging: does pseudopyloric metaplasia muddy the waters? Endosc Int Open Apr 2022;10:E434-e40.
[80] Kamada T, Watanabe H, Furuta T, et al. Diagnostic criteria and endoscopic and histological findings of autoimmune gastritis in Japan. J Gastroenterol 2023;58:185–95.
[81] Chen S, Xu L, Yan L, et al. A novel endoscopic artificial intelligence system to assist in the diagnosis of autoimmune gastritis: a multicenter study. Endoscopy 2025;57:299–309.
[82] Dottori L, Palumbo C, Dilaghi E, et al. Antral mucosa healing at long-term follow-up in patients with corpus atrophic gastritis and concomitant antral gastritis may mimic autoimmune gastritis. Dig Liver Dis 2025;57:333–9.
[83] Correa P. Human gastric carcinogenesis: a multistep and multifactorial process: first American cancer society award lecture on cancer epidemiology and prevention. Cancer Res 1992;52:6735–40 PMID: 1458460.
[84] Hoft S, Noto C, DiPaolo R. Two distinct etiologies of gastric cancer: infection and autoimmunity. Front Cell Dev Biol 2021;9:752346. doi:10.3389/fcell.2021. 752346.
[85] Lahner E, Vaira D, Figura N, et al. Role of noninvasive tests (C-urea breath test and stool antigen test) as additional tools in diagnosis of Helicobacter pylori infection in patients with atrophic body gastritis. Helicobacter 2004;9:436–42.
[86] Aydin O, Egilmez R, Karabacak T, et al. Interobserver variation in histopathological assessment of Helicobacter pylori gastritis. World J Gastroenterol 2003;9:2232–5.
[87] Chen X, van der Hulst R, Bruno M, et al. Interobserver variation in the histopathological scoring of Helicobacter pylori related gastritis. J Clin Pathol 1999;52:612–15.
[88] Rugge M, Fassan M, Pizzi M, et al. Operative link for gastritis assessment vs operative link on intestinal metaplasia assessment. World J Gastroenterol 2011;17:4596–601.
[89] Conti L, Lenti M, Di Sabatino A, et al. Seronegative autoimmune atrophic gastritis is more common in elderly patients. Dig Liver Dis 2020;52:1310–14.
[90] Lenti M, Miceli E, Padula D, et al. The challenging diagnosis of autoimmune atrophic gastritis. Scand J Gastroenterol 2017;52:471–2.
[91] Bettington M, Brown I. Autoimmune gastritis: novel clues to histological diagnosis. Pathology 2013;45:145–9.
[92] Lenti M, Joudaki S, Miceli E, Lahner E, Massironi S, Votto M, Licari A, Caimmi S, Bramuzzo M, Di Leo G, Crocco M, Malerba F, Francavilla R, Lionetti P, Alvisi P, Panceri R, Zuin G, Villanacci V, Barp J, Fuoti M, Oliva S, Aloi M, Distante M, Assa A, Dotan Y, Amato A, Romano C, Staiano A, Miele E, Strisciuglio C, Fioretti M, Zingone F, Cananzi M, De Giacomo C, Di Nardo G, Quadrelli A, Vanoli A, Paulli M, Annibale B, Marseglia G, Di Sabatino A. Pediatric autoimmune gastritis: an international, multicentric study. J Pediatr Gastroenterol Nutr 12 Aug 2025 Epub ahead of print. PMID: 40798919. doi:10.1002/jpn3.70187.
[93] Miceli E, Padula D, Lenti M, et al. A laboratory score in the diagnosis of autoimmune atrophic gastritis: a prospective study. J Clin Gastroenterol 2015;49:e1–5.
[94] Malfertheiner P, Camargo M, El-Omar E, et al. Helicobacter pylori infection. Nat Rev Dis Primers 2023;9:19.
[95] Forman D, Newell D, Fullerton F, et al. Association between infection with Helicobacter pylori and risk of gastric cancer: evidence from a prospective investigation. BMJ 1991;302:1302–5.
[96] Ford A, Yuan Y, Moayyedi P. Helicobacter pylori eradication therapy to prevent gastric cancer: systematic review and meta-analysis. Gut 2020;69:2113–21.
[97] Presotto F, Sabini B, Cecchetto A, et al. Helicobacter pylori infection and gastric autoimmune diseases: is there a link? Helicobacter 2003;8:578–84.
[98] Rugge M, Genta R, Fassan M, et al. OLGA gastritis staging for the prediction of gastric cancer risk: a long-term follow-up study of 7436 patients. Am J Gastroenterol 2018;113:1621–8.
[99] Capelle L, de Vries A, Haringsma J, et al. The staging of gastritis with the OLGA system by using intestinal metaplasia as an accurate alternative for atrophic gastritis. Gastrointest Endosc 2010;71:1150–8.
[100] Graham D, Rugge M, Genta R. Diagnosis: gastric intestinal metaplasia - what to do next? Curr Opin Gastroenterol 2019;35:535–43.
[101] Lenti M, Lahner E, Bergamaschi G, et al. Cell blood count alterations and patterns of anaemia in autoimmune atrophic gastritis at diagnosis: a multicentre study. J Clin Med 2019;8:1992.
[102] Doorakkers E, Lagergren J, Engstrand L, et al. Helicobacter pylori eradication treatment and the risk of gastric adenocarcinoma in a western population. Gut 2018;67:2092–6.
[103] Rokkas T, Pistiolas D, Sechopoulos P, et al. The long-term impact of Helicobacter pylori eradication on gastric histology: a systematic review and metaanalysis. Helicobacter 2007;12:32–8 Suppl 2.
[104] Zhu F, Zhang X, Li P, et al. Effect of Helicobacter pylori eradication on gastric precancerous lesions: a systematic review and metaanalysis. Helicobacter 2023;28:e13013. doi:10.1111/hel.13013.
[105] Liang Y, Yang Y, Nong R, et al. Do atrophic gastritis and intestinal metaplasia reverse after Helicobacter pylori eradication? Helicobacter 2024;29:e13042. doi:10.1111/hel.13042.
[106] Annibale B, Azzoni C, Corleto V, et al. Atrophic body gastritis patients with enterochromaffin-like cell dysplasia are at increased risk for the development of type I gastric carcinoid. Eur J Gastroenterol Hepatol 2001;13:1449–56.
[107] Vanoli A, La Rosa S, Luinetti O, et al. Histologic changes in type A chronic atrophic gastritis indicating increased risk of neuroendocrine tumor development: the predictive role of dysplastic and severely hyperplastic enterochromaffin-like cell lesions. Hum Pathol 2013;44:1827–37.
[108] Annibale B, Aprile M, D’Ambra G, et al. Cure of Helicobacter pylori infection in atrophic body gastritis patients does not improve mucosal atrophy but reduces hypergastrinemia and its related effects on body ECL-cell hyperplasia. Aliment Pharmacol Ther 2000;14:625–34.
[109] Malfertheiner P, Megraud F, Rokkas T, et al. Management of Helicobacter pylori infection: the Maastricht VI/Florence consensus report. Gut Epub ahead print August 2022. doi:10.1136/gutjnl-2022-327745.
[110] De Francesco V, Bellesia A, Ridola L, et al. Firstline therapies for Helicobacter pylori eradication: a ritical reappraisal of updated guidelines. Ann Gastroenterol 2017;30:373–9.
[111] Chey W, Leontiadis G, Howden C, et al. ACG clinical guideline: treatment of Helicobacter pylori infection. Am J Gastroenterol 2017;112:212–38.
[112] Zagari R, Dajti E, Cominardi A, et al. Standard bismuth quadruple therapy versus concomitant therapy for the first-line treatment of Helicobacter pylori infection: a systematic review and metaanalysis of randomised controlled trials. J Clin Med 2023;12:3258.
[113] Nyssen O, Bordin D, Tepes B, et al. European Registry on Helicobacter pylori Management (Hp-EuReg): patterns and trends in first-line empirical eradication prescription and outcomes of 5 years and 21 33 patients. Gut 2021;70:40–54.
[114] Lahner E, Carabotti M, Annibale B. Treatment of Helicobacter pylori infection in atrophic gastritis. World J Gastroenterol 2018;24:2373–80.
[115] Dilaghi E, Mosciatti L, Dottori L, et al. Therapeutic regimens against Helicobacter pylori infection without proton pump inhibitors in patients with corpus atrophic gastritis: a real-life single-centre longitudinal observational study. Ther Adv Gastroenterol 2025;18:17562848241308035 Published 2025 Jan 14. doi:10.1177/17562848241308035.
[116] Lenti M, Hammer H, Tacheci I, et al. European consensus on malabsorptionUEG & SIGE, LGA, SPG, SRGH, CGS, ESPCG, EAGEN, ESPEN, and ESPGHAN. Part 1: definitions, clinical phenotypes, and diagnostic testing for malabsorption. United Eur Gastroenterol J 2025 Mar 25 Epub ahead of print. PMID: 40129317. doi:10.1002/ueg2.70012.
[117] Lenti M, Hammer H, Tacheci I, et al. European consensus on MalabsorptionUEG & SIGE, LGA, SPG, SRGH, CGS, ESPCG, EAGEN, ESPEN, and ESPGHAN: part 2: screening, special populations, nutritional goals, supportive care, primary care perspective. United Eur Gastroenterol J 2025 Mar 15 Epub ahead of print. PMID: 40088199. doi:10.1002/ueg2.70011.
[118] Esposito G, Dottori L, Pivetta G, et al. Pernicious anemia: the hematological presentation of a multifaceted disorder caused by cobalamin deficiency. Nutrients 2022;14:1672.
[119] Dottori L, Corleone Tsar’kov D, Dilaghi E, et al. Efficacy and safety of intravenous ferric carboxymaltose treatment of iron deficiency anaemia in patients with Corpus atrophic gastritis: a retrospective study. Nutrients 2023;15:4199.
[120] Massironi S, Cavalcoli F, Zilli A. Relevance of vitamin D deficiency in patients with chronic autoimmune atrophic gastritis: a prospective study. BMC Gastroenterol 2018;18:172.
[121] Carabotti M, Esposito G, Lahner E, et al. Gastroesophageal reflux symptoms and microscopic esophagitis in a cohort of consecutive patients affected by atrophic body gastritis: a pilot study. Scand J Gastroenterol 2019;54:35–40.